Introduction
Anatomically, the stylohyoid ligament extends between the lesser horn of the hyoid bone and the styloid process of the temporal bone.Reference Standring1 This tripartite structure, comprising the lesser horn of the hyoid bone, the stylohyoid ligament and the styloid process, is collectively referred to as the hyoid apparatus or stylohyoid chain.Reference de Bakker, de Bakker, Soerdjbalie-Maikoe and Dikkers2 When examining the function of the stylohyoid chain, the following can be listed: it contributes to the suspension of the hyoid bone, indirectly supporting the tongue and larynx and may influence postural stability through cranio-cervical connections.
The stylohyoid complex exhibits anatomical variations, such as an elongated styloid process (ESP) and an aberrant hyoid apparatus (AHA).Reference de Bakker, de Bakker, Soerdjbalie-Maikoe and Dikkers3 The ESP is typically defined as a styloid process exceeding 3 cm in length (Figure 1).Reference Nedunchezhian4–Reference Bokhari, Graham and Mohseni6 Eagle syndrome refers to the presence of clinical symptoms, such as oropharyngeal pain or the sensation of a foreign body in the throat, associated with ESP. The term AHA describes incomplete/complete ossification or calcification of the hyoid apparatus (Figure 2, Figure 3), which can result in symptoms including dysphagia, limited cervical mobility, glossopharyngeal neuralgia or pain due to compression of adjacent sensory nerves.Reference de Bakker, de Bakker, Soerdjbalie-Maikoe and Dikkers3
Three-dimensional volume-rendered (left) and sagittal multiplanar reconstruction (right) MDCTA images demonstrating a markedly elongated right styloid process, measuring 5.25 cm from its origin at the temporal bone to the distal end of the process (MacDonald–Jankowski Pattern E).

Three-dimensional volume-rendered MDCTA image (left) and sagittal multiplanar reconstruction (right) demonstrating an aberrant hyoid apparatus (AHA) with segmented calcification of the stylohyoid chain (red arrowheads, the last arrowhead is the lesser horn of the hyoid bone). The calcified segments extend from the temporal bone toward the hyoid bone.

Three-dimensional volume-rendered MDCTA image demonstrating bilateral aberrant hyoid apparatus (AHA) with calcification of the stylohyoid chain, corresponding to MacDonald–Jankowski Pattern K. Calcified segments extend from the ceratohyal (region 3) to the hypohyal (region 4), forming a continuous structure.

The term AHA, though often used interchangeably with calcified stylohyoid chain (CSC) in the literature, may encompass a broader spectrum of developmental deviations beyond mere ossification. It is frequently assumed that stylohyoid chain calcification also involves the ESP.Reference Bagga, Kumar and Yeluri7–Reference Raina, Gothi and Rajan10 However, De Bakker emphasised that these two conditions have been “intermingled in the literature” and proposed that both Eagle’s syndrome and AHA be classified under the term second pharyngeal arch cartilage anomalies.Reference de Bakker, de Bakker, Soerdjbalie-Maikoe and Dikkers3 The second pharyngeal arch, also known as the hyoid arch, plays a fundamental role in craniofacial development. Reichert’s cartilage, derived from this arch, gives rise to the stapes, styloid process of the temporal bone, stylohyoid ligament, lesser horn and the upper part of the hyoid bone body.Reference Moore11
Embryologically, the stylohyoid chain develops from four distinct regions: the intrapetrosal part of the styloid process originates from the tympanohyal (region 1); the main shaft of the styloid process from the stylohyal (region 2); the stylohyoid ligament from the keratohyal and/or accessory keratohyal (region 3); and the lesser horn of the hyoid bone from the hypohyal (region 4).Reference de Bakker, de Bakker, Soerdjbalie-Maikoe and Dikkers3
Assuming both ESP and AHA represent pathologies of the stylohyoid chain, the most widely accepted classification system is that of MacDonald-Jankowski (Figure 4).Reference MacDonald-Jankowski9 According to this classification, there are 12 types of calcification of the stylohyoid chain. Patterns A–B–C–D represent typical styloid processes. Pattern E is an ESP. Patterns F–G–H–I–J–K represent calcified stylohyoid ligaments and pattern L has no styloid process visible.Reference MacDonald-Jankowski9 Pattern A consists of region 1, tympanohyal alone; pattern B consists of region 2, stylohyal alone; pattern C consists of regions 1 and 2, distinct; pattern D consists of regions 1 and 2, merged; pattern E consists of regions 1, 2 and 3, merged; pattern F consists of regions 1, 2 and 3, distinct; pattern G consists of regions 1 and 2, merged, but distinct from 3; pattern H consists of regions 2 and 3, distinct; pattern I consists of regions 2 and 3, merged, but distinct from 1; pattern J consists of region 3 alone: pattern K consists of region 3 and 4, merged (may include calcification in another region).Reference MacDonald-Jankowski9
Schematic representation of the 12 identified morphological patterns of the stylohyoid complex.

Therefore, this study aimed to evaluate both ESP (the underlying cause of Eagle’s syndrome) and AHA, as anatomical variations of the stylohyoid chain complex.
Methods
This study included data from 406 individuals who underwent head and neck computed tomography angiography (CTA) between 2014 and 2022. As bilateral imaging was available in each case, a total of 812 heminecks were retrospectively assessed. The participants ranged in age from 2 to 95 years (mean age: 45 years), with an equal male-to-female ratio (1:1). This study received approval from our institution’s Non-Interventional Clinical Research Ethics Committee.
A 64-detector row dual CT scanner (Somatom Definition, Siemens Healthcare, Erlangen, Germany) was used for CT imaging. The protocol was as follows: 64 × 0.6 collimation, 1.4 pitch, 0.5-second rotation time. The source images were reconstructed into 1-mm slice thicknesses, and then axial, coronal and sagittal images were reformatted and analysed. In our health center, it is a routine practice to obtain informed consent from every patient who receives CT angiography imaging with the use of a contrast agent.
All statistical analyses were performed using SPSS version 15.0 (SPSS Inc., Chicago, IL, USA). Continuous variables were expressed as mean plus or minus standard deviation, median and minimum–maximum values, while categorical variables were summarised as frequencies and percentages.
The normality of data distribution was evaluated using the Shapiro–Wilk test, and visual inspection of histograms and Q–Q plots was also performed to confirm distributional assumptions. The Levene’s test was applied to assess the homogeneity of variances. In addition to descriptive statistics, associations between categorical variables were assessed using the chi-squared test or the Monte Carlo corrected chi-squared test (applied when expected cell counts in more than 20 per cent of cells were <5).
For comparisons between two independent groups, the independent samples t-test was used when parametric assumptions were met; otherwise, the Welch’s t-test was applied. In the comparison of more than two independent groups, the Kruskal–Wallis test was used due to violation of parametric assumptions or small subgroup sizes. When a statistically significant difference was detected, post hoc pairwise comparisons were performed using the Mann–Whitney U test, and Bonferroni correction was applied to control for type I error (adjusted significance threshold set according to the number of pairwise comparisons).
A p-value of less than 0.05 was considered statistically significant.
Variation scanning was performed on axial, coronal and sagittal sections of multi-detector CTA (MDCTA) images using the bone window setting. Multi-planar reconstructions (MPR) were applied to optimise visualisation of the stylohyoid chain complex in each plane. Three-dimensional volume-rendered (VR) images were generated to provide complementary spatial information on the continuity, orientation and extent of calcifications.
In cases where an ESP was identified, its length was measured from its origin at the tympanic plate to the tip of the process using the measurement tool in the MDCTA software. A styloid process was classified as elongated if its length exceeded 30 mm.
In cases where an AHA was observed, the stylohyoid chain complex was categorised according to the classification system proposed by MacDonald-Jankowski. Since patterns A–B–C–D represent typical styloid processes, they were collectively considered as a single group and not analysed separately.
All evaluations were conducted based on gender and age groups. The participants were divided into three age categories: 0–24 years, 25–59 years and 60 years and above.
Results
Anatomical variations were observed in 71 (17 per cent) cases, including 49 (12 per cent) cases with an ESP and 17 (4 per cent) with an AHA. Notably, five (1 per cent) cases exhibited an AHA in conjunction with a contralateral ESP. The distribution of these findings is summarised in Table 1.
Descriptive results by gender

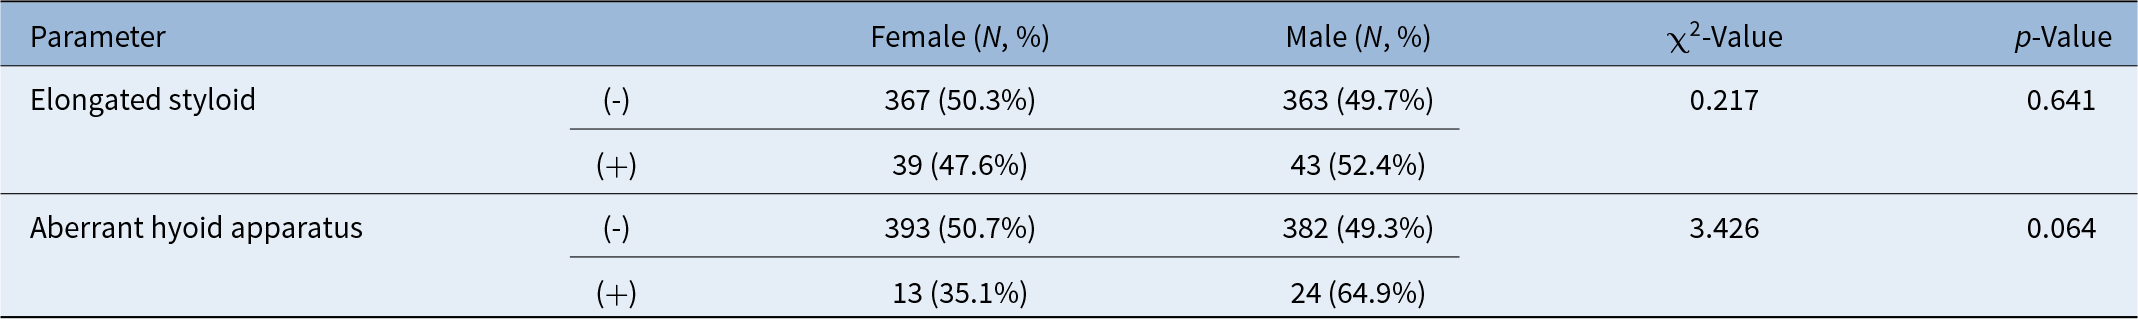
Among those with anatomical variations, 31 (7.4 per cent) were female and 40 (9.6 per cent) were male. No statistically significant gender difference was observed in the prevalence of either the ESP (p = 0.641) or the AHA (p = 0.064) (Table 2).
Frequences of ES and AHA by gender

AHA = aberrant hyoid apparatus; ES = elongated styloid.
The ESP was detected in 82 sides (43 right, 38 left, with one bilateral case), with a mean length of 3.66 plus or minus 0.41 cm (range: 3.03–4.88 cm). These were observed in 39 (47.6 per cent) females and 43 (52.4 per cent) males. There was no significant gender difference in the length of the ESP (p = 0.193) (Table 3).
Mean length of ES by gender

ES = elongated styloid.
A significant difference was found in the frequency of elongated styloid cases among age groups (p = 0.006) (Table 4). Elongation was most common in the greater than or equal to 60-year group (12.7 per cent) and least common in the less than 24-year group (3.1 per cent) (Figure 5). Similarly, a statistically significant difference in the mean length of ESP was observed among age groups (p < 0.001), with the greater than or equal to 60-year group showing the longest lengths (3.82 ± 0.45 cm) (Table 5).
Line graph showing the frequency of elongated styloid process (ESP) across age groups.

Frequences of ES by age groups

Note: The data presented in bold are statistically significant from the other age groups (p < 0.05).
ES = elongated styloid.
Mean length of ES by age groups

Note: The data presented in bold are statistically significant from each other (p < 0.05).
ES = elongated styloid.
The AHA was identified in 37 sides (20 right, 17 left), with an average patient age of 41.95 plus or minus 20.13 years (range: 12–85). No significant gender difference was found (p = 0.064), nor was a significant difference observed among age groups in its prevalence (p = 0.33) (Table 6).
Frequencies of AHA by age groups

All aberrant hyoid apparatuses were observed as incompletely ossified. Remarkably, in 5 (22 per cent) of the 22 aberrant cases, the contralateral side also exhibited an ESP.
The distribution of stylohyoid chain calcification types is shown in Table 7. Patterns A–B–C–D were the most common (85.3 per cent), followed by Pattern E (10.1 per cent). Other patterns were less frequently observed.
Distribution of the type of calsification stylohyoid chain by age groups and total study population

The distribution of these calcification types by age group is presented in Table 6 and Figure 6. Pattern E was increasingly prevalent with age, while Patterns A–B–C–D decreased proportionally in the older age groups.
Bar chart illustrating the distribution of stylohyoid complex calcification patterns according to age groups.

Discussion
The hyoid apparatus in mammals consists of a connected sequence of skeletal components situated in the throat region. The ossified apparatus is typically composed of four bones: the tympanohyal, stylohyal, keratohyal (or accessory keratohyal) and hypohyal.Reference Weissengruber, Forstenpointner, Peters, Kübber-Heiss and Fitch12 In humans, a completely ossified hyoid apparatus has been reported only in a few studies.Reference Hilloowala13–Reference Lee16 Of interest, anatomical configurations resembling a fully ossified hyoid apparatus, commonly found as a normal feature in various non-human mammals such as felines (e.g., lions), equines (e.g., horses), certain birds (e.g., woodpeckers) and lagomorphs (e.g., rabbits), appear only as rare anatomical variants in humans.Reference Weissengruber, Forstenpointner, Peters, Kübber-Heiss and Fitch12–Reference Lee16 This rare configuration may have both anatomical and clinical implications.
Humans are unique among vertebrates in that the tongue extends into the pharynx, whereas in other animals, the hyoid bone remains more directly embedded within the tongue body.Reference Krennmair and Piehslinger17 This evolutionary adaptation is associated with craniofacial changes during the transition to bipedalism, including the downward and backward repositioning of the face and mandible. These modifications, which facilitated an upright head posture and horizontal gaze, are encapsulated in the concept of klinorhynchy—the ventral flexure of the cranial base.Reference Assiri Ahmed, Estrugo-Devesa, Roselló Llabrés, Egido-Moreno and López-López18, Reference Altındağ, Eren, Küçükkalem and Altındağ19 Consequently, the human hyoid apparatus displays a unique spatial configuration, including the styloid process, stylohyoid ligament and lesser horn of the hyoid bone, representing a reorganisation of ancestral skeletal and soft tissue structures.
Using MDCTA, we investigated the anatomical variants and ossification patterns of the stylohyoid complex with high spatial resolution. Among 406 individuals, the normal pattern was identified in 83 per cent of cases, ESP in 12 per cent and AHA in 4 per cent. On a per-hemineck basis (n = 812), ESP and AHA were detected in 10.1 per cent and 4.6 per cent of cases, respectively. Bilateral occurrence was noted in 6.9 per cent of subjects for ESP (representing 68 per cent of all ESP cases) and in 3.7 per cent for AHA (representing 80 per cent of all AHA cases). A unilateral combination of ESP with AHA or other aberrant anatomy was observed in 1 per cent of subjects, and notably, 22 per cent of AHA cases also demonstrated a contralateral ESP.
These findings indicate that, while a normal configuration predominates, a notable minority exhibit ESP or CSC, which may hold anatomical or clinical significance. ESP was more frequently bilateral, consistent with prior findings.Reference Krennmair and Piehslinger17 Our observed ESP prevalence of 12 per cent lies in the lower-to-mid range of previous reports. Panoramic radiograph-based studies have reported ESP rates ranging from 7.1 per cent to 72–75 per cent,Reference Bagga, Kumar and Yeluri7, Reference Alpoz, Akar, Celik, Govsa and Lomcali8, Reference Assiri Ahmed, Estrugo-Devesa, Roselló Llabrés, Egido-Moreno and López-López18, Reference Altındağ, Eren, Küçükkalem and Altındağ19 likely reflecting variability in imaging methods and diagnostic thresholds. Advanced imaging studies, including cone-beam computed tomography (CBCT) and MDCTA, tend to yield more moderate prevalence rates: Yang et al. (2024) reported 33 per centReference Yang, Yuzi and Beibei20 and Triantafyllou et al. (2025) found 35 per centReference Triantafyllou, Botis, Vassiou, Vlychou, Tsakotos and Kalamatianos21 (Table 8).
Comparative prevalence of ESP and CSC according to study modalities and diagnostic criteria

CBCT = cone-beam computed tomography; CSC = calcification of stylohyoid chain; CT = computed tomography; ESP = elongated styloid process; PAN = panoramic radiograph.
Our comparatively lower ESP prevalence likely reflects the use of a stringent elongation threshold (>30 mm) and the superior contrast resolution of MDCTA, which may reduce overestimation by enabling clearer differentiation between true bony elongation and segmental calcifications within the stylohyoid chain.Reference Miracle and Mukherji22 This distinction is critical for accurate morphologic classification. Differences across studies may also arise from population-specific factors such as age and genetic background. For instance, our study included participants with a mean age of 45 years and applied a 30 mm threshold, whereas Triantafyllou et al. (2025) used a higher threshold (>33 mm) in an older study group (mean age: 60.87 years). In contrast, Yang et al. (2024) examined a younger population (20–40 years) but used a lower threshold (>25 mm).
CSC prevalence in our study (4 per cent) is consistent with prior findings. PAN studies report a wide range, from 1.7 per cent to 20.02 per cent.Reference Alpoz, Akar, Celik, Govsa and Lomcali8, Reference Altındağ, Eren, Küçükkalem and Altındağ19, Reference Rizzatti-Barbosa, Ribeiro, Silva-Concilio, Di Hipolito and Ambrosano23 MDCTA’s superior resolution likely contributes to our intermediate prevalence by better distinguishing calcified ligamentous segments. In our sample, Pattern E (ESP) was the most frequent non-normal calcification pattern (10.1 per cent), followed by Pattern K (1.2 per cent), while Patterns F, G, I and J were rare (<2 per cent each).
In our series, the mean ESP length was 3.72 plus or minus 0.44 cm in females and 3.60 plus or minus 0.38 cm in males (p = 0.193). Concerning age, mean ESP length increased progressively across groups (3.50 cm in <24-year group, 3.56 cm in 25–59-year group adults and 3.82 cm in ≥60-year group; p < 0.001). The mean age of patients with AHA was 41.9 years.
We found no statistically significant correlation between gender and ESP or CSC prevalence, in agreement with some prior reports.Reference Alpoz, Akar, Celik, Govsa and Lomcali8, Reference Assiri Ahmed, Estrugo-Devesa, Roselló Llabrés, Egido-Moreno and López-López18, Reference Altındağ, Eren, Küçükkalem and Altındağ19, Reference Ferrario, Sigurta, Daddona, Dalloca, Miani and Tafuro24 However, others have reported ESP more commonly in malesReference Bagga, Kumar and Yeluri7, Reference Triantafyllou, Botis, Vassiou, Vlychou, Tsakotos and Kalamatianos21, Reference Gözil, Yener, Calgüner, Araç, Tunç and Bahçelioğlu25 and CSC more often in females.Reference Triantafyllou, Botis, Vassiou, Vlychou, Tsakotos and Kalamatianos21, Reference Rizzatti-Barbosa, Ribeiro, Silva-Concilio, Di Hipolito and Ambrosano23 These discrepancies may arise from differences in methodology, demographics and especially age distribution. Previous studies and the present findings regarding the associations of ESP and CSC with age, gender and styloid process length are comparatively summarised in Table 9.
Comparative summary of age and gender relations of ESP and CSC and length variability of the styloid process to age and gender

CBCT = cone-beam computed tomography; CSC = calcification of stylohyoid chain; CT = computed tomography; ESP = elongated styloid process; MDCTA = multi-detector computed tomography angiography; PAN = panoramic radiograph.
Regarding age, our data revealed a significant difference in ESP prevalence across age groups, but not for CSC. This partially contrasts with previous studies, where CSC was reported to increase with age, particularly beyond 60 years,Reference Altındağ, Eren, Küçükkalem and Altındağ19, Reference Triantafyllou, Botis, Vassiou, Vlychou, Tsakotos and Kalamatianos21, Reference Rizzatti-Barbosa, Ribeiro, Silva-Concilio, Di Hipolito and Ambrosano23 suggesting a potential age-related degenerative origin. In our study, however, CSC did not exhibit a similar age-related trend, raising the possibility that its occurrence may be linked to different developmental mechanisms. Conversely, the progressive increase in ESP with age may reflect ongoing ossification driven by mechanical stress or degenerative changes. Taken together, these findings may be consistent with the possibility that ESP and CSC, while phenotypically similar, have different aetiological pathways, CSC possibly related to embryological remnants of the second pharyngeal archReference de Bakker, de Bakker, Soerdjbalie-Maikoe and Dikkers3 and ESP potentially linked to gradual postnatal ossification. Figure 7 illustrates the contrast between ESP and AHA across different age groups.
Bar chart depicting the prevalence of elongated styloid process (ESP) and aberrant hyoid apparatus (AHA).

Omnell et al. (1998) noted that ossified segments in the stylohyoid ligament develop primarily in childhood and adolescence, with rapid elongation until the end of adolescence, followed by slower growth. Ossified segments also tend to shift from superior positions in the less than 24-year group to inferior ones in older age.Reference Omnell, Gandhi and Omnell26 Similarly, Krennmair and Piehslinger (2002) observed increasing ossifications in the mid- and lower segments with age.Reference Krennmair and Piehslinger17 These observations support a dual-aetiology hypothesis: early ossification may reflect congenital remnants of the second branchial arch, whereas late-onset calcification may arise from acquired, degenerative changes. In our study, although the number of AHA cases was limited, the overall age-related distribution pattern (as demonstrated in) partially supports this dual-aetiology hypothesis.
In addition to the increasing prevalence of ESP across age groups, its mean length also showed a progressive increase with age. Statistically significant differences in styloid process length were observed particularly in the 25- to 59-year and greater than or equal to 60-year groups. The absence of a significant difference in the less than 24-year group is likely attributable to the very small sample size (n = 4), which may have limited the statistical power. This finding is compatible with the hypothesis that age-related elongation of the styloid process may be influenced by cumulative degenerative or ossific changes over time.Reference Krennmair and Piehslinger17, Reference Ferrario, Sigurta, Daddona, Dalloca, Miani and Tafuro24
Overall, our findings highlight the morphological diversity of the stylohyoid complex, ranging from elongation to ossification, likely reflecting a spectrum of developmental and pathological processes. Given their potential clinical relevance, especially in Eagle syndrome, these anatomical variants may be noteworthy in imaging interpretation and surgical planning. As high-resolution imaging becomes standard, detailed characterisation of these variants is crucial for radiologists, otolaryngologists and maxillofacial surgeons.
Clinical relevance and Eagle syndrome
Eagle syndrome manifests as cervicofacial symptoms, including throat pain, dysphagia, otalgia and a persistent foreign body sensation, typically associated with ESP. Multiple mechanisms have been proposed: mechanical irritation, neurovascular compression and post-tonsillectomy fibrosis.Reference Standring1, Reference de Bakker, de Bakker, Soerdjbalie-Maikoe and Dikkers2 However, radiographic elongation alone does not confirm Eagle syndrome without clinical correlation.Reference Nedunchezhian4
In our sample, 12 per cent had ESP and 4 per cent had AHA, representing a portion of the general population with these anatomical variants, most of whom may remain asymptomatic. Furthermore, symptom severity often does not correlate with the degree of elongation or calcification,Reference Lorman and Biggs5, Reference Bokhari, Graham and Mohseni6 reinforcing the need for multidisciplinary evaluation when Eagle syndrome is suspected. Given their proximity to critical neurovascular structures, ESP and CSC may underlie chronic orofacial pain or be misinterpreted as temporomandibular joint dysfunction, especially in cases resistant to conventional treatment.Reference de Bakker, de Bakker, Soerdjbalie-Maikoe and Dikkers3, Reference Lorman and Biggs5, Reference Bokhari, Graham and Mohseni6, Reference Raina, Gothi and Rajan10 These considerations highlight the potential importance of including such anatomical variants in the differential diagnosis of cervicofacial pain syndromes.
Study limitations
As a retrospective, single-center study based on pre-existing imaging data, our findings are subject to limitations in clinical correlation and generalisability. Additionally, the small sample size in certain subgroups may have reduced statistical power for specific comparisons.
Future directions
The age-related and bilateral trends we observed suggest that these changes may result from complex and overlapping congenital, degenerative or mechanical mechanisms. Future research should aim to clarify their aetiological pathways and clinical implications.
• Elongation or ossification of the stylohyoid chain can cause cervicofacial pain known as Eagle syndrome
• Previous radiological evaluations have largely relied on panoramic radiographs, which provide limited high-resolution anatomic detail
• Using multi detector computed tomography angiography, this study provides a population-based, high-resolution evaluation of both elongated styloid process and aberrant hyoid apparatus, quantifying prevalence, bilaterality and morphological variation
• Elongated styloid process shows an age-related increase, whereas aberrant hyoid apparatus does not, supporting distinct developmental versus degenerative mechanisms
• The study highlights that elongated styloid process and aberrant hyoid apparatus, although phenotypically similar, follow different aetiological pathways
Conclusion
Although ESP and AHA may appear phenotypically similar, our findings indicate that they are likely to originate from distinct aetiological pathways: potentially involving embryological development, evolutionary adaptations or age-related degenerative changes. The use of high-resolution MDCTA enabled a detailed analysis of ossification patterns, reinforcing the diagnostic value of advanced imaging in identifying clinically relevant variants. Such distinctions are crucial for accurate interpretation and appropriate clinical management, especially especially in the context of Eagle syndrome and orofacial pain syndromes, where these entities may contribute to a diagnostic dilemma due to overlapping clinical features and imaging findings.
Funding
This research received no specific grant from any funding agency, whether commercial or not-for-profit.
Competing interests
The authors declare no conflict of interest.
Ethıcs approval statement
The study was approved by the Non-Interventional Clinical Research Ethics Committee of Hacettepe University Faculty of Medicine (Approval number: GO 22/386).
Acknowledgements
The authors thank Hülya Erdil Çakıroğlu for preparing the medical illustration.