





Introduction
A critical aspect of everyday decisions is choosing when to exploit, or persist with a well-known option, and when to explore, or try an uncertain option with potentially higher rewards. To successfully navigate real-world scenarios, with dynamic environments and unclear risks and rewards, individuals must carefully find a balance between exploitation and exploration, that is the ‘exploration/exploitation trade-off’ (Addicott et al., Reference Addicott, Pearson, Sweitzer, Barack and Platt2017). Excessive exploration may lead to the underutilization of proven resources, whereas too little exploration can result in inflexibility and not discovering potentially more rewarding long-term options.
Explore/exploit decision-making involves a range of reward-related and cognitive processes (Lloyd, Viding, McKay, & Furl, Reference Lloyd, Viding, McKay and Furl2023), which are core psychopathological features of multiple neuropsychiatric disorders. As such, the explore/exploit trade-off has been proposed as a transdiagnostic feature across psychosis, mood, and anxiety disorders (Addicott et al., Reference Addicott, Pearson, Sweitzer, Barack and Platt2017; Jami, Abbaszade, & Vahabie, Reference Jami, Abbaszade and Vahabie2025; Lloyd et al., Reference Lloyd, Roiser, Skeen, Freeman, Badalova, Agunbiade, Busakhwe, DeFlorio, Marcu, Pirie, Saleh, Snyder, Fearon and Viding2024). The explore/exploit trade-off has been understood as an ecologically valid framework to conceptualize complex psychopathology, as a systems-level approach that integrates disparate functions and maps onto adaptive, daily-life behaviors, such as foraging (Addicott et al., Reference Addicott, Pearson, Sweitzer, Barack and Platt2017; Hagan, Aimufua, Haynos, & Walsh, Reference Hagan, Aimufua, Haynos and Walsh2024; Speers & Bilkey, Reference Speers and Bilkey2023). Major depressive disorder (MDD) is a neuropsychiatric disorder characterized by a wide range of symptoms. Deficits in motivation and goal-directed behaviors are a core feature of MDD and one of the main contributors to functional impairments. Previous work has assessed explore/exploit decision-making in MDD and suggested biases in choice behavior, although the extant literature is highly heterogeneous, with both increased and reduced exploration reported (Jami, Abbaszade, & Vahabie, Reference Jami, Abbaszade and Vahabie2025; Lloyd et al., Reference Lloyd, Roiser, Skeen, Freeman, Badalova, Agunbiade, Busakhwe, DeFlorio, Marcu, Pirie, Saleh, Snyder, Fearon and Viding2024).
Several factors influence explore/exploit decision-making and determine optimal strategies. A prominent theory is the marginal value theorem (MVT), which posits that an individual should explore when the rewards expected from exploiting fall below the background reward rate of the environment (Lloyd, Viding, McKay, & Furl, Reference Lloyd, Viding, McKay and Furl2023). In richer environments, with a higher background rate of reward, individuals should explore more extensively, whereas in poorer environments predominantly exploiting would result in higher rewards (Garrett & Daw, Reference Garrett and Daw2020). Moreover, individual factors have also been highlighted. From a neurobiological perspective, dopamine neurotransmission has been identified as a key mediator of explore/exploit decision-making (Chakroun et al., Reference Chakroun, Mathar, Wiehler, Ganzer and Peters2020). Dopamine has a well-established role in explore/exploit behavior through its role in reward learning and prediction error, but also potentially via its regulation of effort expenditure (Addicott et al., Reference Addicott, Pearson, Sweitzer, Barack and Platt2017). Within this framework, it has been theorized that dopamine modulates energy expenditure along two axes: the general levels of activity and the choices made with it; that is, deciding how available energy is expended (Beeler, Frazier, & Zhuang, Reference Beeler, Frazier and Zhuang2012). Every action has an energetic cost; therefore, choice behavior can potentially be affected by each individual’s internal energy milieu and perception of their energy environment. Extending these theoretical concepts to explore/exploit decision-making, in situations where the internal environment is perceived as healthy, exploring new opportunities and/or taking risks might be beneficial. In more adverse conditions, a more careful approach, based on the conservation of energy and exploitation of what is available, might be more adaptive (Addicott et al., Reference Addicott, Pearson, Sweitzer, Barack and Platt2017).
Conversely, evidence indicates that mesolimbic dopamine neurons express receptors for hormones that signal energy availability, including insulin, leptin, ghrelin, and glucagon-like peptide 1 (GLP-1) (Cassidy & Tong, Reference Cassidy and Tong2017; Liu & Borgland, Reference Liu and Borgland2015). This indicates that there is a pathway connecting physiological energy states to modulation of dopamine neurotransmission and, putatively, to explore/exploit behaviors. An interesting test case for this hypothesis is the behavioral effects of GLP-1 receptor agonists (GLP-1RAs). GLP-1RAs, such as semaglutide, are approved agents for the treatment of obesity and diabetes mellitus and are notable for their efficacy in promoting weight loss. Evidence indicates that this effect is achieved primarily via modulation of the reward aspects of feeding (Mansur et al., Reference Mansur, Di Vincenzo, Badulescu, Gill, Tabassum, Lopez, Rosenblat and McIntyre2024). There is interest in understanding whether these effects extend to non-food rewards, potentially broadening the application of this class of agents to primarily neuropsychiatric conditions. Within this context, we aimed to assess the effects of oral semaglutide on explore/exploit behavior in patients with MDD, in a randomized, double-blind, placebo-controlled trial. In the pre-specified primary outcome of this trial, oral semaglutide did not improve objective measures of executive function, although we documented significant improvements in attention and memory; we also did not observe any acute changes in depressive symptoms (Badulescu et al., Reference Badulescu, Gill, Shah, Brudner, Phan, Di Vincenzo, Tabassum, Armanyous, Llach, Rosenblat, McIntyre and Mansur2026). The primary objective of the present secondary and exploratory analyses was to measure the effects of treatment with semaglutide, over 16 weeks, on performance on an explore/exploit decision-making paradigm. Secondarily, we aimed to determine whether the effect of semaglutide on explore/exploit behavior in MDD is mediated by treatment-related changes in depressive symptom severity and metabolic parameters.
Materials and methods
Experimental design
This was a secondary analysis of a 16-week, double-blind, placebo-controlled, parallel-group, fixed-dose randomized clinical trial evaluating the efficacy, safety, and tolerability of adjunctive oral semaglutide for the treatment of cognitive dysfunction in MDD (NCT04466345). The study was conducted at the Mood Disorders Psychopharmacology Unit, University Health Network, a tertiary outpatient center in Toronto, Canada. The full study design, eligibility criteria, and primary cognitive outcomes have been described previously (Badulescu et al., Reference Badulescu, Gill, Shah, Brudner, Phan, Di Vincenzo, Tabassum, Armanyous, Llach, Rosenblat, McIntyre and Mansur2026). Briefly, eligible participants were outpatients aged 18–60 years with a DSM-5 diagnosis of MDD confirmed by the Mini-International Neuropsychiatric Interview, below-average performance (>1 SD below normative data) on the Trail Making Test-B, and a body mass index of 25 kg/m2 or greater. Participants were randomized 1:1, stratified by sex, to oral semaglutide (initiated at 3 mg and titrated over 8 weeks to 14 mg) or matching placebo, adjunctive to treatment as usual. No changes to the psychotropic regimen were permitted in the 4 weeks preceding randomization or throughout the trial. The study was approved by the University Health Network Institutional Ethics Board, and all participants provided written informed consent.
To assess decision-making under uncertainty, we used a four-armed bandit task (Daw et al., Reference Daw, O’Doherty, Dayan, Seymour and Dolan2006). The task included 300 trials, which were separated by a short break into two blocks of 150 trials. Participants were instructed to maximize their total rewards over a fixed number of trials. Subjects were told in advance that all points earned ($1 per point) would be paid in full after the experiment. Each trial presented four colorful slots, representing four choice options; each had a probability of yielding a reward. Under the cover, each slot was assigned a different starting value (e.g. 20, 40, 60, 80). The mean payoffs of the four slots drifted randomly across trials according to a decaying Gaussian random walk. Participants were informed that the points paid out by each slot oscillated randomly and independently over trials, so they would have to choose at any given point between exploiting the currently used slot or exploring the other three options to maximize gain. Subjects could only find information about the current worth of a slot through sampling it. Participants had a maximum of 1.5 s to indicate their choice. If no button was pressed during that time, a large red X was displayed in the center of the screen, indicating a missed trial with no points earned. After selecting the slot of their choice, the slot played an animation (2 s) and revealed the payoff (1 s). Each trial concluded with a white screen, presented for 1 s.
All individuals completed a 300-trial four-armed restless bandit task at two time points: baseline (pre-treatment) and 16 weeks (post-treatment) (Figure 1). These data were used to parameterize and evaluate latent cognitive processes driving choice behavior and their modulation by treatment. Additional outcomes include measurement of body mass index (BMI) and depressive symptom severity (with the Hamilton Depression Rating Scale – HAMD-17).
Study design and task overview. Participants with major depressive disorder were randomized to pharmacological treatment or matched placebo for 16 weeks. They completed a four-armed restless bandit task at baseline and post-treatment, with 300 trials per session. Choice behavior was modeled to quantify latent decision processes, including exploitation, directed exploration, and choice perseveration, and to examine treatment-related changes in these processes.

Figure 1. Long description
The top section outlines the study timeline across three phases.
1. Participants. 72 individuals with Major Depressive Disorder (M D D) undergo 1 to 1 randomization.
2. Baseline (Pre-treatment). Participants perform a four-armed restless bandit task consisting of 300 trials. Icons for a computer monitor (Choice behavior) and a brain (Computational modeling) indicate the data collected.
3. Intervention (16 weeks). Solid arrows lead to two groups: a Treatment Group (n equals 35) receiving pharmacological intervention and a Control Group (n equals 37) receiving a matched placebo.
4. Post-treatment (Week 16). Dashed arrows lead to a repeat of the 300-trial bandit task and data collection.
The bottom section is divided into two panels.
Left panel: Four-armed restless bandit task. A sequence shows a Choice screen with four colored boxes (blue, yellow, green, red), an Outcome screen showing a score of plus 35, and an Inter-trial interval screen with a white cross. This sequence repeats for 300 trials.
Right panel: Computational modeling (Latent cognitive processes). Three icons represent the modeled processes: a balance scale for Exploitation; a series of colored boxes with error bars and a question mark for Directed exploration; and a circular arrow around colored boxes for Choice perseveration. A dashed arrow points to the final goal: Treatment-related modulation of cognitive processes.
Computational modeling of choice behavior
To characterize the latent cognitive drivers of decision-making in the four-armed restless bandit task, participant behavior was parameterized using a trial-by-trial reinforcement-learning model. Adaptive behavior requires navigating the exploration-exploitation trade-off, balancing the selection of currently optimal options against the sampling of uncertain ones. To dissociate the computational architectures underlying this trade-off, our model integrates a belief-updating module (estimating both expected value and associative uncertainty) with a choice module that stochastically maps these latent indices onto action selection.
Belief updating
We modeled this updating with a Kalman filter, which is the Bayes-optimal learning rule for a Gaussian random walk of the kind that generated the rewards. Following prior work using the same class of choice models in restless-bandit settings (Chakroun et al., Reference Chakroun, Mathar, Wiehler, Ganzer and Peters2020), the Kalman-filter parameters governing the assumed reward dynamics were fixed at the task-generating values rather than estimated from participants’ choices. Jointly estimating these additional parameters would further increase the dimensionality and non-convexity of the likelihood, making estimation more susceptible to local optima. For each option, the filter maintains a running estimate of its value, Vt, together with an estimate of the uncertainty surrounding that value,
$ {S}_t $
 , at trial
$ t $
 . After each outcome, the value and uncertainty of the chosen option are revised in proportion to the prediction error and the current uncertainty, while the uncertainty of unchosen options grows over time.
Choice rule
On each trial, choices were modeled with a SoftMax rule in which the probability of selecting an option
$ k $
 depends on three trial-level indices: its mean estimate value Vt,k, its estimated uncertainty St,k, and a perseverative indicator It,k that equals one if the option
$ k $
 was chosen on the immediately preceding trial. Specifically, let
$ {A}_t $
 denote the arm chosen on trial
$ t $
 , denote P(At = k) be the choosing probability; we have:

Each parameter in this model isolates a distinct, mechanistically interpretable behavioral phenotype:
-
- Exploitation ( $ {\beta}_1 $
 ): Higher weights reflect greater sensitivity to differences in expected reward, increasing the influence of learned reward values on choice.
-
- Directed exploration ( $ {\beta}_2 $
): Higher values reflect greater sensitivity to uncertainty, increasing the tendency to select options with greater uncertainty. -
- Choice perseveration ( $ {\beta}_3 $
): Higher values indicate stronger choice persistence, reflected in greater dependence on the action selected on the previous trial, independent of expected value and uncertainty.


Evaluating intervention effects on behavioral phenotypes
To evaluate population-level treatment effects, we embedded the latent decision-making parameters into a joint regression framework that accounts for trait-like individual differences and nonspecific time trends. The population-level treatment effects on exploitation, directed exploration, and choice perseveration constituted the main computational analyses. We additionally conducted exploratory treatment-by-baseline interaction analyses involving age, BMI, baseline depression severity, and sex. Given the 12 moderator tests across the three computational outcomes, we applied the Benjamini–Hochberg procedure to control the false discovery rate (FDR) and report FDR-adjusted q-values alongside effect estimates and 95% confidence intervals. Further details on the model specification, model comparison, parameter-estimation procedures, and sensitivity analyses are provided in the Supplementary material. The identifiability and parameter-recovery properties of the choice model and estimation procedure have been studied previously, with identifiability established through theoretical analysis and parameter recovery evaluated through simulation studies (Zhang et al., Reference Zhang, Wang, Chen, Mansur and Sarhangian2026).
Regret analysis
We next examined whether the intervention was associated with improved task performance using normalized cumulative regret, a behavioral measure of suboptimal choice in the bandit task. Cumulative regret quantifies the loss incurred by not selecting the best available option at each trial. Because reward trajectories varied across participants, regret was normalized within each participant’s realized reward environment; details are provided in the Supplementary material. The resulting measure ranges from 0 to 1, with values closer to 0 indicating near-optimal performance and larger values indicating greater cumulative loss from suboptimal choices.
We evaluated differences in post-treatment normalized regret using ANCOVA models at Rounds 100, 200, and 300. Each model included treatment assignment as a predictor and adjusted for the corresponding pre-treatment normalized regret. These checkpoint analyses were exploratory and were evaluated using two-sided tests. To account for multiple comparisons across the three checkpoints, we applied the Holm procedure and report both nominal and Holm-adjusted p-values.
Mediation analysis
To examine whether the observed treatment effects on the explore/exploit outcomes could be statistically explained by intervention-related changes in BMI, we conducted an exploratory mediation analysis using BMI change as a potential mediator. BMI change was defined as post-treatment BMI minus baseline BMI. We first estimated a separate regression model with BMI change as the dependent variable to quantify the association between treatment assignment and BMI change. We then extended the primary outcome models by including BMI change as an additional covariate and examined whether the estimated treatment effects on exploitation and choice perseveration were attenuated after adjustment for BMI change. The treatment coefficient from the adjusted model is reported as the treatment effect adjusted for BMI change, and the corresponding indirect pathway is reported as the estimated indirect effect via BMI change.
Results
Demographic and clinical characteristics of the participants
During pre-treatment assessment (Visit 1), demographic and clinical characteristics of the 72 participants with MDD were balanced between the control (n = 37) and treatment (n = 35) groups. No significant differences at baseline were observed regarding age (p = 0.414), BMI (p = 0.308), HAMD scores (p = 0.221), or sex (p = 0.990). Fifty-four participants (75% of all recruited participants) completed the endpoint evaluation at week 16. Differences in study completion rates between treatment groups were not statistically significant (semaglutide: 28 of 35 [80%]; placebo: 26 of 37 [73%]; p = 0.483).
Heterogeneous effects
To characterize the intervention effects and their impact on patients with different characteristics, we decomposed the treatment effect into an Average Treatment Effect (ATE) and treatment-by-baseline interaction effects. The exploratory moderator analyses examined age, BMI, baseline depression severity, and sex. Because 12 treatment-by-baseline interactions were evaluated across the three computational outcomes, we report Benjamini–Hochberg FDR-adjusted q-values in addition to nominal p-values.
For exploitation (Table 1), the intervention was associated with a positive population-level treatment effect (ATE = 0.0242, p < 0.001). In the exploratory moderator analyses, higher baseline BMI was associated with a smaller treatment-related increase in exploitation (Estimate = −0.0141, 95% CI [−0.0206, −0.0076], q < 0.001), and the treatment × sex interaction was also supported after FDR adjustment (Estimate = −0.0178, 95% CI [−0.0313, −0.0046], q = 0.018). The treatment × age interaction was positive (Estimate = 0.0086, 95% CI [0.0008, 0.0163], nominal p = 0.029), but did not remain below the 5% FDR threshold (q = 0.050). The interaction with baseline depression severity was not supported after FDR adjustment.
Intervention effects on exploitation, choice perseveration, and directed exploration, moderated by baseline characteristics

Table 1. Long description
The table is divided into three sections.
Section a, Exploitation:
* Intercept: Estimate 0.0883, 95 percent C I [0.0851, 0.0915], Nominal p less than 0.001.
* Time: Estimate 0.0058, 95 percent C I [0.0039, 0.0077], Nominal p less than 0.001.
* Treatment A T E: Estimate 0.0242, 95 percent C I [0.0143, 0.0341], Nominal p less than 0.001.
* Treatment times B M I: Estimate minus 0.0141, 95 percent C I [minus 0.0206, minus 0.0076], Nominal p less than 0.001, B H dash F D R q less than 0.001.
* Treatment times age: Estimate 0.0086, 95 percent C I [0.0008, 0.0163], Nominal p 0.029, B H dash F D R q 0.050.
* Treatment times depression: Estimate minus 0.0053, 95 percent C I [minus 0.0119, 0.0013], Nominal p 0.116, B H dash F D R q 0.138.
* Treatment times sex: Estimate minus 0.0178, 95 percent C I [minus 0.0313, minus 0.0046], Nominal p 0.009, B H dash F D R q 0.018.
Section b, Choice perseveration:
* Intercept: Estimate 0.4993, 95 percent C I [0.4331, 0.5656], Nominal p less than 0.001.
* Time: Estimate 0.3156, 95 percent C I [0.2635, 0.3676], Nominal p less than 0.001.
* Treatment A T E: Estimate 0.3017, 95 percent C I [0.0633, 0.5402], Nominal p 0.013.
* Treatment times B M I: Estimate 0.2368, 95 percent C I [0.0961, 0.3775], Nominal p 0.001, B H dash F D R q 0.002.
* Treatment times age: Estimate minus 0.5520, 95 percent C I [minus 0.696, minus 0.4075], Nominal p less than 0.001, B H dash F D R q less than 0.001.
* Treatment times depression: Estimate 0.3829, 95 percent C I [0.2235, 0.5424], Nominal p less than 0.001, B H dash F D R q less than 0.001.
* Treatment times sex: Estimate minus 0.3073, 95 percent C I [minus 0.6035, minus 0.0111], Nominal p 0.042, B H dash F D R q 0.063.
Section c, Directed exploration:
* Intercept: Estimate minus 0.0139, 95 percent C I [minus 0.0282, 0.0029], Nominal p 0.080.
* Time: Estimate minus 0.0130, 95 percent C I [minus 0.0241, minus 0.0046], Nominal p 0.009.
* Treatment A T E: Estimate 0.0619, 95 percent C I [0.0132, 0.1106], Nominal p 0.013.
* Treatment times B M I: Estimate minus 0.0137, 95 percent C I [minus 0.0442, 0.0168], Nominal p 0.379, B H dash F D R q 0.379.
* Treatment times age: Estimate minus 0.0291, 95 percent C I [minus 0.0584, 0.0018], Nominal p 0.058, B H dash F D R q 0.077.
* Treatment times depression: Estimate 0.0159, 95 percent C I [minus 0.0141, 0.0459], Nominal p 0.299, B H dash F D R q 0.316.
* Treatment times sex: Estimate minus 0.1025, 95 percent C I [minus 0.1615, minus 0.0435], Nominal p 0.001, B H dash F D R q 0.002.
Note: Treatment-by-baseline interaction analyses were exploratory and are interpreted primarily based on effect estimates and 95% confidence intervals. BMI, age, and depression severity were mean-centered prior to analysis. Nominal p-values are reported together with Benjamini–Hochberg false discovery rate (FDR)-adjusted q-values across the 12 treatment-by-baseline interaction tests spanning the three computational outcomes. FDR adjustment was not applied to the intercept, time, or average treatment effect terms.
For choice perseveration (Table 1), there was a positive population-level treatment effect (ATE = 0.3017, p = 0.013). Exploratory moderator analyses suggested heterogeneity associated with baseline BMI (Estimate = 0.2368, q = 0.002), age (Estimate = −0.5520, q < 0.001), and depression severity (Estimate = 0.3829, q < 0.001). The treatment × sex interaction was nominally significant (p = 0.042) but did not remain below the FDR threshold (q = 0.063). These moderator findings are interpreted as hypothesis-generating given the modest sample size.
Furthermore, for directed exploration (Table 1), the main effect of time indicated lower directed exploration across sessions (Estimate = −0.0130, p = 0.009), while the population-level treatment effect was positive (ATE = 0.0619, p = 0.013). Among the exploratory moderators, the treatment × sex interaction remained supported after FDR adjustment (Estimate = −0.1025, q = 0.002), consistent with a smaller treatment-associated increase among male participants. The interactions with baseline BMI, age, and depression severity were not supported after FDR adjustment.
Importantly, the simultaneous increase in these three parameters does not imply a simple shift from exploration toward exploitation, or vice versa. In our model, exploitation and directed exploration are not opposite ends of a single dimension. Rather, the increases in exploitation (
$ {\beta}_1 $
 ) and directed exploration (
$ {\beta}_2 $
 ) reflect greater sensitivity to two distinct sources of information used in choice, namely expected value and uncertainty, respectively. While the increase in choice perseveration (
$ {\beta}_3 $
 ) reflects stronger dependence of current choice on the choice made on the previous trial. Taken together, the treatment-related behavioral pattern is characterized by greater sensitivity to both learned value and uncertainty, together with greater choice persistence.
Behavioral outcome: Normalized regret
As shown in Figure 2, the two groups showed similar regret trajectories before treatment. After treatment, the treatment group exhibited lower normalized regret than the control group across task rounds.
Normalized regret trajectories across groups. Average normalized cumulative regret is shown for the treatment and control groups in the pre-treatment and post-treatment sessions. Shaded bands indicate ±1 standard error. Lower values indicate better task performance.

Figure 2. Long description
The x-axis is labeled Round, with increments from 50 to 300. The y-axis is labeled Normalized Regret (0 = optimal, 1 = worst-case), ranging from 0.125 to 0.300. Four lines with shaded error bands are shown.
* Control Pre-Treatment (blue line with circles): Starts at the highest regret of approximately 0.268 at round 50 and follows a steep downward curve, leveling off near 0.210 by round 300.
* Control Post-Treatment (blue dashed line with squares): Starts at 0.230 and remains relatively flat, ending slightly higher than the pre-treatment group at 0.212.
* Treatment Pre-Treatment (red line with circles): Starts at 0.240 and decreases steadily, reaching a plateau of approximately 0.187 by round 300.
* Treatment Post-Treatment (red dashed line with squares): Maintains the lowest regret throughout, starting at 0.161 and fluctuating slightly to end at 0.150.
Overall, the treatment group shows lower regret than the control group, and the post-treatment sessions show lower regret than pre-treatment sessions for the treatment group, while the control group remains similar across sessions.
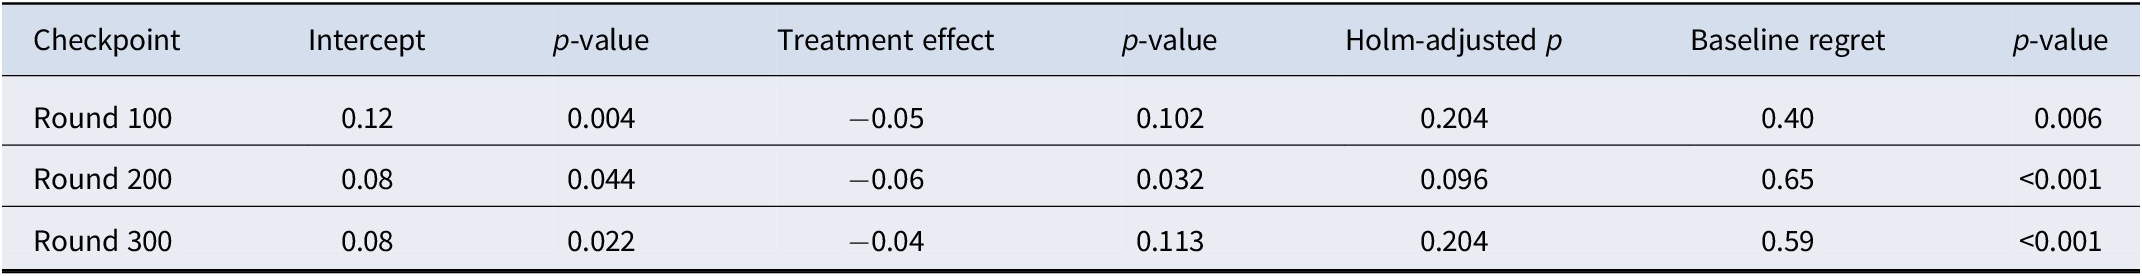
The estimated adjusted treatment effects using the ANCOVA models were negative at all three checkpoints (Table 2), indicating lower post-treatment regret in the treatment group. The estimated reductions were −0.05, −0.06, and −0.04 at Rounds 100, 200, and 300, respectively. Using two-sided tests, the treatment effect was nominally significant at Round 200 (p = 0.032), while the corresponding p-values at Rounds 100 and 300 were 0.102 and 0.113. After Holm adjustment across the three checkpoint analyses, the adjusted p-values were 0.204, 0.096, and 0.204, respectively. Baseline regret was positively associated with post-treatment regret at all three checkpoints. Overall, the treatment-effect estimates showed a consistent pattern of lower normalized regret following treatment, although the statistical evidence was modest after accounting for multiple comparisons. Unlike the computational choice model, which leverages the full trial-by-trial choice trajectories, the regret analysis is based on participant-level summary measures at each checkpoint, resulting in more limited information for estimating treatment differences.
Adjusted treatment effects on post-treatment normalized regret at task checkpoints

Table 2. Long description
The table consists of eight columns and three data rows representing task checkpoints at Round 100, Round 200, and Round 300.
Column headers from left to right are: Checkpoint, Intercept, p-value, Treatment effect, p-value, Holm-adjusted p, Baseline regret, and p-value.
Data by row:
* Round 100: Intercept 0.12 (p 0.004), Treatment effect minus 0.05 (p 0.102), Holm-adjusted p 0.204, Baseline regret 0.40 (p 0.006).
* Round 200: Intercept 0.08 (p 0.044), Treatment effect minus 0.06 (p 0.032), Holm-adjusted p 0.096, Baseline regret 0.65 (p less than 0.001).
* Round 300: Intercept 0.08 (p 0.022), Treatment effect minus 0.04 (p 0.113), Holm-adjusted p 0.204, Baseline regret 0.59 (p less than 0.001).
Negative treatment effects indicate lower adjusted post-treatment regret in the treatment group relative to the control group. Values are derived from A N C O V A models.
Note: Values are from ANCOVA models predicting post-treatment normalized regret at each checkpoint, adjusting for the corresponding pre-treatment normalized regret. Negative treatment effects indicate lower adjusted post-treatment regret in the treatment group relative to the control group. Nominal two-sided p-values are reported together with Holm-adjusted p-values accounting for multiple testing across the three checkpoint-specific treatment effects. Lower normalized regret indicates better task performance.
Mediation analysis of treatment effects
The intervention was associated with a significant reduction in BMI compared with placebo (estimate = −0.995, p < 0.001). After additionally adjusting for BMI change, the estimated treatment effects are presented in Table 3.
Mediation analysis of treatment effects on exploitation, choice perseveration, and directed exploration

Table 3. Long description
A complex data table divided into three sections: (a) Exploitation, (b) Choice perseveration, and (c) Directed exploration. Each section lists predictors including Intercept, Time, Treatment effect adjusted for B M I change, and interactions between Treatment and B M I, age, depression, and sex, as well as the Indirect effect via B M I change. The columns provide the Estimate, 95% C I, Nominal p-value, and B H - F D R q-value.
Section (a) Exploitation: Significant interactions include Treatment times B M I (Estimate -0.0148, q < 0.001), Treatment times age (Estimate 0.0091, q = 0.044), and Treatment times sex (Estimate -0.0167, q = 0.030).
Section (b) Choice perseveration: Significant interactions include Treatment times B M I (Estimate 0.1846, q = 0.030), Treatment times age (Estimate -0.5147, q < 0.001), and Treatment times depression (Estimate 0.3686, q < 0.001).
Section (c) Directed exploration: Significant interactions include Treatment times age (Estimate -0.0312, q = 0.048) and Treatment times sex (Estimate -0.1129, q < 0.001). The indirect effect via B M I change is not statistically significant across any of the three behavioral measures.
Note: BMI change was z-score standardized prior to analysis. Significant indirect effects indicate mediation through treatment-related BMI reduction. BMI, age, and depression severity were mean-centered prior to analysis.
For exploitation (Table 3), the direct treatment effect remained significantly positive after adjustment for BMI change (Estimate = 0.0225, p < 0.001), whereas the indirect effect through BMI change was not statistically significant (Estimate = −0.0012, p = 0.685). Thus, the observed treatment association with exploitation was not statistically explained by measured BMI change in this sample.
For choice perseveration (Table 3), the treatment effect after adjustment for BMI change was positive, although its 95% CI crosses zero. The estimated indirect effect through BMI change was negative but did not reach statistical significance (Estimate = −0.1193, p = 0.053). However, given the modest sample size, this finding should be considered suggestive but inconclusive. The present analysis does not provide sufficient evidence to rule out a mediating role of BMI change in the treatment effect on choice perseveration. For directed exploration (Table 3), the treatment effect remained significantly positive after adjustment for BMI change (Estimate = 0.0874, p = 0.003), whereas the estimated indirect effect was not statistically significant (Estimate = 0.0199, p = 0.121).
Taken together, the observed treatment associations with exploitation and directed exploration were not statistically explained by measured BMI change in this sample. For choice perseveration, however, the indirect effect approached the conventional significance threshold, and the present analysis does not rule out a potential mediating role of BMI change.
Discussion
Overall, results indicate that treatment with semaglutide modulates explore/exploit behaviors in patients with MDD. Compared to placebo, treatment with semaglutide resulted in increased exploitation, directed exploration, and perseveration. Following treatment, patients with MDD were better able to monitor and/or choose the most rewarding options in uncertain situations. In our model, this could reflect an improvement in outcome monitoring, with a more accurate representation of the value estimate for each option learned from one trial to the next; and/or value-based choice, with a stronger bias toward options with higher learned expected values.
Semaglutide-treated participants displayed a shift toward a more exploitative decision strategy, but, interestingly, paired with an increase in directed exploration. Previous work has demonstrated that uncertainty tends to increase over time during a series of repeated choices, either perseverative or exploitative (Chakroun et al., Reference Chakroun, Mathar, Wiehler, Ganzer and Peters2020). Directed exploration, defined herein as the exploration of a choice with high uncertainty, is an active process to obtain new information, and thus reduce uncertainty. Exploratory choices are costly, by requiring a proactive/effortful choice, as well as incurring an opportunity cost (Brown, Hallquist, Frank, & Dombrovski, Reference Brown, Hallquist, Frank and Dombrovski2022; Nair et al., Reference Nair, Niyogi, Shang, Tabrizi, Rees and Rutledge2023). We have previously reported that treatment with semaglutide resulted in an improvement in measures of attention and memory in this population (Badulescu et al., Reference Badulescu, Gill, Shah, Brudner, Phan, Di Vincenzo, Tabassum, Armanyous, Llach, Rosenblat, McIntyre and Mansur2026). We have also recently explored the effects of treatment on effort-based decision-making, and observed an increase in the willingness to exert effort, but only for rewards with higher expected values, and a reduction in the perceived cost of effort (Gill et al., Reference Gill, Badulescu, Shah, Brudner, Phan, Di Vincenzo, Tabassum, Thanarajah, Llach, Rosenblat, McIntyre and Mansur2026). It is conceivable then that the behavioral signature on the explore/exploit trade-off observed here represents both the improved ability to track and update the many potential options, and the facilitation to make effortful choices, in semaglutide-treated patients.
Within this context, the finding of increased perseveration with semaglutide treatment is counter-intuitive. Generally, perseveration is considered to be less effortful than switching; the idea being that repeating a previous action is less demanding than initiating a goal-directed action (Daw, Reference Daw2018). Nonetheless, there are alternative models, such as considering perseveration as a strategy aimed at simplifying decision-making policies, or the probabilistic mapping from states to actions (Gershman, Reference Gershman2020). In this model, policy complexity is distinct from computational complexity, which corresponds to how difficult it is to perform a task. As such, learning and implementing a simple, or compressed, policy, such as a tendency to repeat the previous action, can be adaptive, freeing cognitive resources to consider other inputs to guide action selection, and thus not sacrificing potential rewards (Brown, Hallquist, Frank, & Dombrovski, Reference Brown, Hallquist, Frank and Dombrovski2022; Lai & Gershman, Reference Lai and Gershman2024; Legler et al., Reference Legler, Cuevas Rivera, Schwobel, Wagner and Kiebel2025). A previous study has reported that patients with Parkinson’s disease showed a reduction in perseveration in a four-armed restless bandit task, which was correlated with apathy scores, and conversely displayed a signature of increased random exploratory and decreased exploitative choices (Gilmour et al., Reference Gilmour, Mackenzie, Feile, Tayler-Grint, Suveges, Macfarlane, Macleod, Marshall, Grunwald, Steele and Gilbertson2024). These converging results are interesting and provide further context to the interpretation above, but it should be noted that Parkinson’s disease has a significantly distinct neurobiology, and the aforementioned study was a cross-sectional assessment, not involving any intervention.
It is also notable that while semaglutide effects on explore/exploit behavior were moderated by baseline characteristics, they were not mediated by weight loss. Metabolic dysfunction has been consistently and independently associated with cognitive dysfunction and impaired reward processing in MDD (Gill et al., Reference Gill, Badulescu, Di Vincenzo, Tabassum, McKenzie, Shah, Amin, Llach, Rosenblat, McIntyre and Mansur2025; Restivo et al., Reference Restivo, McKinnon, Frey, Hall, Syed and Taylor2017). With the well-known and clinically significant metabolic effects of GLP-1RAs, which were observed in this patient population (Badulescu et al., Reference Badulescu, Gill, Shah, Brudner, Phan, Di Vincenzo, Tabassum, Armanyous, Llach, Rosenblat, McIntyre and Mansur2026), it is possible that the effects of GLP-1RAs on behavioral outcomes are a consequence of metabolic improvement, rather than a direct effect of GLP-1 receptor activation. Indeed, in our previous work, we documented that semaglutide’s effects on global cognition were fully mediated by weight loss (Badulescu et al., Reference Badulescu, Gill, Shah, Brudner, Phan, Di Vincenzo, Tabassum, Armanyous, Llach, Rosenblat, McIntyre and Mansur2026). The exploratory mediation analysis did not provide evidence that BMI change statistically explained the observed treatment associations with exploitation and directed exploration. However, given the modest sample size and the fact that BMI change may not capture the full range of metabolic effects, these analyses do not rule out metabolic mediation.
This is a secondary, exploratory analysis of a randomized clinical trial. Other study limitations include a modest sample size (N = 72), which limits the statistical power necessary to detect more subtle treatment effects or interactions between metabolic factors and decision-making outcomes. Specifically, the sample was likely underpowered to detect mediation effects. Participants were receiving mixed pharmacotherapy regimens. There are no meaningful pharmacological interactions between semaglutide and most psychotropic medications. Nonetheless, heterogeneity in patients’ pharmacological regimen precluded the analysis of the potential specific effects of each class of agents. The study sample might also not be generalizable to the broader population with MDD, as only overweight/obese patients with pre-treatment evidence of cognitive dysfunction were enrolled. Finally, evidence indicated a high likelihood of functional unblinding due to gastrointestinal side effects and noticeable weight loss in the semaglutide group, which may impact study outcomes (Badulescu et al., Reference Badulescu, Gill, Shah, Brudner, Phan, Di Vincenzo, Tabassum, Armanyous, Llach, Rosenblat, McIntyre and Mansur2026).
In conclusion, our study indicates that treatment with semaglutide significantly modulates explore/exploit decision-making in patients with MDD. Treatment with semaglutide resulted in increased exploitation, directed exploration, and perseveration in a four-armed restless bandit task, compared to placebo. To our knowledge, this represents the first clinical trial investigating the effect of a GLP1RA on explore/exploit behaviors in a clinical sample.
Supplementary material
The supplementary material for this article can be found at http://doi.org/10.1017/S0033291726106412.
Funding statement
This study was supported by grant number 20-24 from the Physicians’ Services Incorporated (PSI) Foundation.
CDL has received the support of a fellowship from ‘la Caixa’ Foundation (ID 100010434). The fellowship code is ‘LCF/BQ/EU22/11930062’. CDL has also received CME-related honoraria, or consulting fees, from CASEN Recordati, Organon, Lundbeck, and the Academy for Continuing Medical Education (Akademijazakme).
JDR has received research grant support from the Canadian Institute of Health Research (CIHR), Physician Services, Inc. (PSI) Foundation, Labatt Brain Health Network, Brain and Cognition Discovery Foundation (BCDF), Canadian Cancer Society, Canadian Psychiatric Association, Academic Scholars Award, American Psychiatric Association, American Society of Psychopharmacology, University of Toronto, University Health Network Center for Mental Health, Joseph M. West Family Memorial Fund, and Timeposters Fellowship and industry funding for speaker/consultation/research fees from iGan, Boehringer Ingelheim, Janssen, Allergan, Lundbeck, Sunovion, Braxia Health, Braxia Scientific Corp., and COMPASS.
RSM has received research grant support from CIHR/GACD/National Natural Science Foundation of China (NSFC) and the Milken Institute; speaker/consultation fees from Lundbeck, Janssen, Alkermes, Neumora Therapeutics, Boehringer Ingelheim, Sage, Biogen, Mitsubishi Tanabe, Purdue, Pfizer, Otsuka, Takeda, Neurocrine, Sunovion, Bausch Health, Axsome, Novo Nordisk, Kris, Sanofi, Eisai, Intra-Cellular, NewBridge Pharmaceuticals, Viatris, Abbvie, Atai Life Sciences. Dr. Roger McIntyre is the CEO of Braxia Scientific Corp.
RBM has received research grant support from the CIHR, the PSI Foundation, and the Baszucki Brain Research Fund, and an Academic Scholars Award, Department of Psychiatry, University of Toronto.
Competing interests
The PSI Foundation had no role in the design and conduct of the study; collection, management, analysis, and interpretation of the data; preparation, review, or approval of the manuscript; and decision to submit the manuscript for publication.
All other authors report no biomedical financial interests or potential conflicts of interest.
Ethical standards
The authors assert that all procedures contributing to this work comply with the ethical standards of the relevant national and institutional committees on human experimentation and with the Helsinki Declaration of 1975, as revised in 2008.




 Open access

