INTRODUCTION
Arterial spin labeling (ASL) is a developing magnetic resonance method to measure cerebral perfusion (Detre et al., 1992; Alsop, 2005). ASL applies a magnetic label to the water molecules of flowing blood in a region proximal to the imaging slice. As the magnetic label enters the imaging slice it exchanges with tissue water and slightly alters the image contrast. The magnetic label is delivered to the image slice at a rate determined by local cerebral blood flow (CBF) (Buxton et al., 1998; Calamante et al., 1999). Typically the image acquired after magnetic tagging is subtracted from a control image to remove the effects of static magnetization and to control for imaging effects of the tagging experiment unrelated to the rate of blood flow. Figure 1 shows the high resolution of ASL CBF maps with the gyral anatomy of cortical flow clearly visible. Part I of this paper, Alsop's chapter, and the original sources referenced earlier provide additional detail about ASL methods (Alsop, 2005; Liu & Brown, 2007, this issue).

Perfusion images from a FAIR sequence. Voxels were resliced into 1 mm3 and smoothed by an amount of 3.44 mm full width half maximum, the original in-plane pixel length. A threshold was set to emphasize cortical flow.
Part II of this paper summarizes the current findings from studies using ASL to investigate pathophysiology, diagnostic specificity, and treatment outcome in neuropsychiatric disorders. It also reviews the use of ASL to study normal brain function. The papers involving clinical studies were found by searching PubMed using the search terms “Arterial Spin Labeling” and the clinical condition described in the heading of each of the later sections (www.pubmed.gov). Papers written in English and published through the middle of 2006 were reviewed. We report the results of all studies involving patients and selected studies involving animals. Most technical papers focusing on ASL methods identified in the current PubMed search were discussed in Part I of this review (Liu & Brown, 2007, this issue).
Healthy Brain Function
Studies using ASL perfusion to localize the brain's response to changes of behavioral status are reviewed in Table 1. The studies reviewed include behavioral validation studies of ASL perfusion, studies comparing ASL perfusion with other functional imaging techniques, comparative studies of ASL and blood oxygen level dependent (BOLD) contrast as measures of brain response, and pharmacological studies.
Arterial spin labeling findings during behavioral challenge

Validation studies used the known functional organization of the brain to determine how well ASL perfusion methods can localize brain function. Motor studies uniformly have found ASL CBF changes in the primary motor cortex, and visual stimulation studies have found changes in the occipital cortex (Aguirre et al., 2002; Brown et al., 2003; Garraux et al., 2005; Gollub et al., 1998; Li et al., 2000; Restom et al., 2006; Tjandra et al., 2005; Wang et al., 2003; Yongbi et al., 2002). Motor activation effects are larger at 3.0 T than at 1.5 T, presumably caused by the greater signal to noise of higher field magnets (Yongbi et al., 2002). Cognitive manipulations have also produced expected lateralized and localized ASL CBF changes with language generation activating Broca's area, visual attention activating anterior cingulate and right prefrontal cortex, and working memory activating the prefrontal and parietal cortex (Kemeny et al., 2005; Kim et al., 2006; Yee et al., 2000; Ye et al., 1998). The spatial activation patterns for ASL CBF obtained during finger tapping or visual stimulation have been shown to agree well with cerebral blood volume changes measured by gadolinium bolus tracking (Li et al., 2000). Moreover, ASL CBF correlates with total and oxy-hemoglobin across time points of a finger-tapping task, as measured by near-infrared spectroscopy (Huppert et al., 2006). In these early studies the spatial and temporal properties of ASL CBF correlate well with other hemodynamic measures of brain activity and with expected patterns of activation based on the known functional organization of the brain.
A detailed comparison of ASL perfusion and BOLD signals was presented in Part I (Liu & Brown, 2007, this issue). The papers reviewed here provide further guidance about when to use each of these methods to study healthy brain function. Unless corrected for physiological confounds, ASL signals are prone to signal variation that reduce their sensitivity to behavioral manipulations (Restom et al., 2006). Perhaps for this reason ASL CBF is less sensitive to parametric manipulations of task demands than is BOLD contrast (Rao et al., 2000). ASL maps also tend to exhibit smaller activation regions than BOLD maps (Mildner et al., 2005; Tjandra et al., 2005). The smaller spatial extent of the ASL maps might be because of their decreased sensitivity to small activation changes or to their improved signal localization (Liu & Brown, 2007, this issue). In some experiments, the advantage of BOLD over ASL measures is reduced by the greater between-subject variation of BOLD measures compared with ASL (Wang, et al., 2003). Even though BOLD contrast is typically more sensitive to changes of behavioral state than ASL CBF, especially when the ASL signal is uncorrected for physiological variation, the advantage of BOLD contrast is limited to paradigms where the delay between the two behavioral conditions of interest is less than one minute. As the interval between two behavioral manipulations increases and exceeds two minutes, ASL perfusion is often more sensitive to changes in brain response than are BOLD signals (Aguirre et al., 2002; Wang et al., 2003). The relative stability of ASL perfusion to long-term temporal effects makes ASL an effective method to study naturalistic longitudinal changes in mood, mental set or drive, or to study interventions. ASL CBF is also less prone than BOLD to false activations during overt speech paradigms, apparently because ASL is less sensitive to susceptibility artifacts caused by the air volume dynamics involved in speaking (Kemeny et al., 2005).
Pharmacological manipulations, such as acetazolamide, that alter brain CBF without altering brain metabolism, affect the magnitude of the BOLD response (Brown et al., 2003). However, pharmacological manipulations that have little impact on brain blood flow, such as methylphenidate, have little impact on BOLD response in brain areas not targeted by the drug (Rao et al., 2000). The impact of drugs that globally affect CBF and brain metabolism are more difficulty to interpret. For example, Gollub and colleagues reported that although cocaine infusion reduced CBF by 14%, BOLD response in the occipital cortex to flickering checkerboard was not significantly altered following cocaine infusion (Gollub et al., 1998). One might conclude from these results that drug-induced alterations in CBF need not affect the BOLD response. Yet, these findings are also compatible with a down regulation of brain metabolism, a potential effect of cocaine administration (Gollub et al., 1998; London et al., 1990).
Neuropsychiatric Disorders
The following section discusses ASL in studies of adults. Wang and Licht's (2006) recent review discusses ASL in studies of children.
Cerebrovascular Disease
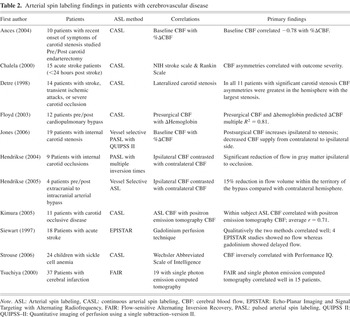
Studies using ASL to investigate CBF have correlated ASL values with clinical, behavioral or other imaging variables or have used ASL to monitor cerebrovascular surgery (See Table 2). Chalela and colleagues (2000) used continuous ASL to study the clinical correlates of flow asymmetries in 15 patients with acute unilateral stroke. See Part 1 for a discussion of continuous ASL (CASL) and pulsed ASL (PASL) (Liu & Brown, 2007, this issue). Eleven of the 15 patients had visible CBF deficits corresponding to the patient's lateralized symptoms. CBF asymmetries correlated significantly with symptom severity at admission (National Institutes of Health Stroke Scale scores) and with daily functioning at 30 days post-stroke (Rankin Scale) (Bonita & Beaglehole, 1988; Chalela et al., 2000).
Arterial spin labeling findings in patients with cerebrovascular disease

Studies of patients with carotid artery occlusion or with high-grade stenosis have often been used to validate CBF techniques (e.g., Ewing et al., 1987; Yamauchi et al., 1996). A study using CASL to measure CBF found flow asymmetries pointing to the involved hemisphere in all 11 patients with clinically significant stenosis (Detre et al., 1998). These results are especially encouraging when considering that CBF studies of carotid artery occlusion or high-grade stenosis are complicated by collateral flow, which can lengthen the transit-time associated with the delivery of a tracer to a region of interest (Ewing et al., 1987; Cosottini et al., 2005). To correct for variable transit times, Hendrikse and co-authors used single-slice, pulsed ASL to acquire flow images at six inversion times ranging from 200 to 1600 msec in nine patients with carotid artery occlusion (Hendrikse et al., 2004). Patients had transient ischemic attacks or minor strokes compatible with ischemia within the vascular territory of the occluded carotid artery. All patients had less than 30% stenosis in the contralateral carotid artery. Except for the two most extreme inversion times, the perfusion-weighted signal in gray matter was less in the hemisphere ipsilateral to the occlusion compared with the contralateral hemisphere or with control values. Curve fitting to the difference images (control minus tag) acquired across inversion times provided a single estimate of CBF, which was significantly lower in the ipsilateral hemisphere compared with flow in the hemisphere opposite the occlusion. CBF estimated from multiple inversion times yielded flow values comparable to values based on previously validated CBF methods (Hendrikse et al., 2004).
Kimura and colleagues (2005) used continuous ASL and CO2 PET to assess regional CBF in 11 patients with unilateral occlusive disease. The authors not only calculated perfusion maps for ASL and PET methods separately, but also estimated transit delays from combined ASL and PET measures. For each subject, ASL CBF was correlated with PET CBF across 48 ROIs. The average correlation over subjects was 0.71. However, the average ASL CBF values were significantly smaller than PET CBF within gray matter ROIs on the affected side. An analysis of the arterial transit times performed by the current reviewers found that the transit times were significantly greater in the involved hemisphere, t(10) = 2.80, p = .019. Moreover, we found that the difference in arterial transit times between the affected and non-affected hemispheres correlated 0.60, p = .051 with the PET/ASL CBF difference in the involved hemisphere. The underestimation of CBF by ASL in the involved hemisphere appears to be due longer transit times, as argued by Kimura and colleagues (2005). Nonetheless, these results show fairly good agreement between ASL and PET CBF measures for patients with unilateral occlusions. Similar agreement has been reported for ASL and SPECT CBF measures in subacute infarction (Tsuchiya et al., 2000).
Ances et al. (2004) used multislice, CASL to study CBF in 10 symptomatic patients with carotid stenosis before and three months after carotid endarterectomy. Vascular regions of interest were drawn on the CBF images. Carotid endarterectomy did not alter global blood flow. Data about CBF changes within the distribution of the operated carotid artery were not provided. The authors stated that when CBF from the anterior and middle cerebral arteries were combined, baseline CBF correlated significantly (r = −.78) with the change in CBF following surgery, whereas the correlation of baseline flow with flow change was nonsignificant (r = .25) in the posterior distribution. Any conclusions to be drawn from these change scores must be tempered by the confounding of baseline scores with simple change scores. Because simple change scores include the baseline in their definition and because measurement error produces regression to the mean, baseline scores can be inversely correlated with change scores even if baseline scores and follow-up scores are randomly generated (Cohen et al., 2003). Using selective labeling of each carotid artery, a recent study of carotid endarterectomy found increased CBF in the middle cerebral artery territory ipsilateral to carotid stenosis and decreased contralateral supply to the ipsilateral side (Jones et al., 2006). Such results call into question the usefulness of global CBF measures to track the hemodynamic effects of cerebrovascular surgery.
Hendrikse and co-authors (2005) used vessel selective ASL to study CBF in seven patients before and after extracranial to intracranial (ECIC) arterial bypass. A novel aspect of this study was the selective labeling of flow within the grafted vessel. Three patients were treated for giant aneurysms, and four were treated for symptoms related to internal carotid occlusion. A turbo transfer insensitive labeling method was used to acquire flow images at inversion times ranging from 200 ms to 2600 ms. ASL CBF measured within the operated and contralateral hemispheres and within the basilar circulation was within the normal range, supporting PET studies that found flow normalization following ECIC arterial bypass (Gibbs et al., 1987; Marshall et al., 2002).
Brain Tumors
MR perfusion studies have focused primarily on the use of ASL to distinguish among tumor types and to monitor treatment change. The current literature on ASL studies of brain tumors is summarized in Table 3. ASL perfusion shows consistently higher CBF values in high-grade than low-grade gliomas (Warmuth et al., 2003; Weber et al., 2006; Wolf et al., 2005). The difference in flow level reliably distinguishes low-grade and high-grade gliomas at sensitivity rates ranging from 79% to 100% and specificity rates ranging from 50% to 100%. One study found that a relative measure of tumor CBF separated untreated grade III and IV gliomas from grade I and II gliomas at 100% accuracy (Warmuth et al., 2003). ASL CBF appeared most valid in distinguishing among tumor types when flows were age-adjusted (Warmuth et al., 2003). Increased CBF can also distinguish higher-grade gliomas from lymphomas, whereas increased peri-tumoral flow in non-enhancing T2-hyperintense regions of glioblastomas can distinguish these primary brain tumors from metastatic tumors (Weber et al., 2006). Brain normalized flow within a metastasis seems to be intermediate, with flow values between those of high-grade and low-grade gliomas (Warmuth et al., 2003).
Arterial spin labeling findings in patients with brain tumors

The accuracy of ASL perfusion measures for the differentiation of tumor types has been compared with the accuracy of dynamic susceptibility weighted contrast (DSWC) measures of perfusion and volume. DSWC involves using rapid MR imaging techniques to track an injected paramagnetic contrast agent over time (Alsop, 2005). The delivery of the contrast agent temporally decreases the MR signal on T2* weighted images (Alsop, 2005). Plots of the change in signal over time provide information about mean transit time, cerebral blood flow, and cerebral blood volume (CBV). As commonly used, DSWC measures mean transit time in absolute units, and relative values of CBF and CBV (Alsop, 2005). DSWC has been used successfully to predict tumor progression (Law et al., 2006). Consequently, DSWC has become an important criterion against which new MR flow methods should be validated in brain tumor patients.
As seen in Table 3, DSWC enhanced MRI values correlated 0.83 with PASL CBF within the tumor region (Warmuth et al., 2003). DSWC correlated .88 and .89 with two different PASL methods when flows were measured in healthy brain regions of patients with brain metastases (Weber et al., 2003). Moreover, ASL and DSWC distinguish high and low grade gliomas at the same significance level (Warmuth et al., 2003). In comparison with DSWC, ASL provides quantitative CBF values that are unrelated to the disruptions of blood-brain barrier, does not require the injection of a contrast agent, and requires little post-processing so that images are rapidly available for clinical interpretation. DSWC has better signal to noise, permits the acquisition of a greater number of slices, and provides information about tumor blood volume and vessel permeability (Warmuth et al., 2003; Weber et al., 2003).
Weber and colleagues (2004) used FAIR Q2TIPS, a type of pulsed ASL, and DSWC to measure CBF prior to stereotactic radiosurgery and 6, 12, and 24 weeks post-surgery in a sample of 25 patients with brain metastasis. Patients were divided into those showing tumor remission, tumor stability or tumor progression at six months. Baseline regional CBF did not predict tumor response. However, a reduction in the ratio of tumor CBF to contralateral gray matter CBF at six weeks predicted tumor responders with 100% sensitivity and specificity (Weber et al., 2004). ASL was more accurate in predicting outcome than were MRI measurements of tumor volume. DSWC had sensitivity and specificity values similar to ASL values. In a related study, ASL CBF measured in healthy brain tissue did not change after stereotactic radiosurgery to treat metastatic tumors (Weber et al., 2003). Although the results of the Weber et al. (2004) study confirmed ASL's potential to predict and to monitor treatment response in brain tumor, only three patients were non-responders, thereby limiting the study's generalizability.
Alzheimer's Disease
A preliminary study using pulsed ASL demonstrated decreased parieto-occipital and temporo-occipital perfusion compared with controls. Moreover, parieto-occipital hypoperfusion correlated with increasing dementia severity (Sandson et al., 1996). A subsequent ASL study demonstrated significant temporal, parietal, frontal, and posterior cingulate hypoperfusion in AD subjects. In this cohort, posterior parietal and posterior cingulate hypoperfusion correlated with increasing dementia severity (Alsop et al., 2000). More recently, pulsed ASL revealed hypoperfusion in AD patients bilaterally in the inferior parietal and inferior frontal cortex, as well as the posterior cingulate (Johnson et al., 2005). Compared with healthy controls, subjects with mild cognitive impairment (MCI) showed decreased perfusion (albeit less robust than in the AD group) in an area of the inferior right parietal lobe similar to the region of most severely reduced perfusion in the AD group (Johnson et al., 2005). One limitation of the Johnson study was that it tagged arterial spins at the level of the circle of Willis. Thus, the area imaged excluded relevant inferior portions of the brain such as medial temporal lobes and inferior frontal areas (Krishnan et al., 2005).
Although sites of hypoperfusion in these three studies differ somewhat—probably related to differences in brain coverage—they are consistent with previous PET findings as well as the pathophysiology and neuropsychological deficits characteristics of AD. If the MCI findings are replicated, ASL measures of perfusion may prove a useful biological marker for MCI.
Epilepsy
ASL has been used to augment presurgical planning of epilepsy patients and to explore basic questions about the coupling of CBF and metabolism during interictal epileptic discharges. Using continuous ASL, one study found abnormal asymmetries of medial temporal lobe flow in patients with intractable temporal lobe epilepsy (Wolf et al., 2001). Seizure laterality was determined by surface and intracranial electroencephalograms, PET 18F-fluorodeoxyglucose scans, and surgical outcome. When the sign of an ASL perfusion asymmetry index obtained in the medial temporal lobe was used to predict the laterality of the temporal lobe seizure, relative hypoperfusion correctly predicted lesion laterality in 11 of the 12 cases. The one patient whose ASL measure predicted lesion laterality opposite from the surgical hemisphere was not seizure free after the surgery. Diagnostic reading of presurgical magnetic resonance images correctly identified seizure laterality in only nine patients, and an asymmetry index based on hippocampal volume measured from structural MR images correctly lateralized 8 of 11 cases. The ASL measure of temporal lobe perfusion asymmetry correlated .79 with the asymmetry measure derived from the 18F-fluorodeoxyglucose PET scans. In this small study, ASL measures of asymmetry outperformed all other methods except FDG-PET, which was used to define the optimal side for surgery and, therefore, formed part of the prediction criterion (Wolf et al., 2001). Another study of patients with temporal lobe epilepsy found a significant correlation of .75 between a pulsed ASL measure of asymmetrical perfusion and an asymmetry measure of CBF obtained by H215O PET perfusion imaging (Liu et al., 2001).
The use of ASL flow measures to identify temporal lobe regions containing abnormal neural tissue assumes that the coupling of flow and neural metabolism is not disrupted by epilepsy. CBF and regional metabolism in an epileptic focus increase during the early phase of seizure activity, then decrease with nerve cell death (Duncan, 1997; Henry et al., 1993; Ingvar, 1986; Weinand & Carter, 1994). Studies of interictal flow and metabolism in focal epilepsy have produced mixed results, with evidence supporting both compromised (Breier et al., 1997; Fink et al., 1996) and preserved (Franck et al., 1989; Kuhl et al., 1980) coupling of CBF and metabolism. Stefanovic and colleagues (2005) used combined ASL and BOLD measures to study the coupling of CBF and cerebral oxygen utilization in seven patients with idiopathic generalized epilepsy studied during performance of a motor task and while experiencing interictal epileptic discharges. Interictal epileptic activity typically involved several dozen bursts of spike and wave discharges each lasting less than four seconds. The interictal epileptic discharges occurred in the absence of clinical signs of a seizure. Multislice, pulsed ASL obtained by a PICORE QUIPSS II protocol was used to measure CBF (Stefanovic et al., 2005; Wong et al., 1998). A standard gradient echo, T2* weighted sequence was used to obtain BOLD signal measurements. Both CBF and BOLD images were obtained during a block design experiment comparing rest with a pinch-grip of a pressure bulb and, in a separate experiment, during graded exposure to carbon dioxide (hypercapnia). The percent change in the cerebral metabolic rate of oxygen utilization (%ΔCMRO2) was obtained from CBF and BOLD measures using the deoxyhemoglobin dilution model (Davis et al., 1998). The hypercapnia experiment provided a calibration constant that defined the maximum BOLD signal change possible given the specific hardware and pulse sequences used. See Liu and Brown (2007) or Davis et al. (1998) for a discussion of the calibrated BOLD method. The CBF response to the pinch-grip condition was linearly related to %ΔCMRO2, with a slope equal to 0.46 ± 0.05. The coupling was very similar to the value observed by these authors in a previously published group of healthy controls, where the slope equaled .44 ± 0.04 (Stefanovic et al., 2005). In only two subjects did any areas of BOLD response to interictal epileptic discharges overlap with CBF changes. Across these small areas of overlap, %ΔCBF and %ΔCMRO2 were linearly related with a slope equal to 0.48 ± 0.17, a value very similar to those observed in the pinch-grip paradigm.
Stefanovic and colleagues interpreted their results as supporting the coupling of flow and metabolism during behavioral activation tasks in patients with epilepsy (Stefanovic et al., 2005). It will be important to confirm this coupling with other behavioral paradigms, especially those that activate temporal lobe function. Their data on the coupling of flow and metabolism during interictal epileptic discharges is less convincing. The regression analysis Stefanovic and colleagues reported involved only two patients, and one patient contributed more than one data point to the regression. Moreover, the BOLD and CBF t-value maps Stefanovic and colleagues (2005) published showed areas where epileptic discharges appeared to have altered BOLD signals without altering flow, suggesting an uncoupling of metabolism and flow. Thus, whether CBF and BOLD signals remain coupled during interictal epileptic discharges remains an open question.
Affective Disorders
In the only study to utilize ASL in affective disorders, hyperperfusion measured by pulsed ASL in ventral anterior cingulate and amygdala predicted antidepressant response to partial sleep deprivation among individuals with major depression (Clark et al., 2006a, 2006b). These results were consistent with previous PET and SPECT studies of sleep deprivation and antidepressant medication in major depression (Buchsbaum et al., 1997; Mayberg et al., 1999; Wu et al., 1999; Drevets et al., 2002).
Anxiety Disorders and Stress
PubMed searches that combined the terms “Anxiety Disorder,” “Post-traumatic Stress Disorder,” or “Phobia” individually with “Arterial Spin Labeling” did not locate any papers. We did find one study using CASL to study changes in cerebral perfusion related to the stress induced by performance-monitored mental arithmetic (Wang et al., 2005). The authors chose CASL perfusion methods over BOLD because of the former method's long-term stability (Liu & Brown, 2007, this issue). CBF in the right ventral prefrontal cortex, right insular-putamenal region, and anterior cinglulate showed sustained activation among individuals showing high stress responses to mental arithmetic. Moreover, baseline CBF in the ventral, right prefrontal cortex and right orbitofrontal cortex correlated with changes in physiological measures of stress induced by mental arithmetic. This study shows the usefulness of combining baseline perfusion with activation data to support inferences about brain systems that mediate stress responses.
Substance Use Disorders
A study contrasting the relationship between BOLD and ASL measures during IV cocaine and placebo (saline) infusion found that BOLD signal intensity (measured during visual stimulation) did not change significantly with cocaine infusion, even though IV cocaine produced a 14% decrease in global cortical gray matter perfusion. (Gollub et al., 1998). A pulsed ASL study showed decreased prefrontal and left parietal perfusion in young alcohol dependent women compared with women who were not alcohol dependent (Clark et al., in press). In both cases, ASL findings were consistent with PET and SPECT findings (Moselhy et al., 2001; Demir et al., 2002; Gottschalk & Kosten 2002). A recent paper reported that chronic cigarette smoking in alcohol dependent individuals is associated with reduced ASL-measured CBF in frontal and parietal cortex (Gazdzinski et al., 2006).
Human Immunodeficiency Virus
Continuous ASL has also been successfully used to study HIV patients (Ances et al., 2006). Compared with HIV negative controls, the HIV-associated neurocognitive impairment (HNCI) group showed significantly decreased blood flow in the caudate nucleus, a structure preferentially affected in HIV infection. HIV patients with subsyndromal neurocognitive findings showed a mild decrease in caudate perfusion compared with healthy controls (p = .070). Reduced caudate perfusion may be a useful biomarker for subsequent studies of neurocognitive decline in HIV positive subjects (Ances et al., 2006).
COMMENT
Arterial spin labeling appears to be a valid method for the study of lower and higher brain functions. ASL CBF detects expected patterns of brain activation predicted from the known functional organization of the motor, visual, and language systems of the brain. ASL CBF has strong concurrent validity as a marker of brain function when correlated with dynamic susceptibility weighted contrast imaging and with near infrared spectroscopy. ASL CBF more strongly correlates with changes of behavioral state than do BOLD signals when the changes occur over periods longer than a few minutes. ASL measures of brain response appear to be less variable across subjects than do BOLD measures. These properties make ASL an especially useful noninvasive method to measure CBF in longitudinal and treatment studies. ASL's lower contrast to noise when compared with BOLD can be improved by removing unwanted variation through physiological monitoring and by performing studies at higher field strengths. ASL CBF seems less sensitive to artifacts created by spoken responses than do BOLD signals. ASL CBF is likely to become commonly used in cognitive and affective neuroscience to study slowly evolving changes in psychological state, such as mood changes, and to help with the interpretation of BOLD findings in pharmacological studies.
The literature reviewed supports the validity of ASL perfusion as a marker of neuronal dysfunction in several neuropsychiatric disorders. ASL perfusion is highly accurate in detecting the laterality of a lesion. In particular, asymmetry of ASL perfusion is strongly correlated with lateralized clinical symptoms in stroke, CBF asymmetries in stenotic-occlusive disease, hemodynamic asymmetries produced by lateralized brain tumors, and lateralized temporal lobe abnormalities in epilepsy. Within lesioned areas, ASL measures of perfusion have excellent concurrent validity when correlated with PET CBF or with dynamic susceptibility-weighted MR signals. Among individuals with stroke, ASL can provide a clearer picture of the localization of ischemic deficit underlying focal neuropsychological functions than structural MRI (Love et al., 2002). Among brain tumor patients, ASL can be used to provide an initial tumor grading. ASL appears to be useful when planning epilepsy surgery and when predicting treatment response to brain tumor surgery. Early post-surgical changes in ASL perfusion appear to be especially accurate in predicting treatment response in brain tumors. The ability of ASL to selectively and non-invasively tag flow through the major vascular territories is likely to be especially useful when evaluating and monitoring treatment of cerebrovascular disease and brain tumors. Conclusions about ASL must be qualified by the small sample sizes of the studies currently in the literature. Moreover, few studies have used ASL to investigate CBF in epilepsy, mood disorders, and HIV, limiting conclusions that we could draw about the utility of ASL in these disorders. Finally, no human studies using ASL to study “head injury,” “traumatic brain injury,” “anxiety disorders,” “obsessive-compulsive disorders,” “post-traumatic stress disorder,” “phobia,” or “schizophrenia” were identified in our PubMed search (www.pubmed.gov). ASL research into these common neuropsychiatric disorders is uncharted.
Although ASL provides highly valid qualitative information about CBF abnormalities, disease processes that alter the structure of the cerebrovasculature can limit the use of ASL to quantify blood flow in absolute units. Perhaps the most important challenge is that diseases that alter the path of flowing blood can change the transit times involved in the delivery of tapped blood to a brain region. Variation in transit times, in turn, causes unwanted variation in CBF estimates (Buxton et al., 1998). Disorders, such as vascular anomalies or stenotic-occlusive disease, that distort the geometry of cerebral vessels or interrupt the normal path of blood's flow through the brain are known to alter blood flow transit times (Kim et al., 2002; Matsumoto et al., 2000). Investigators and clinicians using ASL to examine CBF in conditions known to alter transit times should have a firm understanding of how altered transit times might influence quantitative CBF measures for the disorder they are studying. Fitting flow equations to ASL data points from a study involving multiple inversion times is one method to account for variable transit times in clinical studies (Hendrikse et al., 2004). Alternatively, a relatively new ASL method, referred to as velocity-selective ASL, that tags blood based on velocity as opposed to spatial position, has the potential to provide accurate CBF measures even in the presence of long transit delays (Liu & Brown, 2007; Wong et al., 2006). The characteristics of velocity-selective ASL are under active investigation.
Although ASL CBF measures correlated well with other accepted blood flow measures, ASL has lower intrinsic signal to noise than some other techniques (Wintermark et al., 2005). Moreover the incremental validity of ASL perfusion compared with more established methods, such as PET and dynamic susceptibility-weighted MR, still remains to be determined. Yet, the studies reviewed suggest that ASL methods of measuring CBF may be as accurate as more invasive methods. Given that ASL is repeatable, non-invasive, and easily integrated with other MR methods to image brain anatomy and metabolism, ASL blood flow techniques are likely to become more widely used in clinical research and practice.
ACKNOWLEDGMENTS
Preparation of this paper was supported by the VISN 22 Mental Illness Research Education and Clinical Center, a Biomedical Engineering Research Grant from the Whitaker Foundation, and by NIH grants #1 U24 RR021992 to the Function Biomedical Informatics Research Network (FBIRN, http://www.nbirn.net), 1 RO1 NS051661 to the first author, 5 K08 MH01642 and the 2006 Sleep Research Society Foundation J. Christian Gillin, M.D. Research Award to the second author, and 1 R01 NS367220 to Richard Buxton.