Introduction
Neural models of adult post-traumatic stress disorder (PTSD) suggest abnormalities in circuitry underlying emotion regulation. Relatively common findings have included increased activation of the amygdala, insula and dorsal anterior cingulate cortex (dACC) in response to emotional stimuli, particularly negative or threatening stimuli (Rauch et al. Reference Rauch, Shin and Phelps2006; Shin & Liberzon, Reference Shin and Liberzon2010). By contrast, the ventromedial prefrontal cortex (vmPFC) shows relatively decreased activation in PTSD (Rauch et al. Reference Rauch, Shin and Phelps2006; Shin & Liberzon, Reference Shin and Liberzon2010). The hippocampus shows increased activation to encoding of negative stimuli but impaired recruitment during fear extinction in subjects with PTSD (Milad et al. Reference Milad, Pitman, Ellis, Gold, Shin, Lasko, Zeidan, Handwerger, Orr and Rauch2009; Brohawn et al. Reference Brohawn, Offringa, Pfaff, Hughes and Shin2010). These findings have led to a neural model of PTSD in which there is heightened detection and encoding of emotional stimuli mediated by the amygdala and hippocampus, increased threat appraisal and expression of fear responses by the dACC, with impaired fear suppression by the vmPFC and hippocampus (Rauch et al. Reference Rauch, Shin and Phelps2006; Quirk & Mueller, Reference Quirk and Mueller2008; Shin & Liberzon, Reference Shin and Liberzon2010). Abnormal functioning of this network may underlie symptoms of re-experiencing, avoidance and hyperarousal that are characteristic of PTSD.
Currently, the contribution of cumulative trauma, particularly childhood maltreatment, to neural dysfunction in PTSD remains largely unexplored. A history of childhood maltreatment represents one of the largest risk factors for the development of PTSD as an adult. In the military population, the risk is similar to that of the adult index trauma (effect size ∼0.25) (Brewin et al. Reference Brewin, Andrews and Valentine2000). Structural brain studies of trauma-exposed children (without apparent psychiatric illness) suggest reduced volume of the PFC (Hanson et al. Reference Hanson, Chung, Avants, Shirtcliff, Gee, Davidson and Pollak2010; Edmiston et al. Reference Edmiston, Wang, Mazure, Guiney, Sinha, Mayes and Blumberg2011). Studies of adults with a history of childhood maltreatment have demonstrated reduced PFC and hippocampal volumes, and increased amygdala activation to threat stimuli (Andersen et al. Reference Andersen, Tomada, Vincow, Valente, Polcari and Teicher2008; Lupien et al. Reference Lupien, McEwen, Gunnar and Heim2009; Dannlowski et al. Reference Dannlowski, Stuhrmann, Beutelmann, Zwanzger, Lenzen, Grotegerd, Domschke, Hohoff, Ohrmann, Bauer, Lindner, Postert, Konrad, Arolt, Heindel, Suslow and Kugel2012). Thus, childhood maltreatment exposure may impact emotion regulation circuitry to create vulnerability for the development of post-traumatic stress symptoms (PTSS) following subsequent trauma in adulthood.
Adult trauma exposure may further impact emotion regulation circuitry to create vulnerability for PTSD symptoms. A study of combat veterans without PTSD or mental illness revealed that combat exposure itself was associated with increased amygdala and insula activation to emotional stimuli (van Wingen et al. Reference van Wingen, Geuze, Vermetten and Fernández2011a). These changes were reported to normalize after 1.5 years, although changes in amygdala–dACC coupling related to perceived combat threat remained (van Wingen et al. Reference van Wingen, Geuze, Vermetten and Fernandez2011b). Together, these findings suggest that childhood and adult trauma exposure may act in a cumulative way to alter emotion regulation circuitry and precipitate the clinical symptoms of PTSD.
In the current study we examined the functional neural correlates of childhood maltreatment, combat exposure and PTSS in young military veterans. We included all variables in a single model to examine their relative contributions to brain activation. In response to implicit threat stimuli, but not to positive stimuli, we hypothesized that childhood maltreatment, combat exposure and current PTSS would correlate with increased amygdala, insula, dACC and hippocampal activation, and impaired vmPFC recruitment in an additive way. In line with the dimensional approaches proposed for DSM-5 and the National Institute of Mental Health (NIMH) Research Domain Criteria (in particular, the threat processing domain) (Helzer et al. Reference Helzer, Kraemer, Krueger, Wittchen, Sirovatka and Regier2008; Insel et al. Reference Insel, Cuthbert, Garvey, Heinssen, Pine, Quinn, Sanislow and Wang2010), we examined these variables in subjects with a wide range of PTSS, both above and below the PTSD threshold.
Method
Participants
Twenty-eight young male combat veterans from Operations Enduring and Iraqi Freedom were recruited from the Pittsburgh area through public media advertisements from October 2010 to November 2011. Written informed consent was obtained from all participants after procedures were explained according to University of Pittsburgh Institutional Review Board guidelines. DD Form 214 documentation of prior military service was obtained from all potential participants. Subjects were between the ages of 18 and 35 years, right-handed and medication free. Exclusion criteria included active substance abuse (past month), suicidality, psychotic or bipolar disorder, magnetic resonance imaging (MRI) contra-indication, or neurological disease. In addition, participants were not included if they were currently receiving treatment for traumatic brain injury or had concussive symptoms at the time of the study. Of the 28 participants in the current sample, 13 (46.4%) reported exposure to blast, fire or explosion. Nine (32.1%) reported a history of closed head injury, and two of them also endorsed a loss of consciousness during their combat deployment. Seven of these participants endorsed being dazed, confused or ‘seeing stars’, two participants endorsed not remembering the injury, and four participants endorsed having symptoms of concussion afterwards. Symptoms included headache, dizziness and irritability. However, none had concussive symptoms or were being treated for any sequelae of traumatic brain injury at the time of participation.
Subjects were assessed with the Structured Clinical Interview for DSM-IV Axis I Disorders (SCID-I; First et al. Reference First, Spitzer, Gibbon and Williams2002). Past month PTSS were assessed using the Clinician-Administered PTSD Scale (CAPS; Blake et al. Reference Blake, Weathers, Nagy, Kaloupek, Gusman, Charney and Keane1995). Eighteen subjects met full criteria for PTSD as identified by the CAPS, using the F1/I2 criteria (Weathers et al. Reference Weathers, Keane and Davidson2001). Three subjects met criteria for current major depressive disorder. Subjects were free of other current co-morbid psychiatric disorders as determined by the SCID. Past DSM-IV diagnoses included major depressive disorder (n = 5), bulimia nervosa (n = 1), alcohol abuse/dependence (n = 15), cannabis abuse/dependence (n = 4), and cocaine abuse/dependence (n = 1). The prevalence of these diagnoses did not differ significantly between PTSD and non-PTSD subjects (χ2 test, p > 0.1). Depressive symptom severity was measured using the Beck Depression Inventory (BDI; Beck et al. Reference Beck, Ward, Mendelson, Mock and Erbaugh1961). Level of combat exposure was measured with the Combat Exposure Scale (CES; Keane et al. Reference Keane, Fairbank, Caddell, Zimering, Taylor and Mora1989). Childhood maltreatment history was assessed using the Childhood Trauma Questionnaire (CTQ; Scher et al. Reference Scher, Stein, Asmundson, McCreary and Forde2001); the total CTQ score was used for this study. Additional rating scales included the Dissociative Experiences Scale (DES; Bernstein & Putnam, Reference Bernstein and Putnam1986) and the National Adult Reading Test (NART; Blair & Spreen, Reference Blair and Spreen1989) to estimate IQ.
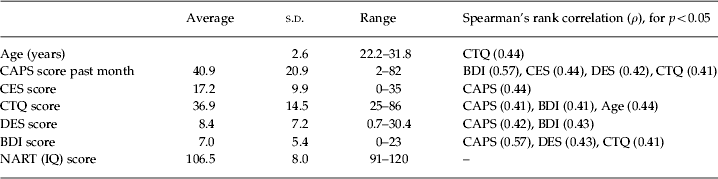
Demographic and clinical variables for the subjects are shown in Table 1. Across all subjects, Spearman's rank correlation of clinical variables revealed that the CAPS score correlated significantly (p < 0.05) with BDI (ρ = 0.57), CES (ρ = 0.44), DES (ρ = 0.42) and CTQ scores (ρ = 0.41). BDI scores also correlated with DES (ρ = 0.43) and CTQ (ρ = 0.41) scores, and CTQ correlated with subject age (ρ = 0.44). NART (IQ) scores were not significantly correlated with other variables.
Demographic and clinical variables for participants (n = 28)
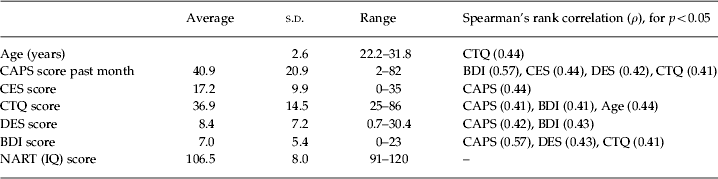
CAPS, Clinician-Administered Post-Traumatic Stress Disorder Scale; CES, Combat Exposure Scale; CTQ, Childhood Trauma Questionnaire; DES, Dissociative Experiences Scale; BDI, Beck Depression Inventory; NART, National Adult Reading Test; s.d., standard deviation.
Dynamic faces task
Subjects completed functional MRI (fMRI) during which they performed a dynamic faces task. This paradigm is an implicit emotion processing task that elicits activation in the amygdala and mPFC and has been described previously (Almeida et al. Reference Almeida, Kronhaus, Sibille, Langenecker, Versace, Labarbara and Phillips2011). In brief, participants were asked to identify the color of a semi-transparent foreground color flash that appears during the presentation of a dynamically changing background face (neutral to emotional). Emotion conditions included: happy, sad, angry and fearful. Only angry and happy conditions were examined in our analyses (angry as the most threatening emotion condition, and happy as a positive, safe condition for comparison). Control trials consisted of a simple morphing shape with similar structural and movement characteristics to each face stimulus. Emotional and control blocks were presented in a pseudo-randomized order so that no two blocks of any condition were presented sequentially.
MRI acquisition and image processing
Neuroimaging data were collected using a 3-T Siemens Trio MRI scanner at the Magnetic Resonance Research Center in the University of Pittsburgh Medical Center. Structural three-dimensional (3D) axial magnetization prepared rapid gradient echo (MPRAGE) images were acquired in the same session [echo time (TE) 3.29 ms, repetition time (TR) 2200 ms, flip angle 9°, field of view (FOV) 256 mm × 192 mm, slice thickness 1 mm, matrix 256 × 256, 192 continuous slices]. Blood oxygen level-dependent (BOLD) images were then acquired with a gradient echo echo-planar imaging (EPI) sequence during 13 min covering 39 axial slices (3.1-mm thick, TR/TE 2000/28 ms, FOV 205 cm × 205 cm, matrix 64 × 64, flip angle 90°).
Analyses were conducted in SPM8 (www.fil.ion.ucl.ac.uk/spm). Structural MPRAGE images for each participant were realigned manually and segmented into native space. BOLD images were realigned and unwarped, co-registered with the anatomical gray matter image, and spatially normalized into standard stereotactic space [Montreal Neurological Institute (MNI) template] using a 12-parameter affine model. Normalized images were resampled to 2 mm× 2 mm × 2 mm voxels and smoothed with a 6-mm full-width at half-maximum (FWHM) Gaussian filter.
A first-level (within-subject) fixed-effect model was constructed with four emotions (anger, fear, sad and happy) and the control condition entered as separate regressors in the design matrix, including movement parameters as nuisance variables and the canonical hemodynamic response function (HRF) model. The second-level analysis included two separate, multivariate voxelwise regressions for the angry-shape and happy-shape contrasts within SPM8. Only angry and happy conditions were included in the final analysis as preliminary analyses suggested suboptimal task-induced activation in the fear and sad conditions, making them unsuitable for hypothesis testing in this group of subjects. Angry and happy conditions were not compared directly. Regressors of interest included the CAPS, CES, CTQ and DES, and were covaried for depressive symptoms and estimated IQ. Dissociative symptoms were included in this model given evidence suggesting the opposite pattern of brain activation in dissociative subtypes of PTSD (e.g. increased vmPFC, decreased amygdala activation; Lanius et al. Reference Lanius, Vermetten, Loewenstein, Brand, Schmahl, Bremner and Spiegel2010). Task-induced effects were first determined across all subjects for each emotion condition. Subsequently, task-related activation patterns for each regressor of interest were examined from the same model.
Functional regions of interest (ROIs) were defined as clusters of contiguous voxels exceeding the a priori statistical threshold in a manner similar to that described previously (Milad et al. Reference Milad, Pitman, Ellis, Gold, Shin, Lasko, Zeidan, Handwerger, Orr and Rauch2009; Rougemont-Bücking et al. Reference Rougemont-Bücking, Linnman, Zeffiro, Zeidan, Lebron-Milad, Rodriguez-Romaguera, Rauch, Pitman and Milad2011). We focused our fMRI data analysis a priori on the anteromedial PFC, amygdala, hippocampus and insula. For these areas we used a threshold of uncorrected p < 0.001, and a minimum spatial extent of 10 contiguous voxels. We used a more stringent threshold of p < 0.0001 for other brain regions.
Results
Task performance
Overall, subjects performed with high accuracy in identifying color flashes during the angry and happy trials (90% and 91% correct respectively). Multivariate regression was performed in SPSS version 20 (SPSS Inc., USA) to include all clinical variables in a single model and determine whether they predicted differences in reaction times or accuracy for the angry or happy conditions relative to the shape condition. CAPS, CES, CTQ, DES and NART scores showed no significant correlation with relative reaction times or accuracy. BDI score correlated positively with a longer reaction time to happy versus shape (β = 0.50, p = 0.04) but not to angry versus shape. BDI was not correlated with relative accuracy for either emotion.
fMRI responses during the dynamic faces task
Angry versus shape
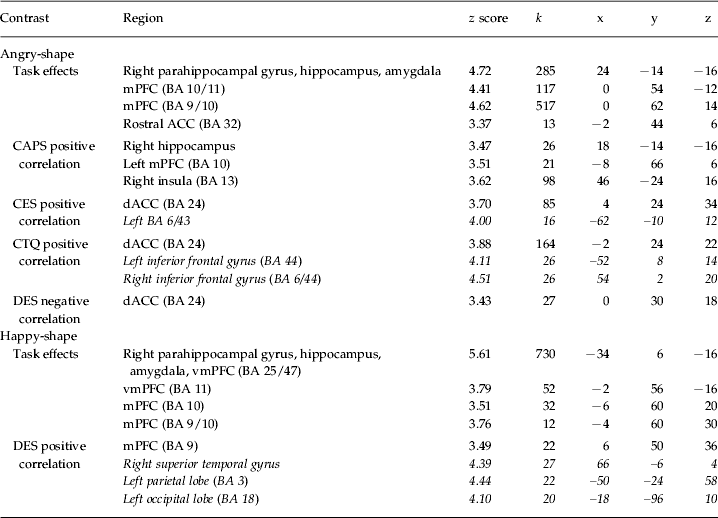
A summary of regional brain activation is shown in Table 2. Across all subjects, the angry trials (contrasted to shape) activated the medial and ventral PFC [Brodmann area (BA) 9, 10, 11, 32], the right hippocampus and amygdala, and the bilateral fusiform gyrus (Fig. 1a). In the multivariate regression, which included all clinical variables in a single model within SPM, CAPS scores correlated positively with activation in the right hippocampus (Fig. 2a, b), right insula (BA 13, Fig. 2c, d) and mPFC (BA 10, Fig. 2e, f). CES scores correlated positively with dACC (BA 32) activation (Fig. 3a, b). CTQ scores correlated positively with an adjacent area of the dACC (BA 24) (Fig. 3c, d). Analysis of the CES- and CTQ-associated clusters in the dACC using ImCalc within SPM revealed that there was no spatial overlap (Fig. 3e). In contrast to CES and CTQ, DES scores correlated negatively with dACC (BA 24, Table 2). None of the variables in the model correlated significantly with amygdala activation.
Task effects. (a) The angry-shape contrast and (b) the happy-shape contrast revealed activation in the ventromedial prefrontal cortex (vmPFC), amygdala, hippocampus and the visual/face processing stream including the fusiform gyrus. The results were covaried for depressive symptoms and IQ. Activation patterns across all subjects are displayed at the p < 0.001 uncorrected threshold.

Clinician-Administered Post-Traumatic Stress Disorder Scale (CAPS) correlations for angry-shape contrast. CAPS scores (past month) correlated positively with activation in the hippocampus (a, b), insula (c, d) and medial prefrontal cortex (mPFC) (e, f). Activation images are shown for each brain region (a, c, e) along with partial plots of the extracted percentage blood oxygen level-dependent (BOLD) signal change for each cluster versus CAPS scores (b, d, f). The results were covaried for depressive symptoms and IQ.
Trauma exposure correlates for angry-shape contrast. Combat Exposure Scale (CES) (a, b) and Childhood Trauma Questionnaire (CTQ) (c, d) scores correlated positively with activation in adjacent areas of the dorsal anterior cingulate cortex (dACC; BA 32 and BA 24 respectively). Activation images (a, c) and partial plots of the extracted percentage blood oxygen level-dependent (BOLD) signal change versus trauma exposure (b, d) are shown. (e) CES- (yellow) and CTQ- (red) associated dACC clusters were adjacent and without any spatial overlap. The results were covaried for depressive symptoms and IQ.
Functional magnetic resonance imaging (fMRI) responses during the dynamic faces task
CAPS, Clinician-Administered Post-Traumatic Stress Disorder Scale; CES, Combat Exposure Scale; CTQ, Childhood Trauma Questionnaire; BDI, Beck Depression Inventory; vmPFC, ventromedial prefrontal cortex; dACC, dorsal anterior cingulate cortex; BA, Brodmann area; k, cluster size.
Multivariate regression was conducted in SPM8 to examine the neural correlates of CAPS, CES, CTQ and DES in the angry-shape and happy-shape contrast conditions. For each emotion contrast, overall task effects are shown, followed by significant correlations with clinical variables. Analyses were controlled for BDI and IQ scores. A priori functional regions of interest (shown in regular type) were identified at p < 0.001 uncorrected, with minimum cluster size k = 10 voxels. Regions outside of a priori areas (shown in italics) were identified at the more stringent p < 0.0001 threshold. Peak activation coordinates (x, y, z) are based on the Montreal Neurological Institute (MNI) atlas.
In regions outside of these a priori areas, CES correlated positively with activation in the left BA 6/43. CTQ correlated positively with activation in bilateral BA 44 and another cluster including BA 2 and 40.
Following on from these results, we performed two secondary analyses. First, we assessed for an interaction between CES and CTQ in the dACC by including an interaction term in the voxelwise multivariate regression. This analysis revealed no significant interaction in the dACC, although their independent associations with dACC activation remained. Second, the lack of a correlation between trauma exposure or PTSS and amygdala activation in this contrast is surprising and could be due to habituation of amygdala activation over repeated blocks. To examine this possibility, we extracted the task-induced amygdala activation for each block and performed further analysis within SPSS. Repeated-measures ANOVA revealed a significant effect of block (F = 11.84, p < 0.001). This effect was driven by robust amygdala activation to angry faces in blocks 1 and 2, but no activation in block 3, suggesting habituation. In multivariate regressions for blocks 1 and 2, the CAPS score correlated positively with amygdala activation (β = 0.49, p = 0.08 and β = 0.64, p = 0.03 respectively). CES, CTQ and DES scores were not correlated with amygdala activation in any of the blocks.
Happy versus shape
A summary of regional brain activation is shown in Table 2. Across all subjects, the happy trials (contrasted to shape) activated the medial and ventral PFC (BA 10, 11, 25, 47), the right hippocampus and amygdala, and the bilateral fusiform gyrus (Fig. 1b). In the multivariate regression, which included all clinical variables in a single model within SPM, CAPS, CES and CTQ scores were not significantly correlated with any brain activation or deactivation. DES scores correlated positively with dorsal mPFC (BA 9) activation (Table 2).
In regions outside of these a priori areas, DES also positively correlated with activation in the right superior temporal gyrus, and left parietal and occipital lobe.
Discussion
To our knowledge, this is one of the few studies to examine, within a single model, the contribution of childhood and adult trauma exposure and PTSS to alterations in brain circuitry that have been associated with PTSD. We tested this circuitry using a dynamic faces task that requires implicit emotion regulation and attentional processing of emotional cues. We focused on angry and happy emotional distractors in our analyses, with the prediction that angry faces are potent threat cues and would specifically elicit differences associated with childhood maltreatment, combat exposure and PTSS. Both emotion conditions elicited activation of the vmPFC and amygdala, suggesting engagement of circuitry underlying the detection of emotional cues and implicit regulation of emotional responses.
In the angry but not the happy trials, PTSS (CAPS scores) correlated positively with insula and hippocampus activation, and a small cluster in BA 10. PTSS also correlated with amygdala activation in earlier angry blocks. Combat exposure and childhood maltreatment scores correlated positively with activation of adjacent areas of the dACC. Dissociative symptoms, by contrast, correlated negatively with dACC activation.
Increased dACC activation has been observed in studies of PTSD, including studies of fear conditioning and extinction, emotional interference, and resting (Shin & Liberzon, Reference Shin and Liberzon2010). The dACC subserves the appraisal and expression of fear and anxiety, in addition to conflict adaptation (Phillips et al. Reference Phillips, Ladouceur and Drevets2008; Etkin et al. Reference Etkin, Egner and Kalisch2011; Shackman et al. Reference Shackman, Salomons, Slagter, Fox, Winter and Davidson2011). The dACC shows strong connectivity with the amygdala and is the probable homologue of the rat prelimbic (PL) cortex (Milad et al. Reference Milad, Rauch, Pitman and Quirk2006; Etkin et al. Reference Etkin, Egner and Kalisch2011). Deactivation, stimulation and neuronal recording studies of the rat PL cortex suggest that this region promotes the expression of fear responses (e.g. Vidal-Gonzalez et al. Reference Vidal-Gonzalez, Vidal-Gonzalez, Rauch and Quirk2006; Quirk & Mueller, Reference Quirk and Mueller2008; Burgos-Robles et al. Reference Burgos-Robles, Vidal-Gonzalez and Quirk2009; Sierra-Mercado et al. Reference Sierra-Mercado, Padilla-Coreano and Quirk2011). As such, heightened activity in this structure could underlie, in part, the hypervigilance (heightened threat appraisal) and generalized fear responses associated with PTSS. A study of Vietnam veteran twin pairs revealed increased dACC activation in both the twins with PTSD and their non-PTSD co-twins, suggesting that increased dACC activation is a familial risk factor for developing PTSD (Shin et al. Reference Shin, Lasko, Macklin, Karpf, Milad, Orr, Goetz, Fischman, Rauch and Pitman2009, Reference Shin, Bush, Milad, Lasko, Brohawn, Hughes, Macklin, Gold, Karpf, Orr, Rauch and Pitman2011). Our results suggest that one important familial risk factor may be childhood maltreatment exposure, which would be expected to be a common risk among siblings. Our findings further suggest that both childhood maltreatment and adult combat exposure correlate independently with dACC activation to threat. Clinically, both childhood maltreatment and combat exposure scores correlated significantly with PTSS. Thus, trauma-associated dACC activation could represent one putative mechanism for the development of PTSS, by creating vulnerability at the brain level. A recent study in rats revealed that chronic stress exposure resulted in a failure to decrease PL firing during fear extinction recall (Wilber et al. Reference Wilber, Walker, Southwood, Farrell, Lin, Rebec and Wellman2011). In humans, a longitudinal study of combat veterans revealed that perceived threat during combat may lead to a lasting, reduced negative coupling between the dACC and the amygdala, even in the absence of PTSD (van Wingen et al. Reference van Wingen, Geuze, Vermetten and Fernandez2011b). In this context, our findings suggest that both childhood and adult trauma exposure may sensitize the dACC, which may promote the appraisal of threat and the expression of fear responses through its connections with the amygdala. PTSS could then emerge from this vulnerability with additional changes in brain circuitry.
Consistent with studies of PTSD, our results demonstrate that PTSS are positively correlated with insula, amygdala and hippocampus activation to threat stimuli. Furthermore, these associations were specific to PTSS, and not attributable to childhood maltreatment or combat exposure. Increased insula and amygdala activation have been relatively common findings in studies of PTSD, with hippocampal activation being more variable (Shin & Liberzon, Reference Shin and Liberzon2010). Although our study is associational only, we speculate that altered activation in these areas could result from greater dACC activation related to trauma exposure. The dACC is known to have strong connections with both the amygdala and the insula (Shackman et al. Reference Shackman, Salomons, Slagter, Fox, Winter and Davidson2011). Sensitization of the dACC could, at least in vulnerable individuals, then lead to greater activation of the insula and amygdala–hippocampus complex, promoting anxiety and fear responses typical of PTSD. This would presumably occur in concert with vmPFC hypo-activation, although we did not detect associations with the vmPFC in our study. Clearly, more longitudinal studies in traumatized populations, beginning in childhood, will be needed to examine these possibilities.
PTSS were also associated positively with dorsomedial PFC (BA 10) activation in our study. This area has been implicated in the suppression of emotional responses, and in selecting choices or actions based on the affective value of an outcome (Phillips et al. Reference Phillips, Ladouceur and Drevets2008; Grabenhorst & Rolls, Reference Grabenhorst and Rolls2011). In this context, increased BA 10 activation may reflect a greater effort required in the presence of PTSS to suppress emotional responses and choose correct responses. Given the lack of differences in reaction times or accuracy, this could reflect a compensatory mechanism.
Our study did not reveal any significant correlations between trauma exposure or PTSS and vmPFC activation. Although vmPFC hypo-activation is commonly reported in studies of PTSD, some studies have found no differences between PTSD and control subjects (Francati et al. Reference Francati, Vermetten and Bremner2007; Etkin & Wager, Reference Etkin and Wager2007). There are several possible reasons for the lack of vmPFC associations in this study. First, although our study included subjects with a wide range of PTSS, we may not have had sufficiently high CAPS scores to detect an association within the vmPFC. When considering only subjects with PTSD, their past month CAPS scores were lower (average 53) than other studies of PTSD. Subjects were also younger than in most studies, with fewer co-morbidities and less chronicity of PTSD. Thus it is possible that vmPFC differences, which have also been shown to correlate with PTSD symptom severity (Shin & Liberzon, Reference Shin and Liberzon2010), are only more evident with more severe and chronic PTSD. Second, it is possible that alterations in vmPFC may have been present shortly after the end of deployment but have since normalized. Further longitudinal studies will be needed to test these possibilities.
Of note, we found that dissociative symptoms were negatively correlated with dACC activation in the threat, but not positive, emotion trials. Reduced dACC activation related to dissociative symptoms could reflect reduced appraisal and expression of fear and anxiety at the neural level (Lanius et al. Reference Lanius, Vermetten, Loewenstein, Brand, Schmahl, Bremner and Spiegel2010). It should be noted, however, that dissociative symptoms in this sample were fairly low, with all but three individuals with DES scores below 15. Thus, comparisons to studies of dissociative subtypes of PTSD are limited.
There are several limitations to the current study. First, these findings are cross-sectional and correlational only and cannot be used to infer causation. It is thus difficult to tease out whether observed changes represent pre-existing vulnerabilities, state-related changes or compensatory changes. Second, these findings may not generalize to other populations (particularly women given the all-male sample), trauma types, or individuals with more severe PTSD as discussed earlier. Third, although subjects were free of any current alcohol or substance abuse, this study did not have measures of cumulative, lifelong alcohol use, which could affect the current results. However, the PTSD and non-PTSD subjects had similar frequencies of past alcohol abuse/dependence, which makes it less likely that this potential confound systematically influenced the results. Fourth, this study enrolled a relatively small number of subjects and would merit replication with a larger sample.
In conclusion, our findings suggest that dACC activation observed in prior studies of PTSD may be attributable to childhood and adult trauma exposure. By contrast, insula, amygdala and hippocampal activation may be specifically associated with PTSS. The specificity of these results to threat stimuli, and not to positive stimuli, is consistent with abnormalities in threat processing associated with PTSD. Taken together, the results of the current study begin to suggest putative mechanisms by which childhood and adult trauma exposure may create a vulnerable brain substrate for the development of PTSS, which itself may emerge with additional changes in limbic circuitry.
Acknowledgments
We thank B. Paul and A. Filippone for their assistance with participant screening, MRI procedures and data organization, and Michael and Morven Heller for their sponsorship.
This work was supported by the American Academy of Child and Adolescent Psychiatry (AACAP) Pilot Research Award (R.J.H.), Department of Defense Congressionally Directed Medical Research Program PT073961 (A.G.), and the National Institute of Mental Health MH083035 (A.G.), MH076971 (M.L.P.), MH088913 (M.L.P.).
Declaration of Interest
Dr A. Germain has served as a consultant for Concurrent Technologies Corporation.