


1. A PUZZLE
Since standard models of household fertility postulate that children are normal goods, one would expect a positive relationship between income and children. However, empirical evidence invariably suggests that, within a given society, fertility is often higher in poorer families [Becker (Reference Becker1960), Jones and Tertilt (Reference Jones, Tertilt and Rupert2008)]. That negative relationship is also consistent across countries; those with higher average fertility have lower average levels of industrialization [Galor and Zang (Reference Galor and Zang1997), Bloom et al. (Reference Bongaarts and Casterline2009)]. In other words, standard economic assumptions are not generally enough to explain the negative fertility–income relationship regularly documented in empirical studies; instead, special assumptions regarding the functional form of the household’s utility or production functions have been necessary [Jones et al. (Reference Jones, Schoonbroodt, Tertilt and Shoven2011)].
Economic models of fertility have been extended to incorporate other relevant aspects of the childrearing decision, such as the explicit costs of raising the child and implicit costs associated with parental time and effort. Each cost can be linked to wage rates in the labor market [Becker (Reference Becker and Lewis1965), Mincer and Polachek (Reference Mincer and Polachek1974)], and each cost creates trade-offs between the quantity of children and the quality of children [Becker and Lewis (Reference Bloom, Canning, Fink and Finlay1973), Leibenstein (Reference Leibenstein1975), Caldwell (Reference Chhikara and Folks1976)]. Contemporary economic fertility theories, such as these, focus on the effects of parental income and the opportunity costs of child-rearing on completed family size. With a few exceptions [Becker (Reference Becker1960), Heckman and Willis (Reference Heckman, Willis and Terleckyj1976), Michael and Willis (Reference Michael, Willis and Terleckyj1976)], these theories do not explicitly incorporate reproduction inputs, such as fecundity and family planning services, despite the role of these two factors in shaping a woman’s fertility history.
In this analysis, we look at one very specific aspect of a woman’s fertility history – her time to first birth – and focus on the ability of contraception in extending that time, keeping in mind that there is uncertainty surrounding the reproduction process. We choose to focus on the duration to first childbirth, because it has the advantage of not depending on parity-specific factors.Footnote 1 The impact of contraception in delaying childbirth, stopping unwanted childbearing and postponing childbirth is an important contributor to fertility reduction [see Goldin and Katz (Reference Goldin and Katz2002), Moultrie et al. (Reference Moultrie, Sayi and Timaeus2012)]. Moreover, the age at which childbearing begins is a key factor in the realized level of a woman’s human capital investment – education and work experience [see Klepinger et al. (Reference Klepinger, Lundberg and Plotnick1995), Upchurch and McCarthy (Reference Upchurch and McCarthy1990), Fitzenberger et al. (Reference Fitzenberger, Sommerfeld and Steffes2013)]. It is generally assumed that increased age at first birth [see te Velde et al. (Reference te Velde, Habbema, Leridon and Eijkemans2012)] and longer birth intervals reduce the number of children a woman can have, although Bongaarts and Casterline (Reference Bradley, Croft, Fishel and Westoff2013) suggest that these intervals are naturally longer in Africa than in other regions. Unfortunately, not so much attention has been directed toward explicitly understanding the behavioral pathways linking contraceptive efficacy to birth spacing and timing [see Yeakey et al. (Reference Yeakey, Muntifering, Ramachandran, Myint, Creanga and Tsui2009)], which influences the fertility transition, and underpins the contribution of this research. Although certain types of contraception work better, because they are more effective, more efficiently used, or both, this analysis does not attempt to separate efficacy in correct use from efficacy in practical use.Footnote 2
Contraception derives its importance from the uncertainty at the center of the human reproduction process. There is uncertainty in the process, itself, as young women are unlikely to know how fertile they (or their partner) might be at any particular point in time. We incorporate the aforementioned uncertainty by assuming that for every fecundable woman, there is an underlying stochastic process leading to childbirth; in other words, there is a probability of pregnancy, and that can be affected by behavior as well as biology. Then, borrowing from the current literature on event history analysis, two types of stochastic fertility models can be formulated. A stochastic hazard fertility model where the childbirth hazard rate is some suitable function of the underlying stochastic process [see Woodbury and Manton (Reference Woodbury and Manton1977), Yashin and Manton (Reference Yashin and Manton1997)], and a birth interval model, which assumes that a woman becomes pregnant when the underlying stochastic process first satisfies a specified condition; thus, the time until birth is a first hitting time [see Aalen and Gjessing (Reference Aalen and Gjessing2001), Abbring (Reference Abbring2012)].
This study assumes an integrated analysis of fertility choices [Easterlin (Reference Erikson Baaz and Stern1975)], where a couples’ capacity to procreate depends on their fecundity, contraception decisions, and sexual behaviors [see Becker (Reference Becker1960), Heckman and Willis (Reference Heckman, Willis and Terleckyj1976), Michael and Willis (Reference Michael, Willis and Terleckyj1976)]. At the same time, they are assumed to choose the ideal number of children by maximizing the utility of their children, subject to a budget constraint reflecting the couple’s income, and their explicit and implicit costs of rearing those children. This approach is consistent with the demographic transition literature, which postulates that the following three prerequisites should prevail for there to be a sustained fertility transition: (i) fertility must be within the calculus of conscious choice; (ii) effective techniques of fertility reduction must be accessible; and (iii) reduced fertility must be viewed as advantageous [Coale (Reference Cox and Oakes1984)].
For our analysis, we use information on the timing of a woman’s first birth in an attempt to link contraceptive efficacy to birth timing and contribute to the debate over why the fertility transition has so far eluded the Democratic Republic of Congo (DRC). According to recent research, while most countries have completed or are well advanced in the transition to low fertility, the DRC is still far from meeting conditions for a sustained fertility transition [see Romaniuk (Reference Romaniuk2011)]. To the best of our knowledge, first hitting times have not been previously applied to study the onset of childbearing, especially in a high-fertility context.
In the empirical analysis, we focus on the timing of the first birth, given the high fertility rate among Congolese teenagers and to mitigate worries surrounding the effects of parity on birth spacing. Defining duration as the time between first intercourse and first birth, we find that the efficacy of contraception plays an important role in the observed duration, as predicted by our model.Footnote 3 Specifically, our results suggest that relatively more effective contraception increases baseline conditions for the mother, which increases time to first birth. Intuitively, these women can choose, to some degree; however, we also find that contraceptive availability matters. When contraceptives are more available, that also increases the time to first birth, as it retards the “drift” toward the first hitting time.
Furthermore, we are able to suggest a partial explanation for the income–fertility puzzle. First, our empirical results provide some support for the hypothesis that children are normal goods, since greater wealth and reduced costs of child-rearing are associated with a reduction in the time to first birth, in that the hasten “drift” toward the first hitting time. Second, since contraception availability is associated with increased time to first birth and because contraception is not easily accessed (therefore, it is costly) or necessarily easily used, the better-off and better educated find it easier to access and, thus, find it easier to delay childbirth. In other words, we observe childbirth delays (and presumably fewer children) among the well-off, because children are costly and they can afford contraception. This explanation does not deny that childrearing costs may be socio-economic status expenditures directly related to parents’ income or that there are implicit costs associated with looking after a child. In fact, our approach assumes such costs are linked to wage rates in the labor market [see Becker (Reference Becker and Lewis1965), Mincer and Polachek (Reference Mincer and Polachek1974)]. Thus, these costs could result in a quality–quantity trade-off [see Becker and Lewis (Reference Bloom, Canning, Fink and Finlay1973), Leibenstein (Reference Leibenstein1975), Caldwell (Reference Chhikara and Folks1976)]; however, we are not able to examine these trade-offs in this analysis.
2. MODEL STRUCTURE
Consider a women who, from first intercourse and for the rest of her sexually active life, makes decisions about the type of contraception she will use. We refer to this as et ∈ [0, 1], which is the level of contraception efficacy at each time t. These decisions are based on the reward she expects to derive from using contraception, which depends on the costs and benefits of contraception. Because contraception allows one to delay childbirth, potential benefits to contraception include human capital investment (such as education and/or work experience) and, thus, higher wages, while the potential costs include direct costs like contraception purchases and foregone joys associated with raising a child. Explicitly, we assume that contraception costs h(et ) per unit of time, and the cost is increasing and convex in the level of efficacy. Assume also that the women experiences natural fecundity pt , has access to It resources per unit of time, and bt net benefits per child (which we assume can be monetized for model convenience). Further, assume that if she decides to move from parity P to parity P + 1, she will have to take some time off to care for the newborn child, thus losing a possible α t percent of her resources It .
We define a birth interval over [0, T], where 0 represents first sexual encounter and T represents first birth. Our primary interest in the analysis is a stopping time τ ∈ [0, T]. Preferably, the stopping time should refer to the time at which contraception is discontinued, and happens with an expectation of childbirth (although childbirth may not occur in all cases). In our empirical analysis, however, we do not have data on contraception discontinuation, τ, and, therefore, we abstract from it. Given a set of information at the beginning of a birth interval and a possible stopping time in that interval, the woman’s total expected reward from contracepting with efficacy et is the sum of two terms: expected reward over [0, τ) and the continuation value over [τ, T) [see Stokey (Reference Stokey2009)].
With this notation and discussion in mind, the stopping time is determined by V 0, which denotes the total expected discounted reward from following an optimal contraception strategy over a finite horizon [0, T].
 $$\begin{eqnarray*}
V_{0} &=& \textrm{Expected reward over} [0,\tau ) + \textrm{Expected reward over}[\tau ,T)\\[-2pt]
& =& \int _{0}^{\tau }e^{-\rho t}\left[\left(1-\pi _{t}\right)\left(R_{1t}-h\left(e_{t}\right)\right)+ \pi _{t}\left(R_{2t}-h\left(e_{t}\right)\right)\right]dt+ e^{-\rho \tau }W_{\tau }(e, P),
\end{eqnarray*}$$
where π t [ ≡ (1 − et )pt ] is the probability of falling pregnant, ρ is the rate of time preference, and R 1t [ ≡ It + btP] and R 2t [ ≡ (1 − α t )It + bt (P + 1)] are the streams of the woman’s resources at parity P and P + 1, respectively. Given this structure, it is fairly clear that a woman’s stopping time decision balances the benefits of having a child against the costs of contraception and lost earnings, such that a women who stops contracepting believes that a child is more important to her than potential lost wages (even though contraception costs disappear).Footnote 4
After multiplying through and collecting terms, the total expected reward of stopping contraception at time τ becomes
 $$\begin{equation}
V_{0}= \int ^{\tau }_{0}e^{-\rho t}\left[I_{t}+ b_{t}P + \pi _{t}\left(b_{t}-\alpha _{t} I_{t}\right)-h(e_{t}) \right]dt + e^{-\rho \tau }W_{\tau }(e, P).
\end{equation}$$
By the Martingale Representation Theorem [see Gawarecki and Mandrekar (Reference Gawarecki and Mandrekar2011), pg. 49], the continuation value of contraception, W τ(e, P) in (1) is described by a diffusion process solving the following linear stochastic differential equation [see Sannikov (Reference Sannikov2008)]
 $$\begin{equation}
dW_{\tau }= \left(\rho (\tau ) W_{\tau }- \mu (\tau ) \right)d\tau + \phi (\tau )dB_{\tau },
\end{equation}$$
which, provided that
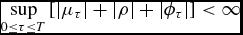 $\underset{0\le \tau \le T}{\sup } \left[|\mu _{\tau }|+|\rho |+|\phi _{\tau }|\right]<\infty$
and E(|w
0|2) < ∞, has a unique solution,
 $$\begin{equation}
W_{\tau }=e^{\rho \tau }\left[w_{0}-\int ^{\tau }_{0}e^{-\rho t}\left(\mu _{t}dt-\phi _{t}dB_{t}\right)\right],
\end{equation}$$
where Bt is a Gaussian Brownian motion, μ t ≡ [It + btP + π t (bt − α t It ) − h(et )] is the expected current net rewards from contracepting with efficacy level et at parity P, while ϕ t ≡ π t σ(pt ) are the diffusion coefficients.
2.1. Empirical Structure
As outlined in our theoretical structure, at each point in time, the woman weighs the direct rewards of stopping contraception, against the value of retaining the option of postponing childbearing, given “primitive” parameters and the history of the continuation value. In this case, she maximizes her expected discounted rewards by becoming pregnant when the continuation value of contraception hits a time-invariant threshold for the first time. Thus, our fertility model has two basic components: (1) a parent latent stochastic process in time {W
τ, τ ⩾ 0} which describes the dynamics of the continuation value of postponing childbearing, with initial value {W
0 = w
0} and (2) an absorbing set
 $\mathcal {B}$
in the state space of the unobserved stochastic parent process that defines its stopping condition.
For simplicity, we assume that the woman places equal value on both present and future utility, meaning that the rate of time preference ρ is equal to zero [see Ramsey (Reference Ramsey1928)]. As a result, the diffusion process in (2) reduces to a Brownian motion with drift of the form
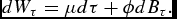 $$\begin{equation}
dW_{\tau }= \mu d\tau + \phi dB_{\tau }.
\end{equation}$$
This assumption is underpinned by the observation that the population hazards resulting from an Ornstein–Uhlenbeck process, as the one in (2) – with constant discount rate – and the Brownian motion in (4) are almost identical [see Aalen et al. (Reference Aalen, Borgan and Gjessing2008)].
Since the childbirth risk process is unobservable to the econometrician, as is the actual contraception discontinuation time, the only observable effect of W τ is through the individual event time T > 0, when the woman gives birth. Let the process W τ start in a positive initial value W(0) = w 0 > 0, and assume that the timing of the birth coincides with the time when the process is absorbed in the absorbing boundary (zero). Thus, the random variable T is defined as
 $$\begin{equation}
T=\underset{\tau \ge 0}{\inf } \lbrace \tau : W_{\tau } =0\rbrace .
\end{equation}$$
Consider one fecundable woman for a moment. As she postpones childbearing through birth control, the rewards she expects from postponing childbearing fluctuate. Over time, since first intercourse or her last live birth, she might experience a relatively steady decline in this contraception continuation value, and, eventually, it hits zero, the level at which we assume she gives birth. The first hitting time is the woman’s duration of the birth interval; here, the time to first birth. On the other hand, the woman may have experienced a relatively steady increase in her level of the continuation value. In this case, she may never give birth.
If we assume that a woman’s level of the continuation value of contraception as a function of time is described by the Brownian motion in (4), and that all coefficients are constant, then the first hitting time T has an inverse Gaussian probability distribution with the following probability density function [see Chhikara and Folks (Reference Coale1989)], where we return to using t to represent time, generically.
 $$\begin{equation}
f(t)=w_{0}(2\pi \phi ^{2} t^{3})^{-\frac{1}{2}}\exp \Bigg \lbrace -\frac{(w_{0}+\mu t)^{2}}{2 \phi ^{2} t}\Bigg \rbrace ,\textrm{for}\ \phi ^{2}>0, w_{0}>0,
\end{equation}$$
and the associated survival function (i.e., Cumulative Distribution Function or CDF)
 $$\begin{equation}
S(t)=\Phi \Bigg (\frac{w_{0}+ \mu t}{\sqrt{\phi ^{2}t}}\Bigg )-\exp (-2w_{0}\mu /\phi ^{2})\Phi \Bigg (-\frac{(w_{0}-\mu t)}{\sqrt{\phi ^{2}t}}\Bigg ),
\end{equation}$$
where Φ(·) is the CDF of the standard normal distribution, and μ and ϕ are the drift and volatility of the process, respectively.
The theory-based hazard rate for time to childbirth is found from θ(t) = f(t)/S(t), which is the ratio of the probability that a women who has not yet given birth will give birth in t, relative to the distribution of women who have not yet given birth up to t. In more practical terms, it describes the probability that a woman who has not yet given birth will do so in the next period of time.
Survival and duration analysis focus on the estimation of the hazard rate and related terms. One of the workhorses of survival analysis is the proportional hazards model [see Cox and Oakes (Reference Easterlin1984), for example]. As its name suggests, a proportional hazard rate is assumed to be proportional to model covariates. In practical terms, the primary benefit of the model is that under proportional hazards, covariate effects can be estimated without knowing the baseline hazard. However, if one is willing to assume a functional form for the baseline hazard rate, it can be estimated. Although appealing, it is not always amenable to interpretation [Reid (Reference Reid1994)], while assuming that covariate impacts should be proportional to the underlying hazard rate might be too restrictive.
Given the restrictiveness, we apply a first hit times (FHT) model, which is underpinned by the rationale of the stopping time problem previously developed.Footnote 5 FHT models are threshold models with regression structures that accommodate the effects of observed covariates and unobserved heterogeneity in duration data analysis. Such models are gradually finding broad application, due to their conceptual appeal and flexibility [see Lee and Whitmore (Reference Lee and Whitmore2006, Reference Lee and Whitmore2010)]. In economics, first hitting times arise in structural models in which agents are assumed to solve an optimal-stopping problem with related rewards described by stochastic processes [see Stokey (Reference Stokey2009)]. Economic applications have so far been confined to labor economics, including Lancaster’s (Reference Lancaster1972) strike duration study, the analysis of labor turnover [Whitmore (Reference Whitmore1979)], and the analysis of unemployment spells [Shimer (Reference Shimer2008)].
FHT models account for initial conditions, as well as dynamics in behavior (referred to as drift), that lead to the decision to stop contraception; thus, the FHT model may lend itself more easily to interpretation. The FHT model arrives at the childbirth hazard by estimating the density and survival function of the time-to-birth, computing the hazard as a ratio of the two. To give an idea about possible dynamics, we present, in Figure 1, hazard rates that might be derived in an FHT setting. Of particular interest is that, regardless of the initial conditions (w 0), all hazards for the Brownian motion converge to the same limiting hazard. Furthermore, the shape of the hazard rate is associated with the distance between the starting point and the point of absorption. At time t = 0, if the process Wt starts at a level close to zero relative to the distribution, the childbirth hazard rate is essentially decreasing; if it starts at an intermediate value of w 0, the childbirth hazard first increases and then decreases; finally, if it starts at a value of w 0 far from zero, the childbirth hazard rate is essentially increasing [see Aalen et al. (Reference Aalen, Borgan and Gjessing2008)].
Hazard rates for time to childbirth θ(t) when the process starts in different values of w 0, when μ = 1 and ϕ2 = 1.

The drift parameter, μ, if negative, quantifies the rate at which the woman approaches childbirth, but it may not be negative, and there is no guarantee that the process will reach the boundary set
 $\mathcal {B}$
. We recognize the fact that for some women, the childbirth risk process Wt
may diffuse away from the childbirth threshold for a long time, and diffuse almost directly toward it for others. Diffusion away (for a short period of time) could arise when some women are temporarily infertile. On the other hand, diffusion away could arise when a woman chooses not to have a child, such that T = ∞. To use the terminology in Abbring (Reference Abbring2012), infertile women make up an unobserved subpopulation that may be described as stayers, while those women who might choose not to have a child are defecting movers.
If μ ⩽ 0, meaning that the net benefits of childbearing are positive, there is a tendency to drift toward the childbirth threshold zero. In this case, childbirth is a certain event, which will occur in some finite time with probability one. The mean survival time, conditional on the event that the childbirth threshold is eventually reached, is
 $$\begin{equation*}
E(t)=\frac{w_{0}}{|\mu |},\textrm{for}\ \mu \ne 0.
\end{equation*}$$
2.2. Estimation Structure
We now turn our attention to the issue of estimating the model from data. So far, taking advantage of the fact that the probabilistic specification of the parent stochastic process in FHT models is usually explicit, parameter estimation for FHT models have been conducted mostly through maximum likelihood methods [see Lee and Whitmore (Reference Lee and Whitmore2006)].
In a total sample of N = NA + NB women, each woman i who has given birth contributes probability density f(Ti |w i0, μ i ) to the sample likelihood function, where Ti is the observed time of childbirth for i = 1, . . ., NA , while a woman j in the sample dataset who is still childless at the time of the survey contributes the survival probability S(Tj |w j0, μ j ) = 1 − F(Tj |w i0, μ j ), where Tj is the right-censored survival time of the woman for j = NA + 1, . . ., NA + NB . The sample likelihood function should be of the form
 $$\begin{equation}
\mathcal {L}(\theta |T)=\prod ^{N_{A}}_{i=1}\Big [f(T_{i}|w_{i0}, \mu _{i})\Big ] \prod ^{N_{A}+N_{B}}_{i =N_{A}+1} \Big [S(T_{i}|w_{i0}, \mu _{i})\Big ].
\end{equation}$$
The more flexible FHT model is easily extended to account for practical empirical problems related to censoring, for which we account by parameterizing censoring [Xiao et al. (Reference Xiao, Whitmore and He2012)]. From the model, if the expected loss from childbearing is higher than current income (i.e., μ > 0), a woman may never fall pregnant, and, thus, she will be childless. In other words, the distribution of women who have not yet given birth could be defective (T is arbitrarily large for some women), such that there is a mass point of survivors. If so, the expected proportion of childless women is given by
 $$\begin{equation*}
1 - c = P(T=\infty )=1-\exp \left(\frac{2w_{0}\mu }{\phi ^{2}}\right),
\end{equation*}$$
which implies that the probability of childbirth P(T < ∞) = 1 − P(T = ∞) may be less than 1. We denote the proportion of women who will eventually give birth to a child, if given enough time, by c, the propensity rate. The propensity rate may either be determined by the parameter values of the latent stochastic process when μ > 0 or be a free parameter that is independently linked to covariates in the FHT regression model. It follows that the modified likelihood function incorporating parameters to explain childlessness within the FHT model becomes
 $$\begin{equation}
\mathcal {L}(c, \theta |T)=\prod ^{N_{A}}_{i=1} c_{i} \Big [f(T_{i}|w_{i0}, \mu _{i})\Big ] \prod ^{N_{A}+N_{B}}_{i =N_{A}+1} \Big [1-c_{j}F(T_{i}|w_{i0}, \mu _{i})\Big ].
\end{equation}$$
As can be seen, (9) is identical to (8) if we assume that c = 1. In other words, all censored women in (8) are assumed to eventually give birth, which our model suggests is not true.
Although the full model has four parameters, namely w 0, μ, ϕ, and c, there are, statistically speaking, only three free parameters. The Inverse Gaussian distribution only depends on the remaining three parameters through two functions: μ/ϕ and w 0/ϕ. Thus, the variance ϕ2 may be set to one without loss of generality, when considering time to childbirth [see Aalen et al. (Reference Aalen, Borgan and Gjessing2008)].
3. PATHWAYS TO A FIRST CHILD IN DR CONGO
In what follows, we apply the FHT fertility model to data on married mothers’ first births from the DRC’s 2007 Demographic and Health Survey (DHS). Our analysis considers the latent childbirth risk process W as defined in (4) setting ϕ2 = 1. For every fecundable woman i, the density of the first-hitting time T is inverse Gaussian distributed as in (6) with a vector of free parameters θ = (ci, w 0i , μ i ) representing the propensity rate, the initial value and drift of the childbirth risk process, respectively.
Although our stopping time model focuses on the use of contraception, particularly the ending of use of contraception, our data only has information on the timing of birth and the age of first sexual encounter. We use the difference between the former and the latter to denote time to birth, when a birth occurs. However, in some cases, the data was inconsistent; for instance, a woman’s first sexual encounter might be reported as occurring after she had given birth. In such cases, we replaced the reported encounter date with a date nine months preceding birth. In other cases, the reported encounters were far too close to birth to be realistic. Although these could be prematurely born children, we dropped all births reported to have occurred inside of six months of the encounter, which reduced the sample by 160 observations.Footnote 6
The 2007 DHS for the DRC is a nationally representative survey for urban and rural residence. It provides information mainly on reproductive behavior and reproductive health for 9,995 women aged 15–49, as well as 4,757 men aged 15–59. The choice of the Congo is dictated by the fact that, despite its size and a large population, very little is known about this country, and its fertility level remains among the highest in the world. With a total population estimated at around 70 million people unevenly distributed on a 2,344,858 km2 surface area, the Congo’s fertility rate is estimated at 6.3.
3.1. Data and Descriptive Statistics
The values of the parameters ci, w 0i , and μ i are linearly linked to covariates that are represented by the vectors X′, Y′, and Z′, respectively.Footnote 7 We follow Xiao et al. (Reference Xiao, Whitmore and He2012) and link the log-odds ratio of ci to a linear combination of covariates. We use the theoretical model presented in Section 2 as a guide in choosing the covariates to include in X′, Y′, and Z′. According to Aalen et al. (Reference Aalen, Borgan and Gjessing2008), one of the major advantages of the threshold regression framework is its ability to differentiate between the effects of covariates on how far the risk process has advanced prior to the study (i.e., the effects on the initial level w 0) and the effects on the dynamics of the risk process (i.e., the effects on the drift μ i ), although some variables may effect both. Furthermore, although a number of variables are included in the model, outlined below, we do not include all variables in all specifications.
Regarding the covariates to include in X′, we assume that the propensity to give birth to a first child is determined by physiological and environmental factors. In that regard, we consider information related to her age at first marriage (in years), her education (none, completed primary, completed secondary or beyond), wealth [see Rutsein and Johnson (Reference Rutsein and Johnson2004), for the DHS methodology, which is underpinned by principle components analysis], whether or not the woman’s first sexual encounter was forced, whether or not she was a virgin when married, the total number of siblings she had and whether or not she moved from a rural to an urban residence.
As for Y′ and w 0i , the initial value of the childbirth risk process, we assume that it will depend on external factors related to the young woman’s socio-economic background around the time of her first sexual intercourse. These factors may include, among others, the woman’s taste for risks and her general childhood environment. In this analysis, we include age at first marriage, whether or not the mother was raised in a rural area during childhood, whether or not she was a virgin when she married, whether or not she knows anything about modern contraceptive methods, whether or not the woman’s first sexual encounter was forced and her level of education. In many cases, the woman’s first sexual encounter occurred before schooling was completed. However, we assume that completed education is also driven by childhood factors that are generally not observable, and, therefore, education is a relevant proxy for those factors.
With regard to Z′ and the drift μ i , we can deduce from the analysis in Section 2, that for a young woman with no children, yet, we have
 $$\begin{equation*}
\mu _{i}\equiv I_{i}(1-\alpha _{i}\pi _{i})+ b_{i}\pi _{i} -h_{i}(e),
\end{equation*}$$
which suggests that values of the woman’s income Ii , child related benefits bi , underlying fecundity (π), use and costs of contraception are important. For the analysis, we include the top four quantiles of the asset index along with the level of education to proxy for income. An asset index is an imperfect measure of wealth, but is all that is available in the DHS, while education is an important correlate of potential labor earnings. As this research is focused on the efficacy of contraception (as well as its cost), we focus our attention on the sort of contraception that the women used preceding the birth of her first child, although some women in the sample have not given birth. The data provides information from two separate questions. The first is whether or not the woman has ever used traditional/folkloric contraceptive methods (including, e.g., the rhythm method or withdrawal) or more modern methods (including intrauterine devices and condoms, among others). The second is the number of children previously born to the mother at the time of first use of contraceptive methods. With these, we are able to denote women who have used either traditional or modern methods and do not (did not) have any children at the time. We also interact these contraceptive measures with a categorical measure of education level (0 = none, 1 = completed primary, and 2 = at least secondary) to allow for the possibility that education could influence the efficacy with which either traditional or modern methods might be applied. In addition to these contraceptive measures, we include contraception availability, which is defined as the natural log of 100 minus the percent unmet need [see Bradley et al. (Reference Caldwell2012)] as a proxy for the cost of contraceptives. This variable is calculated at the survey cluster level, and accounts for the fact that some women may not have any need for contraception, since they might be infecund, postpartum amenorrheic, or sexually inactive.Footnote 8 In subsequent analysis, we also consider whether or not contraceptive availability could be influenced by wealth; thus, we interact wealth and availability. Finally, we include the number of older siblings of the mother, as a proxy for reduced childbearing costs; we assume that older siblings are in a position to help, for example, with care.
Summary statistics for the analysis variables are reported in Table 1. They are separated by the type of birth control used, which is our primary concern. The data suggest that the majority of young women in our study were raised in rural areas, are not well-educated, while too many of them know nothing about modern birth control methods and suffered the ignominy of being forced to participate in their first sexual encounter. Another feature observed in the data is the differentiation in childhood residence, schooling, asset index quintile, age at first marriage, contraception availability, and total number of siblings across the type of contraception. In particular, women who used modern methods are, on average, better educated, were raised in smaller families in urban areas, wealthier, and have better access to contraception. These differences underscore the difficulty in estimating truly exogenous impacts, although we do control for these factors in the subsequent analysis. As expected, the underlying survival times are not similar across the subsamples; all of these differences suggest heterogeneous hazard functions, possibly to the point of being non-proportional.
Summary statistics

Summary Statistics by type of contraception used, when (while) the women had (has) no children. Total sample size: N = 6,959. Asset index is pre-calculated and provided in the survey. Standard errors in parenthesis. aAt least two reported means are statistically significantly different from each other according to one-way ANOVA, level of significance ⩽ 0.001. bMeans are statistically significant from each other, level of significance ⩽ 0.05. cAt least two reported means are statistically significantly different from each other according to one-way ANOVA, level of significance ⩽ 0.10. * Some women have not given birth to any children, yet.
3.2. Empirical Results
The estimated parameters for two models, one specifically incorporating birth propensity (Model 2) and one not incorporating (Model 1) are presented in Table 2. The results are broadly consistent with our theoretical model. In particular, we find that the initial value of the childbirth risk process (ln w 0) is higher for women who are older at the time of their marriage. There is also evidence that the risk process starts at a lower level (the initial risk is higher) for women who were virgins when married. We also see that it is higher for more educated women and for women whose first sexual encounter was forced. These latter two, in particular, point to relatively high “initial” costs of childbirth. Where a woman’s first sexual encounter was forced, she might fear intimacy with men, while sexual engagement for the purposes of procreation could entail other psychic costs for the woman. With education, we expect more educated women to have greater lifetime earnings potential; since raising children is associated with time away from work, and, therefore reduced earnings potential, more educated women are subject to greater childbirth opportunity costs than less educated women.
First hit-time model estimates with and without controls for birth propensity

Estimates of FHT model, based on the application of Xiao et al.’s (Reference Xiao, Whitmore and He2012) STATA package stthreg; the estimates were underpinned by 6,959 observations. Separate estimates presented for logit c, μ, and ln w 0. Standard errors in parentheses. Statistical significance: a 0.01, b 0.05, c 0.1, d 0.15.
The second component of the FHT model is the drift. The drift of the risk process toward the FHT boundary, represented by μ in the table, is generally quicker for women who have more older siblings and are in the top of the asset distribution (especially the fourth quantile). The same is true for more educated women. Although imperfect proxies, each of these variables can be related to income and marginal childbirth costs. A women with more older siblings is likely to have access to relatively less expensive childcare, and, therefore, drifts more quickly to the boundary, i.e., will have children more quickly, all else held fixed. In that regard, our estimates agree with our theoretical model’s intuition. The relationship between assets and education was also expected. Our theoretical model presumes that children are normal goods; thus, increases in income or proxies for income should be related to a general desire for more children (once the initial condition has been fixed), and, in our model, that is seen with increased drift toward the FHT boundary.
With respect to birth control, we find further evidence in support of the model. The costs of contraception matter; our empirical results support the finding that increased availability (decreased cost) of contraception is associated with a drift away from the boundary; in other words, increased availability slows down the time to first birth. Furthermore, women using more effective birth control methods drift more slowly toward childbirth. Furthermore, there is an additional education benefit with respect to contraception use, in that more educated women find their contraception working better, i.e., the interaction applies further brakes to the drift process. The implication is that more educated women use contraception more efficiently than their less educated counterparts.
One caveat, however, should be noted about the availability of contraception. Availability is taken at the time of the survey. Therefore, unfortunately, availability may not match directly to the time period of interest for all women in the survey, which means those variables are, at best, noisy measures of contraception availability. Given that noisy measures are associated with attenuation bias, the statistically significant results still provide support for our main hypothesis that the costs and availability of contraception are associated with the drift toward conception, and, subsequently, birth.
In the final column of the table, we present an estimate of the overall propensity to give birth, which parameterizes censoring. Each model presented in the table accounts for censoring – women who have not given birth up to the time of the 2007 DRC DHS – but only Model 2 parameterizes it through a logit model. The estimates suggest that being married at older ages is associated with a decrease in the probability of ever giving birth; such women are more likely to be censored.
3.3. Sensitivity Analysis
In the preceding discussion, we focused on the results presented in Table 2. It is possible, however, that wealth might affect a woman’s ability to access contraception or that wealth, education, and other characteristics of the mother could provide additional insight into the propensity for childbirth. In two additional tables (see Table 3 and A.1), we consider those possibilities.
First hit-time model estimates including controls for birth propensity: Sensitivity check I

Estimates of FHT model, based on the application of Xiao et al.’s (Reference Xiao, Whitmore and He2012) STATA package stthreg; the estimates were underpinned by 6,959 observations. Separate estimates presented for logit c, μ, and ln w 0. Standard errors in parentheses. Statistical significance: a 0.01, b 0.05, c 0.1, d 0.15.
Initially, we extended Model 2 to further parameterize childbirth censoring. In Models 3 and 4 – see Table 2 – we include a number of additional female characteristics, such as wealth, the woman’s total number of siblings (to control for the mother’s experience with family size growing up), the woman’s education and her initial experiences with sex, such as whether or not her first encounter was forced, whether or not she was a virgin when she married and whether or not she moved from a rural to an urban residence. The results are reported in columns 3 and 6, labeled “c”. With the exception of moving from a rural childhood residence to an urban adult residence, none of the other variables offers statistically significant insight into the birth propensity. It is still the case that women married at older ages are more likely to be childless than women married at younger ages.
In addition to extending Model 2 to further parameterize censoring, we also examined the possibility that wealth influences a woman’s ability to access contraception. Even though contraception might be available in the region, it might not be “practically” available, because a woman might not be in a position to afford it.Footnote 9 Thus, we interacted wealth and contraception availability when estimating the drift, μ; see column 5 under Model 4 in Table 3. As expected, including the interaction terms influences the initially reported wealth estimates, as well as the effect of contraception availability. After including the interaction effect, the results suggest that availability really only matters for those in wealth quintile 3. Plausibly, those in the poorer quintiles may be unable to afford contraception, even if it is available, while those in the upper wealth quintiles are able to find and access contraception, even if it is not widely available. In other words, these results could signal that there is positive wealth gradient associated with accessing contraception.
Although the inclusion of these additional variables provides for additional nuance in interpretation, a common theme in the discussion surrounding Models 3 and 4 was the lack of statistical significance. That theme receives additional support through the comparison of AIC values. Although, based on the reported AIC values, Model 3 provides a slight improvement in fit over Model 2, Model 4 does not. The appendix provides the results from two additional models, but neither of those models offers improvement, based on AIC values.Footnote 10 For that reason, the remainder of the discussion is based on the results reported in Model 3.
4. HAZARDS AND PROBABILITIES OF FIRST CHILDBIRTH
In the preceding analysis, we found empirical support for our theoretical model. However, as with most non-linear models, the parameter estimates provide little information regarding the behavior of the underlying non-linear function. In this case, the parameters cannot tell us how much the underlying birth hazard or birth probability are affected. Therefore, we present a few different scenarios to provide further insight into the time to first birth in the DRC.
One of the reasons for estimating the threshold model is that it allows for non-proportional hazard rates. As we will see in each of the following figures, estimated hazards for different groups are not proportional; they even cross in some cases. The figures we present; see Figures 2–4 are based on three separate scenarios. In Figure 2, we consider the type of contraception, which we refer to as contraceptive efficacy. We assume that modern is more efficacious than traditional, which is more efficacious than none. In order to provide some insight into the effects of contraception effectiveness, we separate the observations into three separate groups: those who have never used contraception before, those who used traditional methods before giving birth to their first child, and those who used modern methods before the birth of their first child. As seen in Table 1, there are differences in the samples, and those differences are statistically significant. In other words, there is “selection on observables” in the choice of contraception, which means our analysis is unlikely to yield causal estimates. Given the differences, we use the mean of the data from each of the samples for the prediction of ln w 0, μ, and logit c, which is used to predict the inverse Gaussian probability density function and survival function. The results are broadly as expected. The birth hazards fall with contraception effectiveness, as does the probability of giving birth by any particular point in time.
Birth hazard and probability of giving birth for women, based on the reported contraception used before first child was born (in some cases, the woman has not yet given birth). Figures are predicted at the mean of the data for each level of effectiveness. Estimated parameters are reported in Table 3 (Model 3). (a) Birth hazard. (b) Birth probability.

Birth hazard and probability of giving birth for women, based on the reported “availability” of birth control in the area. Figures are predicted at the mean of all the data. High availability requires that there is less than 10% unmet need in the region, while low availability requires that there is at least 35% unmet need in the region. Estimated parameters are reported in Table 3 (Model 3). (a) Birth hazard. (b) Birth probability.

Birth hazard and probability of giving birth for women depending on the predicted “initial risk” of giving birth, which is based on ln w 0. High risk represents those in the top quarter, while low risk represents those in the bottom quarter of the predicted values. The figures are predicted based on the mean of the analysis data in those three risk groupings. Estimated parameters are reported in Table 3 (Model 3). (a) Birth hazard. (b) Birth probability.

In the second scenario, we focus on the availability of contraception. The illustration in Figure 3 is based on a different split of the data. In this analysis, there are two groups: those who have relatively good access to contraception, in the sense that it is highly available, and those who have relatively poor availability. The measure is with respect to the percent unmet need, which is a local construct [see Bradley et al. (Reference Caldwell2012)]. If there is 10% unmet need, or less, women are assumed to live in an area where there is relatively good access. On the other hand, if there is less 35% unmet need, women are assumed to live in an area where there is relatively bad access.Footnote 11 For the predictions, we hold all of the control variables at their overall sample mean, with the exception of contraception availability, which is its mean value from each of the “poor” access and “good” access subsamples. As expected, availability matters. The figure shows a peak hazard rate difference around 5% or so, that occurs around 2 years after first sexual intercourse.
In the third scenario, we focus on initial risk, the underlying prediction of ln w 0. For this scenario, illustrated in Figure 4, the predictions are split into three groups – low, moderate, and high risk – depending on the predicted values. High risk are women in the lower 25% of the distribution, while low risk are in the upper 25% of the distribution; recall that larger initial values are further from the boundary, and, therefore, imply reduced risk. After separating women into these three groups, we predicted the various probability functions setting the observed covariates to their sample-specific mean values. Again, this is done because there is some choice in our measure of initial risk, and, therefore, the samples could be selective. Therefore, we feel it is appropriate to allow for mean differences. Although our results do not represent the causal impact of risk, they still provide an accurate representation of the relationship between risk and time to first birth.
It is natural to think that women in the low-risk group start their reproductive history with a “wait and see” attitude and have higher expectations of the contraception related benefits than the other groups. Using the mean (by risk group) of the individual estimated values of the parameters w 0 and μ, we show that the average low-risk woman is characterized by a delay in her childbirth hazard, before starting to catch-up with those of the average woman in other groups with higher risk. This confirms a stylized fact related to the delay in childbirth hazard for low-risk groups that has been reported by other scholars [see Aalen et al. (Reference Aalen, Borgan and Gjessing2008), p. 414]. As a consequence, the probability of the onset of motherhood by any given time is clearly lower for those women who start their active sexual life with higher expectations of contraception related benefits, than for those women who start with lower initial values of the expected future benefits linked to contraception.
5. CONCLUSION
In this paper, we outlined a model for birth timing that was based upon the stochastic nature of the human reproductive process and allowed for contraception decisions. Its empirical counterpart, based on FHT, was estimated using threshold regressions. The empirical analysis focused on the duration to first childbirth using data from a high fertility country in Africa, where there is evidence that birth intervals and the fertility transition is rather different than in other parts of the world [see Romaniuk (Reference Romaniuk2011), Moultrie et al. (Reference Moultrie, Sayi and Timaeus2012), Bongaarts and Casterline (Reference Bradley, Croft, Fishel and Westoff2013)]. Our empirical results suggest that contraception effectiveness and the efficiency with which it is used increases the duration from first intercourse to first childbirth. As expected, the use of more effective modern contraceptive methods by more educated women result in the postponement of the onset of motherhood. The question is of importance, because optimal birth timing, and ultimately optimal family size, is achieved through the practice of birth control.
Although an important aim of the paper was to develop a model of contraceptive use and test its relevance in explaining the puzzling negative relationship between income and family size, we were also interested in using the model to examine the slow fertility transition in the DRC. We have shown that our model and findings can be used as an additional building block in explaining the aforementioned puzzle. Contraception has benefits for women, and women who can access these benefits are in a better position to manage their fertility. Including contraception in the model creates an indirect link from income to contraception to fertility. In our empirical model, we find evidence that children are normal goods, in the sense that once the initial risk of childbirth is set, women with access to greater economic resources drift more quickly to the childbirth boundary; however, that is tempered by their ability to use contraception and use it more effectively, which allows women to initiate childbirth later. Furthermore, our empirical model supports the finding that increased contraception costs and reduced childrearing costs will both lead to reductions in the time to first birth, with the negative implication of greater total fertility.
By applying our model and analysis to the DRC, we are able to provide some insight into its slow fertility transition. Although our research cannot directly account for either the First (1996–1997) or Second (1998–2003) Congolese Wars, there is no doubt that these wars, and the rapes associated with the wars, have had disastrous consequences for women [see Baaz and Stern (Reference Becker2009), Mukwege and Ngini (Reference Mukengere Mukwege and Nangini2009)]. However, there is some indirect evidence regarding the effect of war on hastening the fertility transition, since our analysis suggests that forced sexual encounters result in women being less likely to give birth. Despite the atrocities visited upon women during these wars, and the effect this has likely had on the fertility transition in the DRC, our research is able to offer a few policy suggestions to hasten the transition. First, improve access to female education. Shapiro and Tambashe (Reference Shapiro and Tambashe2001) find large gender differences in educational attainment, even when there are improvements in economic status. Our research suggests that educated women start childbearing later, and are better able to use even less effective contraception. Even though more educated women drift more quickly to contraception stoppage, they start that drift from a much higher level, and the level effect outweighs the drift. Second, improve access to modern contraception, as improved access is associated with increased times to first birth.
Although this research provides new insight into the fertility–income puzzle, our analysis did not explicitly account for the quality–quantity trade-off that women might take into account in their optimal family size decision calculus, which suggests at least one direction for future research. In particular, one could allow child related benefits in the model to depend on parity or on the expected costs of child quality. Furthermore, our analysis does not consider higher parity birth intervals, primarily because of data limitations. Extending the model to account for these additional considerations could provide further insights into family formation, and the fertility transition.
In addition to the aforementioned theoretical extensions, additional empirical research is needed to confirm our results, and, where possible, provide causal evidence, as well. Although repeated analysis for additional countries, using DHS data, could corroborate the preceding evidence, the real limitation of this and any similar analysis that might be repeated in other countries is that the DHS does not follow young women over a reasonably lengthy period of time. For that reason, we cannot observe individual-level contraception usage and fertility dynamics; such data would necessarily improve our understanding, benefit our models and policy advice. Given the limitations in the data, we are not able to present causal evidence that improved access, for example, will lead to greater uptake of (modern) contraception, which will hasten the fertility transition. Similarly, we are not able to provide causal evidence that improving female education, possibly with the inclusion of reproductive health education, hastens the fertility transition, even though our evidence is highly suggestive. Thus, a national DHS-style panel in a high fertility country, like the DRC, would be beneficial to this research agenda.
Compliance with Ethical Standards: Funding: This research was supported by the William and Flora Hewlett Foundation under grant G15085485. This research was further supported by Economic Research Southern Africa. The views expressed in this document are solely those of the authors, and not those of the funders.
Conflict of Interest: The authors declare that they have no conflict of interest.
A. ADDITIONAL ANALYSIS
First hit-time model estimates including controls for birth propensity: Sensitivity check II



