1 Introduction
In the last 2 decades, priority setting in health care has increasingly become a hotly debated issue in academic and practical-political contexts alike. Since the late 1990s, a consensus seems to have been established on the assumption that substantial principles of distributive justice in health care and elsewhere remain fundamentally contested and are not fine-grained enough to guide concrete allocation decisions (see Holm, Reference Holm2000; Daniels, Reference Daniels2008: Ch. 4). Accordingly, the focus shifts from substantial principles to criteria of procedural fairness, with Daniels and Sabin (Reference Daniels and Sabin1997) suggesting their influential framework of ‘accountability for reasonableness’ that serves as a standard for fair decision-making procedures. Institutions like the British National Institute for Health and Care Excellence (NICE) have taken the political demands deriving from the accountability-for-reasonableness framework seriously and have implemented a number of measures that increase transparency, accountability and stakeholder involvement. While these measures surely improve the ‘throughput legitimacy’ (Schmidt, Reference Schmidt2013) of an essentially non-majoritarian institution like NICE, it remains to be seen how they will bear on the public acceptance of its decisions.
Our starting point is different from Daniels and Sabin’s: We assume that institutions necessarily entail biases, meaning that they will benefit certain interests more than others. When a new agency is set up from scratch – as NICE and many other agencies charged with priority-setting decisions were – those who delegate respective tasks to it also inscribe it with norms and values that will bear on decisions. In the ideal case, these will be norms and values of the society which the agency is to serve. For example, a society in which utilitarian considerations enjoy strong support will chose a different institutional design from one in which distribution according to need is favored. In the less ideal case, delegators will also bring strategic considerations to bear and try to ‘lock in’ their policy preferences and to benefit partisan interests beyond their own term in office (see Moe, Reference Moe2005). In either case, however, institutional design may not match social values: either because delegators are ignorant of these values or because they deliberately choose institutional parameters at odds with them. And even if institutional design is democratic in the sense of being driven by societal values rather than strategic considerations of delegators, social values may change and agencies may develop internal dynamics that result in tensions between social and institutionalized values.
Our aim in this paper is mainly an exploratory one. Following a theoretical discussion of distributive principles in the allocation of health care and their implementation through institutional design (section 2), we look at three countries to assess whether social values regarding priorities in health care (section 3) are coherent or incoherent with the values institutionalized in the health care system in general and in priority-setting agencies in particular (section 4) and whether social values are reflected in the decisions of these agencies and the justification of their decisions (section 5). In the discussion (section 6), we address likely consequences of the incongruences we find and conclude that institutional design needs to be democratized if priority-setting agencies are to gain and maintain public support.
2 Social values and political institutions
Which social values play a role in the allocation of the scarce health care services? Following David Miller (Reference Miller1999), public health care systems may be conceived of as an institutionalization of a solidaristic community, in which a principle of distribution according to need is adequate. However, although need is clearly the central distributive principle where heterogeneous health care goods are to be allocated, a definition of what constitutes medical need is less than clear. Quite different forms of need have come to be accepted as constituting legitimate claims on resources, including needs for psychiatric and psychological treatment, the need for fertility treatment or the need for preventive check-up examinations. The increasingly broad specification of need is in keeping with the apparent willingness of developed societies to spend larger proportions of their income on health care and it is reflected in the World Health Organization’s (WHO) maximalistic definition of health as the ‘a state of complete physical, mental and social well-being and not merely the absence of disease or infirmity’ (Preamble to the Constitution of the WHO).
Nevertheless, the populations’ increasing expectations and the progress in medical research and technology have resulted in rising expenses that increasingly cause concern to governments, in particular in times of fiscal austerity. In consequence, other, and in the eyes of some, parasitic principles of distribution have entered the debate on the fair allocation of health services. The first one is the principle of efficiency, or value for money. While the clinical effectiveness of treatments is an obvious criterion for their public reimbursement, efficiency not only asks whether a treatment works, but also at what price to the collective it works. Efficiency considerations can be implemented in different ways, for example through the application of a quality adjusted life year (QALY) calculus that indicates the average costs of one life year (of good quality) gained by a treatment (Nord, Reference Nord1999). In practice, complementing or replacing a principle of need in the allocation of health care with efficiency criteria would imply funding less urgent or essential, but highly effective services that offer good ‘value for money’ and banning expensive but less effective services from funding, even if they are demanded by patients in urgent need (e.g. some last-chance cancer therapies).
A second principle that has entered the debate derives from the observation that rights go hand in hand with duties, and that in the context of health care, recipients of medical services have a responsibility to behave in ways that do not endanger their good health. This principle of personal responsibility for health (Roemer, Reference Roemer1995; Wikler, Reference Wikler2004) brings considerations of desert to bear in the distribution of health care. In contrast to the principles of need and efficiency, personal responsibility for health cannot serve to guide the overall allocation of health care in a society, but rather as an additional criterion in hard choices or decisions over very specific services. In practice, considerations of personal responsibility can be applied in either of two ways in allocation decisions. First, patients who are deemed responsible for their health problems could be asked to pay for respective treatments privately or to make higher co-payments. For example, a German law excluded the treatment of infected piercings and tattoos from reimbursement by the public health funds. Second, patients who have assumed responsibility for their health in adequate ways in the past could be given preferential treatment. For example, a non-smoker may be prioritized over a smoker in the treatment of lung cancer, thus implicitly reducing the prospects of the latter without explicitly banning his or her treatment from funding.
At the same time, however, there also seems to be increasing concern about inequalities in access to health care and unequal chances for good health. Considerations of equality and equity in health care have thus gained significance not only where the organization of the health care system as such is concerned, but also with regard to the allocation of resources within the system (Culyer and Wagstaff, Reference Culyer and Wagstaff1993; Sen, Reference Sen2002). Like the principle of personal responsibility for health, considerations of equality and equity cannot serve as a singly guiding criterion in allocation, but rather as an additional criterion or corrective. In practice, these considerations may entail a priority for services aimed at disadvantaged groups, such as addiction therapy, and for preventive services that could reduce inequalities in health prospects, such as health education programmes. Under a fixed budget, preferential funding for such services will implicitly change the overall allocation of health services to the disadvantage of other patient groups.
While one may regard all of these principles – the fundamental principle of distribution according to need, and the supplementary principles of efficiency, personal responsibility for health and equality and equity – as a basis for legitimate considerations about the fair allocation of resources, they run into conflict as soon as they are to be contextualized and applied. There is a broad body of philosophical literature on the hard choices to be made in the comparative evaluation of claims to medical services under scarce resources, which cannot be recapitulated here (but see Daniels, Reference Daniels2008 for some vivid examples). What is relevant in this context is that governments in most OECD countries have delegated the intricate task of weighting competing principles of just distribution in the assessment of medical technologies to specialized agencies, which are charged with defining lists of medical services, or health baskets, covered by the public health care system (Landwehr and Böhm, Reference Landwehr and Böhm2011). These agencies operate at arm’s length from the government and bureaucracy and are often statutorily independent. However, they are inscribed with values and programmed with distributive principles they are to apply in decisions. Such inscriptions may be explicitly spelled out in the mandate and statutes of an agency, or they may be implemented through institutional design. To use a somewhat blunt example: an agency staffed exclusively with health economists is more likely to apply efficiency considerations than one that is staffed with patient representatives. As Landwehr and Böhm have argued and demonstrated elsewhere (Landwehr and Böhm, Reference Landwehr and Böhm2011; Böhm et al., Reference Böhm, Landwehr and Steiner2014), the institutional design of appointed agencies is likely to have an effect on resulting decisions: institutions always entail biases that benefit some interests more than others and they define standards by which decisions have to be justified.
Assuming that decisions of appointed agencies need to reflect social values adequately in order to gain public acceptance (Clarke and Weale, Reference Clarke and Weale2012; Littlejohns et al., Reference Littlejohns, Yeung, Clark and Weale2012), the question of whether and how societal values are reflected in the institutional design of agencies and in their justification of distributive decisions gains not only academic, but also practical relevance. In our assessment of social values, institutions and decisions, we seek to assess the congruence between social and institutionalized values in three different countries – France, Germany and the United Kingdom – and explore the likely consequences of the incongruences we find. The case selection covers three types of decision-making bodies, differing mainly in terms of their composition, while ensuring a minimum of comparability in general structures and fields of activity: the French National Health Authority [Haute Autorité de Santé (HAS)] represents an expertocratic body, the German Federal Joint Committee [Gemeinsamer Bundesausschuss (G-BA)] consists of corporatistic actors, and the British NICE constitutes a pluralistic body.
3 Social values and health care: results from the International Social Survey Programme (ISSP) 2011
Although they are subject to lively academic and expert debates, the competing principles discussed above remain highly abstract and the issue of health care priority setting has – at least in two of the countries studied here (Germany and France) – not yet been subject to public discourses. Exploring attitudes on the allocation of health care thus constitutes a challenging task. However, the ISSP (2011) has recently conducted a series of surveys aiming to compare attitudes to health care in 32 countries. While the items used in the ISSP survey are not optimal for the purposes of our analysis, the survey does entail some items which we decided to use as proxies for more specific attitudes. In order to address all of the principles discussed above, we use a set of three questions per principle serving as indicator for the endorsement or refusal of each of the principles.Footnote 1 Although the ISSP data do not allow any far-reaching conclusions, we do believe that the significant differences between the three countries are indicative of country-specific social values and preferences over the allocation of health care.
Attitudes to efficiency criteria were measured by agreement or disagreement with the following statements: ‘The government should provide only limited health care services’, ‘People use health care services more than necessary’ and ‘In general, the health care system in [country] is inefficient’.Footnote 2 We view the first proposition as an argument in favour of limit setting, or rationing, in that it implies that only the most essential services should be funded while funding non-essential services wastes resources. This is in keeping with the classical utilitarian demand for efficiency-based optimization, which may also be seen as following from the other two propositions.
A similar construction was used to capture attitudes to equality criteria, where attitudes to the statements ‘Is it fair or unfair that people with higher incomes can afford better health care than people with lower incomes?’, ‘People suffer from severe health problems because they are poor’ and ‘People should have access to publicly funded health care even if they do not hold citizenship of [country]’ were used as proxies. With regard to the first proposition, we assume that people who think that it is unfair that people with higher incomes can afford better health care will consequently plead for equality of access. With regard to the second proposition we assume that people who see poverty as an important cause of health problems will conclude that this is unfair and that opportunities for good health should be equalized. The third proposition not only sheds a light on the preferences for equality, but also on the possible understanding of a right to health care: Either people have a more collectivist understanding in that they link entitlement to citizenship or tax-payment, with the consequence that persons who fail to meet these criteria will be excluded; or they share a more equality-orientated notion in that they favour an individualistic right independently of citizenship or community membership.
Concerning attitudes towards criteria of personal responsibility for health, we were able to use a set of rather straightforward items: ‘Are you in favour or against public funding of programs to prevent obesity?’, ‘Suppose two equally sick people need the same heart operation. One does not smoke, the other is a heavy smoker. In your opinion, who should get the operation first?’ and ‘People should have access to publicly funded health care even if they behave in ways that damage their health’. The relative percentages of agreement (or, for respective items, judgement of fairness or preferred allocation) were balanced with the respective counter positions, then classified on a scale from strong support to strong refusal, and finally aggregated, thus describing the population’s preferences as strongly or moderately in favour of/against or as indifferent to the specific principle. For better readability, percentages are rounded and aggregated results for each country are provided in Table 1.
Social values and health care: ISSP 2011

++=strong support; +=support; o=no clear preference; −=refusal.
3.1 France
The ISSP data for France indicate a moderate refusal of the efficiency principle, a high appreciation of equality issues and no definite position with regard to personal responsibility for health. Regarding attitudes to efficiency as a criterion, a majority of 70% agree that people use health care services more than necessary (14% disagree), which could be indicative of a rather positive attitude towards efficiency-based rationing. However, another 74% of the respondents refuse a limited public supply of health care services (13% in favour of), and yet another 69% disagree with the claim that the French health care system is inefficient (10% agree), thus in sum suggesting a rather dismissive attitude towards a strong efficiency calculus. With regard to equality considerations, at least 46% disagree with the idea of access to health care regardless of citizenship (36% agree). This tendency to reject what is essentially an egalitarian position contrasts with considerable opposition to economic inequalities in access to health care: when asked whether it is fair or unfair that people with higher incomes can afford better health care than people with lower incomes, 81% think it is unfair while only 7% think it is fair. Furthermore, 55% also recognize a relation between health problems and poverty (which 24% negate). Accordingly, we regard the principle of equality as strongly favoured among the French. Somewhat more ambiguous are attitudes concerning the principle of personal responsibility for health. When asked on the basis of concrete examples, a majority of 63% think that the smoking habits of two patients waiting for a heart operation should not make a difference (36% argue for the non-smoker). Moreover, a majority of 62% is in favour of publicly funded programmes for the prevention of obesity (16% against). When asked more generally, however, 50% reject the idea that people who behaved in ways that damaged their health should have access to publicly funded health care (26% vote in favour of). On this basis, the French attitude towards using personal responsibility for health as a criterion in allocation remains rather indeterminate.
3.2 Germany
Among the German respondents, the principle of personal responsibility for health seems to be rejected by a majority, whereas the principle of equality enjoys strong support and no clear or dominant position can be indicated with regard to efficiency. Analysing the latter in detail, a large majority of 73% argue against a limited state supply of health care services and thus rather against efficiency-based rationing (19% in favour of). But at the same time, a simple majority of 52% also agrees that people use health care services more than necessary (27% disagree). The third item was inaccurately translated into German and could not be used for our purposes in this case (respondents not asked whether the system is inefficient, but whether it ‘works well’). In sum, the ISSP does not provide a clear picture of the Germans’ attitude towards efficiency criteria. By contrast, equality considerations enjoy strong support in all three items used as proxies. More than two thirds (78%) think that it is unfair when people with higher incomes can afford better health care than people with lower incomes, while only 7% think that it is fair. Moreover, a large majority (67%) agree that people should have access to health care even without holding citizenship of Germany (19% against), and 51% recognize a close relation between severe health problems and poverty (which only 30% deny). Looking at attitudes towards personal responsibility for health, 40% of the respondents think that people should have no access to publicly funded health care if they behave in ways that damage their health, whereas 36% reject the idea. These rather heterogeneous attitudes converge towards rejection when respondents are confronted with a concrete case: A clear majority of 72% reject the idea of making access to treatment dependent upon smoking habits (although 27% would rather give the operation to the non-smoker), and nearly half of the respondents (49%) are in favour of publicly funded programmes to prevent obesity and thus reject personal responsibility as a criterion in allocation (27% are against such programmes). In sum, the distribution of health services by criteria of personal responsibility for health seems to be refused in Germany.
3.3 United Kingdom
For the British population the survey data suggest a moderate support of the principles of equality and personal responsibility for health, but no clear trend with regard to efficiency. In all, 58% of the respondents think that people use health care services more than necessary (15% disagree), suggesting attitudes in favour of efficiency criteria, but at the same time, a large majority of 76% are opposed to limiting public supply of health care (only 10% are in favour). Owing to the nearly equal shares of agreement (34%) and disagreement (36%) in case of the third question (whether the British health care system is generally inefficient or not) attitudes towards efficiency appear rather heterogeneous. In terms of equality, only 18% support the idea that access to health care should be granted regardless of citizenship, whereas a majority of 63% reject the idea. Although 46% think that is unfair if people with higher incomes can afford better health care than people with lower incomes (29% think it is fair), and 44% agree that people suffer from severe health problems because they are poor (26% disagree). In comparison, the support for equality considerations in the distribution of health services seems to be moderate in Britain. By contrast, criteria of personal responsibility for health enjoy strong support among the respondents. Only in case of the question about publicly funded programmes for the prevention of obesity, a small majority of 44% are in favour of funding and thus do not support responsibility as a criterion for allocation (30% are against public funding). The other two items display attitudes in favour of personal responsibility: 63% would grant the heart operation to the non-smoker, while 36% think smoking habits should not make a difference, and 51% think that people should not have access to publicly funded health care when they behaved in ways that damaged their health (26% disagree).
4 Social values in health care institutions
Assuming that institutions reflect societal values and should be, at least in part, instrumental to shared goals, we now look at institutions in the health care system of each country, asking which values and goals are inscribed into institutions at different levels. We begin by considering general principles in the organization of health care before taking a closer look at the procedures used in allocative decisions. Here, we consider legal regulations as well as internal rules of procedure that define distributive principles and criteria for allocation. Finally, we assume that the institutional set-up and in particular the composition of the bodies that are charged with decisions on the public reimbursement of controversial services (and thus distributive decisions) reflect certain values and goals.
4.1 France
Combining elements of the Bismarck and the Beveridge model, the French health care system is based on the ideas of universality, equality and solidarity. Article L1110-1 of the Public Health Code pronounces the fundamental right of every person to health care, demanding equal access without discrimination, and in Article L.111-2-1 of the Social Security Code ‘the nation affirms its attachment to the universal, mandatory, and solidary character of the sickness insurance’ (translation by the authors). Reimbursement decisions are actually taken by the Ministry of Social Affairs and Health on the basis of recommendations prepared by the HAS and its subcommittees; the National Union of Sickness Funds only takes decisions on the level of reimbursement. According to the legal provisions, the recommendations of HAS are to consider the effectiveness of a drug, its therapeutic value in comparison to alternative treatments, the severity of the condition, the curative, preventive or symptomatic qualities of the drug, as well as its relevance in terms of public health. The HAS itself has thus developed the concepts of actual benefit Service Médical Rendu (SMR) and clinical added value Amélioration du Service Médical Rendu (ASMR). While the latter merely measures the additional benefit in comparison to treatment alternatives, the former combines criteria of utility such as the ones named above (the effectiveness of a drug, the expected impact on public health) with criteria of need, mainly in terms of the severity of condition (HAS, 2011: 12f). Within the HAS, the appraisal of pharmaceuticals is conducted by the Transparency Commission (CT), which is, like the board itself, staffed mainly with clinical researchers and practising physicians. Representatives of the ministry, the sickness funds and the pharmaceutical industry may take part in meetings, but have no voting rights, whereas patient representatives are not included at all. Taking all three dimensions together, the French institutional design can be characterized as focusing strongly on utility – but not on efficiency – and need, acknowledging that both build the basis for defining the SMR. In contrast, equality consideration seem to play a role on a rather abstract, constitutional level, without a concrete pendant on a more narrow institutional level, whereas personal responsibility for health seems to play no role at all.
4.2 Germany
The regulatory framework of the German public health care system, the prototype of a social insurance system, is codified within the fifth social code book (SGB V), where in §1 the principles of solidarity and personal responsibility are named as constitutive norms. The kind of personal responsibility referred to in §1 of the SGB V was originally probably more concerned with the input side of the system, that is the responsibility to hold an insurance as a protection against the risk of disease. More recently, however, this principle has been re-interpreted as a personal responsibility for health-damaging behaviour: in 2007, the legislator introduced a limited reimbursement for ‘self-inflicted diseases’ (§52, SGB V) and complemented this with a further regulation that obliges doctors to report health-damaging behaviour to insurance funds (§294a, in force since 2008). With regard to the public funding of services, §12 SGB V determines an ‘imperative of economy’ according to which only services that are sufficient, appropriate and necessary are to be financed. The specification and application of these general norms is delegated to the Federal Joint Committee (FJC), a body that takes decisions on the exclusion of medical services from the public health basket. The appraisal of medical necessity, usefulness and economic viability is based on an estimation of utility – not merely effectiveness – in comparison to alternative treatments, with evidence-based medicine serving as standard for evaluation (chapter 4, §§6, 7, 9, 10 FJC rules of procedure). But even if the cost-utility ratio is generally considered by the FCJ, a uniform standard of economic evaluation or fixed thresholds could not be established (Zimmermann, 2012: 275). A perceived need for more (neutral) expertise on efficiency is also reflected in the establishment of an ‘Institute of Quality and Efficiency in Health Care’ (IQWiG) in 2004 which is to support the decision-making process by providing scientific reports and information. The FJC is constituted by representatives of service providers and sickness funds on the basis of parity. These two opposing ‘benches’ are flanked by three formally independent expert members, one of them chairing the board, and by representatives of patient organizations without voting rights. This constellation suggests two things: On the one hand, one of the central trade-offs in the distribution of health services is institutionalized in the FJC itself, as service providers – commonly viewed as advocates of the patients and thus representing need – and representatives of sickness funds – usually associated (or branded) as solicitors of efficiency – stands vis-à-vis. On the other hand, the inclusion of independent experts and, at a later date, patient representatives, displays intentions to give weight to expertise (on clinical effectiveness) and to realize a more inclusive decision-making process in which perspectives of patients and disadvantaged groups are taken into consideration. In sum, efficiency and personal responsibility are embraced by the legislator at an abstract level in the social code book IV. Efficiency considerations, however, meet with reservations at the meso-level of concrete allocation decisions. Equality considerations do not play a significant role at the institutional level, even if the recent expansion of the FJC to include patient representatives suggests an increasing sensitivity for matters of equality in health care provision.
4.3 United Kingdom
Retrospectively, the idea of a social right to health care that guarantees free, universal, and equal access was central to the foundation of the British National Health Service (NHS) in 1949. This key principle was confirmed and strengthened in the NHS constitution of 2013 that stipulates ‘a wider social duty to promote equality […] and to pay particular attention to groups or sections of society where improvements in health and life expectancy are not keeping pace with the rest of the population’ (DoH, 2013: 3). Besides thus stressing equality, the constitution also pronounces the obligation to efficiency by ‘providing best value for taxpayers’ money and the most effective, fair and sustainable use of finite resources (NHS, 2013: 3). Below this ‘constitutional’ level, the National Institute of Health and Care Excellence (NICE) takes decisions on the appraisal of controversial technologies for public reimbursement. NICE is to consider the balance between clinical benefit and costs, the degree of need among patients and the potential of long-term innovation to the NHS. Its decisions have to be generally grounded on (scientific) evidence and contribute to the reduction of inequalities (NHS, 2005). For measuring and comparing the cost-effectiveness of technologies, NICE uses QALYs in combination with more or less fixed thresholds [International Centre for Economic Research incremental cost effectiveness-ratio (ICER)], reasoning that only this approach guarantees fair, transparent and cost-effective decisions (NICE, 2008: 32–39). But while in 2008, NICE refrained from using a rule of rescue since it would infringe on the logic of equity weighting, it has meanwhile in part departed from fixed thresholds in cases of life-threatening conditions, although it has specified certain preconditions that must be fulfilled (commonly known as end-of-life-criteria, see NICE, 2008), implying that it is not an unconditional rule of rescue. Criteria such as desert or personal responsibility for health, by contrast, are explicitly ruled out by NICE (NICE, 2008: 23f).
The strong concern with equality is also evident in the procedural dimension of institutional design. The Technology Appraisal Committees of NICE, which prepare the recommendations, are staffed not only with experts and bureaucrats, but also with representatives of patient organizations, physicians’ associations, the pharmaceutical industry, as well as with lay members (citizens), thus including important stakeholders and trying to ensure that different perspectives are considered. This demonstrates not only a comprehensive understanding of the decision problem, but further suggests that the different distributive principles are represented by specific actors: Physicians and patients represent need criteria, clinical experts effectiveness, NHS bureaucrats and health economists efficiency, and lay members bring equality considerations to bear. Overall, the British institutional design expresses a strong concern for efficiency, but also for equality, since both are not only stipulated at the superordinate level of the NHS constitution and embraced as explicit decision criteria, but also manifested in the composition of the committees within NICE. In contrast, the principle of personal responsibility for health is explicitly rejected (Table 2).
Social values in health care institutions

++=strongly inscribed;+=inscribed; o=no clear statement; −=excluded.
5 Social values in the justification of distributive decisions
In our assessment of value congruence in the allocation of health services we now finally look at allocation decisions taken by respective bodies and, more specifically, at the way in which these decisions to publicly fund or not to fund a controversial service were justified with reference to different distributive principles. For this analysis, we have selected a number of controversial drugs for the in- or exclusion of which different rationales can be constructed from the different distributive principles. The idea behind our strategy of assessing justifications for a set of decisions in each country is that we keep the subject of decisions (six drugs) stable between the countries while avoiding biases that might accrue when looking at a single drug that is controversial in only one dimension (e.g. with regard to its efficiency). Our assumption is thus that for each of the controversial drugs, one rationale or justification with regard to a specific distributive principle, suggests itself. The extent to which justifications stress this principle or instead depart from it by referring to competing principles is thus assumed to reveal the comparative weight attached to this principle and respective criteria in decisions. Our analysis here focuses on drugs (rather than other medical services) as they not only constitute one of the biggest cost drivers within the health budget, but are also more regularly and on a larger scale assessed than other services.
The conflict between the distributive principles of need and efficiency is particularly apparent in the case of end-of-life diseases, where high-tech drugs promise a longer life, but no cure. We therefore considered decisions on two very expensive cancer drugs, Trastuzumab for the treatment of terminal gastric cancer and Temsirolismus for the treatment of terminal renal cell carcinoma. We further chose the drug Teriparatide for the treatment of postmenopausal osteoporosis, a very common and severe, but not fatal disease that affects mainly elderly women. For cases in which issues of equality are particularly relevant, we considered two drugs for diseases leading to severe disabilities: Memantine for the treatment of Alzheimer’s disease and Natalizumab for the treatment of multiple sclerosis. Finally, we looked at decisions on Vareniclin, a drug used to assist smoking cessation, which is controversial with regard to issues of personal responsibility for health.
Methodologically, the reports in which the committees charged with technology appraisal justify their decisions on these six drugs were analysed in all three countries. Justifications were analysed using a method of argumentation analysis suggested by Bayer (Reference Bayer2007), which groups arguments into different categories according to the way in which they relate to the competing distributive principles and corresponding criteria. The sections below provide an overview over the principles and criteria that dominate justifications in each of the three countries.
5.1 France
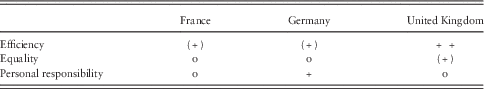
The French CT recommends the funding of all six drugs; only in the case of Teriparatide, funding is tied to certain conditions. A common characteristic of the argumentation is the linkage of utility considerations with issues of need, merging together in arguments of public health. Need is addressed under two different aspects: first, in more qualitative terms with regard to the severity of the condition and the burden on the person affected, and second in more quantitative terms with respect to the total number of people affected and the burden on public health (morbi-mortality). To these aspects of need, the commission relates the estimated effectiveness of the drug, judging whether an impact on morbi-mortality is to be expected or not, and, subsequently, whether the public has an interest in the funding of the drug or not. However, for all decisions considered here, the weights that the reports assign to the single aspects seem to be strongly in favour of the criterion of need. Thus even in cases where a public interest is contested due to doubts about the drug’s effectiveness, as in the case in Memantine (Alzheimer’s disease), the commission argues that in consideration of the severity of the disease and the ‘structuring role’ of Memantine within the larger context of Alzheimer care the actual benefit is important (CT-5952: 9). Similarly, the recommendation of Temsirolimus (renal cell carcinoma), whose impact on the morbi-mortality is assessed as rather small, is justified by the poor prognosis the patients have and thus their urgent need (CT-5270: 7). And in the case of Natalizumab (multiple sclerosis), the commission reasons that despite the safety concerns, and even if the eventual impact on public health remains to be seen, the actual benefit has to be seen as important in consideration of the few available treatment alternatives (CT-11948: 16). Remarkably, efficiency arguments – whether in terms of cost-effectiveness or in terms of budget impact – could neither be identified in these cases nor in the case of Teriparatide (osteoporosis), where funding with a reduced subsidy rate of 65% was recommended. Arguments in favour of using criteria of personal responsibility could not be identified either, although they could have been expected in the case of Vareniclin for smoking cessation (CT-4154).
5.2 Germany
The FJC decided to exclude Vareniclin for smoking cessation as well as Memantine for Alzheimer’s disease from public funding, although in case of the latter some exceptions were admitted. Funding for Temsirolimus (renal cell carcinoma), Teriparatid (osteoporosis) and Natalizumab (multiple sclerosis) was tied to certain conditions. On Trastuzumab, no decision was taken. As Germany uses a negative list for drugs (listing only drugs excluded from funding), this means that Trastuzumab is publicly funded for patients with gastric cancer in Germany. In all cases, arguments centred on evidence-based effectiveness, although this was not the sole criterion considered (which would have implied some kind of decision-making automatism). Instead, arguments based on effectiveness or utility were partly fenced or flanked by efficiency arguments, or outbalanced by arguments of need. What becomes apparent here is a scheme of recommending drugs with proven effectiveness while justifying restrictions with efficiency arguments, and rejecting drugs without proven effectiveness while granting exceptions in cases of urgent need.
Illustrating the former case, the FCJ acknowledges the effectiveness of Natalizumab (multiple sclerosis) and Temsirolimus (renal cell carcinoma), but argues at the same time that in consideration of the safety profile and the high costs, the usage is economically viable only in severe cases (FJC 09.04.2009: 1304), or in cases where the likelihood of beneficence is higher than the likelihood of maleficence (FJC 17.09.2009: 3), thus merging a classical argument of medical ethics with efficiency calculations. A similar argumentation is also found in the case of Teriparatide for postmenopausal osteoporosis, where effectiveness is viewed as proven, yet with reservations in terms of comparative additional benefit. In pronouncing that the daily treatment costs exceed the costs of conventional treatments by nearly 35 times, the FJC concludes that the use of Teriparatide is generally not economically viable, restricting the funding to second-line treatment (cases where patients for various reasons do not respond to standard treatment) (FJC 21.11.2006: 2). This decision also sheds a light on the notion of need applied, which understands need mainly in terms of availability of treatment alternatives, as well as on the weighting of utility and efficiency considerations with issues of need: Even though the treatment is extremely expensive, the committee decided that in cases of severe clinical need, namely when alternative treatments fail or patients are not suitable for treatment alternatives, the drug should be financed. This weighting, or rather the emphasis on such need-related arguments, becomes even more apparent in the case of Memantine (Alzheimer’s disease), demonstrating that issues of need can overrule doubts about utility or efficiency, even if effectiveness is not scientifically confirmed. Thus the FJC decided not to fund Memantine on the grounds that ‘a benefit whose effectiveness cannot be seen as proven is in consequence not medically required, the more so as there are available treatment alternatives’ (FJC 10.08.2010: 10; translation by the authors). But despite this negative judgement, the commission permits exceptions for patients with a severe type of AD due to the unavailability of treatment alternatives in these cases.
Need in terms of the severity of disease, by contrast, seems to play a role only on a more hidden level, in that requirements of evidence-based medicine were not as strictly handled in case of the cancer drug Temsirolimus as in the case of, for example, Teriparatide. This impression is confirmed in the report on Vareniclin for smoking cessation, which the FJC classifies as a lifestyle drug and therefore excludes from funding without even considering its effectiveness or economic viability. The classification as ‘lifestyle drug’ can be seen as an application of the principle of personal responsibility for health (FJC 18.01.2007). By contrast, arguments referring to equality criteria could not be identified at all.
5.3 United Kingdom
Put briefly, NICE recommends Vareniclin for smoking cessation and rejects Temsirolimus for renal cell carcinoma while restricting the funding of the remaining drugs to specified patient groups. In its justifications, NICE generally stresses a spectrum of reasons ranging from considerations of need and equality to ones of utility and efficiency. Only arguments relating to considerations of personal responsibility for health cannot be found at all. In sum, the most substantial weight is given to arguments of efficiency in terms of cost-effectiveness. Thus, in case of the two cancer drugs, the committee argues that the end-of-life criteria can be applied and acknowledges a strong clinical need in patients with renal cell carcinoma due to the bad prognosis and the existence of only one available treatment alternative that in addition is less effective while highly toxic (NICE-TA178: 37f). But despite of the fact that all end-of-life criteria are fulfilled, NICE rejects the funding of Temsirolimus on grounds of an unacceptably high ICER of £102,000 per QALY gained (NICE-TA178: 44), and restricts the funding of Trastuzumab to a small subpopulation, where an ICER of £45,000–£50,000 per QALY gained is seen as acceptable in contrast to an ICER of £63,100–£71,500 per QALY gained for the whole patient population with gastric cancer (NICE-TA 208: 34f).
In contrast, in cases where the ICERs exceed the normal range only marginally, arguments stressing need and also equality considerations can apparently partly modify reservations on the cost-effectiveness. For instance, the committee argues in case of Natalizumab (multiple sclerosis) that the (actually not cost-effective) ICER of £32,000 per QALY gained can be seen as cost-effective when considering the ‘degree of clinical need among people […] and the innovative nature of technology’ (NICE-TA127: 12). A similar reasoning can be found in the case of Memantine (Alzheimer’s disease), where the committee acknowledges the clinical need among patients and – despite considerable doubts of the Evidence Review Group with regard to the drug’s effectiveness – stresses that the ICER could be lower if positive effects on the quality of life were included in the economic modelling (NICE-TA217: 66). Moreover, the argument that access to a medicinal treatment would enhance the access to a broader spectrum of (non-medicinal) benefits, which is currently highly unequal across the country (NICE-TA217: 46), may be seen as conducive for deciding in favour of funding Memantine. With regard to equality criteria, the committee, while frequently stressing the importance of equality, does not seem to make arguments of equality decisive in decisions to fund or not to fund a drug. The case of Teriparatide (for osteoporosis), which is recommended only as fourth-line treatment for patients at high risk, also demonstrates that arguments related to equality cannot overrule doubts on the cost-effectiveness – a pattern that is confirmed by the decisions on cancer drugs in relation to need. In these cases, the committee recommends that patients who are not suitable for the conventional treatment due to disability or contraindications should be treated like patients who did not respond to the standard treatments, since they would otherwise be unfairly disadvantaged in not getting access to treatment at all. Again, while stressing the need to ensure fair chances and to ‘promote equality of opportunity for disabled people’ (NICE-TA 161: 72), the committee rejects the equalization of patients with disability or contraindications, but without an increased risk, arguing that it ‘would not be justified in this case because of the very high ICERs’ (NICE-TA 161: 73). Thus, efficiency concerns obviously overrule considerations of equal access, although a notion of ‘fair chances’ is integrated into efficiency assessments. The priority of efficiency over other distributive criteria is also demonstrated in the decision on Vareniclin, which is assessed like all the other drugs and ultimately recommended, as the ICER seems acceptable to the commission (NICE-TA 123: 5) – arguments about personal responsibility for health were not mentioned (Table 3).
Social values in justifications of distributive decisions
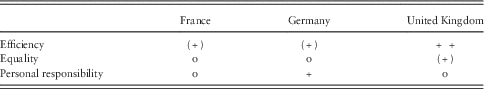
++=strongly decisive; +=decisive; (+)=plays a role, but rather diffuse; o=not mentioned.
6 Discussion and conclusions
Comparing the three countries, social values in the population seem to be mostly congruent with institutionalized values and decisions in the United Kingdom, less congruent in France and rather incongruent in Germany. In the United Kingdom, the support for efficiency and equality criteria is reflected in the institutional design of the health care system at large and in the design of NICE as the central institution in technology appraisal in particular. NICE decisions and their justification in comprehensive reports also reflect the focus on efficiency and stress equality, albeit without making equality considerations decisive. Criteria of personal responsibility for health enjoy some support in the British population, which is not reflected in institutional design or decisions. In France, the rejection of efficiency considerations is reflected only in so far that efficiency criteria are not made decisive in decisions. The strong concern with equality in health care that becomes apparent in the ISSP data fails to be reflected at the institutional level and in decisions. In Germany, social values in the population seem to be completely at odds with institutionalized values and decisions: The institutionalization and use of efficiency criteria in decisions does not seem to supported by ISSP respondents (although the picture remains unclear here). At the same time, the strong concern with equality is not at all reflected in institutions and decisions, while the rejection of personal responsibility for health as a criterion in allocation decisions is discrepant with institutionalized norms and justifications for decisions.
On the basis of these results, we would expect priority-setting institutions and their decisions to enjoy less acceptance in Germany than in the United Kingdom or France. Moreover, satisfaction with the healthcare system’s performance on the whole could be reduced in Germany. The first expectation gains some confirmation from a closer look at debates on priority setting in Germany (Liesching et al., Reference Liesching, Meyer and Raspe2012), where the application of efficiency criteria is strongly contested and where the FJC and the IQWiG are frequently criticized in public. Moreover, frequent struggles between the FJC and the ministry of health (which may be expected to be more strongly driven by majority opinions) reveal frictions within the system. At the same time, a lack of support for the FJC and its decisions may also be accounted for by a lack of procedural justice in the sense of Daniels and Sabin’s ‘accountability for reasonableness’: the FJC is hardly known to the German public and its reports remain more or less incomprehensible to non-experts. Neither in France nor in the United Kingdom can similar struggles be observed (Littlejohns et al., Reference Littlejohns, Sharma and Jeong2012). In France, the existing moderate incongruences may be concealed by the fact that limit-setting decisions rarely exclude services from funding altogether, but rather increase co-payments for controversial services. As most people in France hold supplementary private insurances for these co-payments, limit setting is hardly noticeable and not a central topic in public debates. In the United Kingdom, NICE seems to enjoy comparatively strong public support – despite the fact that it applies a comparatively strict ICER threshold that would be inacceptable elsewhere. And again, perceived procedural fairness may play a role, as NICE is particularly concerned with fulfilling the criteria of ‘accountability for reasonableness’. Regarding contentment with the healthcare system as a whole, the incongruences between societal values, institutions and decisions found in Germany may be a central cause behind the significantly lower satisfaction with the system: while 75% are satisfied in the United Kingdom and 73% are satisfied in France, only 61% express satisfaction in Germany (ISSP, 2011). This result is particularly remarkable in light of the fact that public health care expenses per capita in Germany are considerably higher than in the United Kingdom or France (OECD, 2014).
If the trend to delegate priority setting decisions to specialized agencies continues, these will become even more dependent on ascribed legitimacy if their decisions are to gain public acceptance. Procedural fairness, as outlined in Daniels and Sabin’s ‘accountability for reasonableness’ framework, is certainly an important precondition in this regard. However, the fact that social values and opinions on appropriate distributive criteria in health care vary across societies also means that different institutions will be appropriate for different countries (similarly: Biron et al., Reference Biron, Rumbold and Faden2012). Only if institutional design, decisions and justifications are congruent with these values and opinions can legitimacy and acceptability be ensured. In our eyes, the only way to ensure such congruence are broad and inclusive democratic debates on institutional design and distributive principles and criteria in health care.
Acknowledgement
The authors thank Katharina Böhm and Cornelia Frings, as well as two anonymous reviewers for HEPL for helpful comments on earlier versions of this paper. Research this paper is based on was funded by the VolkswagenStiftung, Hannover.