Introduction
ENT surgical procedure is often the ‘overlooked sibling’ of medical education.Reference Schuster-Bruce, Davies, Conchie, Penfold, Wilson and Waddell1 It is commonly misunderstood in clinical practice, resulting in poor patient management and inappropriate referrals.Reference Patel, Saeed and Smith2 Despite an evidence-based ENT undergraduate curriculum being published in 2014, it was found that undergraduate curricula varied significantly and continued to omit teaching on fundamental topics.Reference Mayer, Smith and Carrie3 This is even more concerning when considering the high exposure to ENT-related issues across many specialties, including paediatrics, general practice and emergency care. ENT problems are not rare; if they were it would potentially be an excuse for the lack of understanding. Instead, GPs are estimated to encounter ENT diagnoses in 10 per cent of adult and 50 per cent of paediatric appointments.Reference Dimitrov, Unadkat, Khanna, Rennie and Saleh4 Subsequently, a larger emphasis is now being placed on ENT in medical curricula and this is expected to increase with the new pan-university Medical Licensing Assessment.
Medical education, a 100 billion dollar industry,Reference Frenk, Chen, Bhutta, Cohen, Crisp and Evans5 is an ever-changing landscape with constant developments to improve knowledge acquisition, retention and application of complex concepts. Innovative teaching methods aim to introduce fun into the ‘classroom experience’ and increase engagement and variety, breaking the monotony of lectures and small-group learning. However, many of these techniques rely on expensive technological solutions, high start-up costs and costly licensing agreements.
In response, we developed a novel ENT-themed escape room. This aimed to provide fun and effective, but cost-efficient, teaching on ENT topics. Escape rooms are fun, immersive experiences whereby players work together in story-based role-playing games, exploring their ‘inner detective’ to solve puzzles and crack codes that culminate in ‘escaping from a locked room’. Whilst they are commonplace in social activities, there have been only a few instances of their inclusion in medical education.Reference Guckian, Eveson and May6 They have, however, been shown to act as more than a ‘superficial form of entertainment’ and actually be a ‘low-cost, high-impact resource’ for learners.Reference Guckian, Eveson and May6
Materials and Methods
This study was designed as a single-centre pilot feasibility and acceptability evaluation with the intention to assess and identify the potential educational benefit of the ENT-themed escape room. The primary aim was to enhance a medical student’s understanding and retention of ENT concepts in an immersive, interactive environment, demonstrating the ability to improve knowledge acquisition through pre-intervention and post-intervention testing. The secondary aim was to identify whether the use of this learning tool would be an enjoyable experience for students, and whether it would potentially increase future engagement with ENT as a specialty.
Participants were all 4th-year medical students based at Sunderland University Medical School. Twenty-seven students participated across 15 sessions. To maintain consistency, a single gamemaster conducted all escape room sessions. Students were recruited as part of their surgical curriculum at Sunderland Hospital. Participation was voluntary, but no candidate refused the opportunity to partake. Puzzles were designed independently; two practice sessions were conducted with other participants to gather feedback and check that all elements worked. The escape room was designed as a 60-minute experience, with students working in groups of two or three, preceded by the pre-test questionnaire (this included time to set up the experience, which took roughly 10 minutes) and was followed by a 15-minute debrief and post-session feedback.
The room was prepared with a total cost of £78 (4× boxes and 4× padlocks). Attempts to print high-quality microscopic images for use with an otoscope cost a further £18, but these were not used in the final edition due to the inability to print at a high enough dots per inch (DPI) level to produce identifiable pathology and so were replaced by a digital screen. All other items were found within the educational department, including an otoscope, thudicums, tongue depressors, a tuning fork, an old laptop, a USB stick and other various props.
All participants provided informed consent prior to participation. This project was deemed not necessary for ethics approval by both the Research Ethics Committee at South Tyneside and Sunderland NHS Trust and the Sunderland University Research Ethics Group (UREG) under application number 029599. Good Clinical Practice guidelines for research were maintained throughout.
Students were given a pre-intervention and a post-intervention questionnaire, which included a range of questions including 10-point scales, Likert-scales, multiple-choice questions (MCQ) and open-space questions (OSQ), which assessed knowledge levels and perceived confidence in ENT for their finals and for when working as a junior doctor. These questionnaires were designed bespokenly for this study; questions were selected to test the topics covered within the escape room and confirmed by a panel of three ENT surgeons for accuracy. This was paired to allow for comparison pre-intervention and post-intervention. We also collected feedback on the effectiveness, difficulty and enjoyment of the escape room and whether they would recommend this exercise for future educational purposes. Quantitative data were collected; both McNemar test and either paired t-test or Wilcoxon signed-rank test (the latter was applied when the data were not normally distributed) statistical analyses were utilised for descriptive statistics on knowledge acquisition, perceived enjoyment and future engagement. Microsoft Excel (http://www.office.com) and SPSS (v29.0.0.0, https://www.ibm.com/products/spss-statistics) software were used to perform statistical analysis. Qualitative data from open-ended survey responses were thematically analysed to identify recurring themes regarding the educational value and challenges of the escape room.
Results
Completion
Students took a mean time of 59.5 minutes (range 46.5–80 minutes) to complete the escape room. On average, participants requested 3.6 clues (range 1–6 clues) to complete the challenges.
Knowledge
Students were asked three MCQs both before and after the escape room: (1) ‘Which condition classically presents with the appearance of bubbles behind the eardrum and may be treated with a grommet?’ (2) ‘Which of these is an important complication of otitis externa?’ and (3) ‘Which of these classically presents with rotational dizziness lasting only a few seconds?’
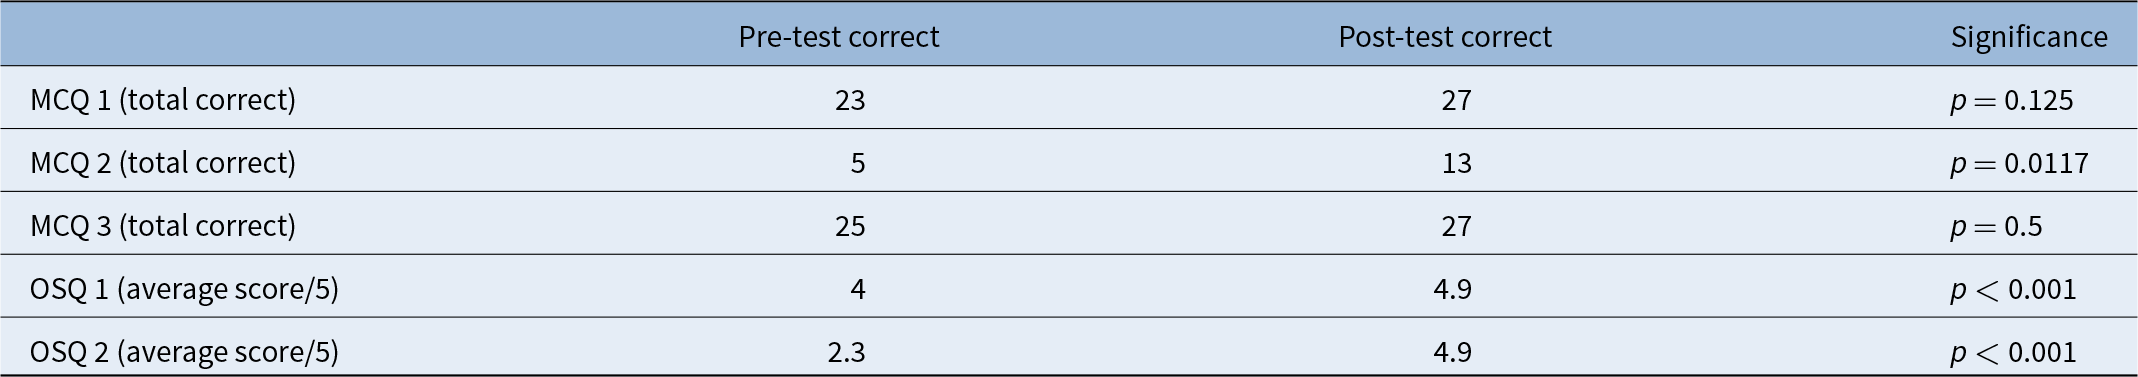
As shown in Table 1, whilst there was an absolute improvement in the post-test assessment for all three questions, statistical significance was achieved only for MCQ2. Similarly, students were asked two OSQs: (1) Please name five red flag symptoms for throat cancer. (2) Please name five causes of septal perforation.
Pre-escape room and post-escape room test results

Table 1 Long description
Correct answers before and after an activity are compared for three multiple-choice items and two open-response items scored out of five. Multiple-choice item 2 increased from 5 correct to 13 correct, and this change is statistically significant with a p value of 0.0117. Multiple-choice item 1 rose from 23 to 27 correct, but the p value of 0.125 indicates the change is not statistically significant. Multiple-choice item 3 increased slightly from 25 to 27 correct, with a p value of 0.5, also not statistically significant. Open-response item 1 improved from an average of 4 to 4.9 out of five, with a p value reported as less than 0.001, indicating a statistically significant increase. Open-response item 2 improved from an average of 2.3 to 4.9 out of five, also with a p value reported as less than 0.001, indicating a statistically significant increase. Overall, the strongest improvements are in the open-response scores and in multiple-choice item 2, while the other multiple-choice items show smaller, non-significant changes. Statistical significance is reported only through p values, and sample size or variability measures are not provided, which limits interpretation of effect size and generalizability.
MCQ = multiple-choice question; OSQ = open-space question.
The number of correct answers was assessed and compared with the number of correct answers post-intervention. There was a statistically significant improvement for both questions, as seen in Table 1.
Confidence and future engagement
The student’s confidence (out of 10) in passing the ENT components of their examinations increased post-test by 2.59 points to 7.07/10 (p < 0.001), and their confidence in ENT overall by 3.04 to 6.3/10 (p < 0.001). Furthermore, participants showed an increased interest in a career in ENT by 1.11 to 5.63/10 (p < 0.001).
Feedback
Students rated the escape room a score of 9.0/10 when asked if they thought it was an effective learning tool, and as 9.7/10 for enjoyment. One student commented ‘[it was] very very fun, and I feel like I know lots more now’, whilst another said, ‘it was great, I really enjoyed it. [It] was the most fun teaching session in surgical procedure’. They gave a score of 9.6/10 when asked how likely they would be to recommend the educational escape room to other students. Overall, every participant gave the experience 5/5 stars.
Game design
To ensure that the ENT-themed escape room was more than just a novelty, significant effort was made to embed essential ENT knowledge and skills into the puzzles and interactive challenges. The key stages to designing the escape room included: Target audience and key testable concepts, puzzle design, storyline, theme and immersion, competition, feedback and reinforcement. These can be replicated to create further escape rooms; examples of these are given below.
Target audience and key testable concepts
The first crucial step in designing the escape room was identifying the target audience and the key concepts to be tested. Before participating in this escape room, due to the limited previous exposure to ENT in their curriculum, students attended a comprehensive ENT-themed lecture and a clinical skills session covering the core conditions required for their medical school finals. From this lecture, the fundamental knowledge components were extracted from the subspecialities of otology, rhinology, laryngology, and head and neck. This allowed consolidation of the key principles, ensuring the activity reinforced key examination-related content.
For example, this included otoscopy, differential diagnoses for vertigo, and head and neck cancer red-flags symptoms. Furthermore, knowledge not previously included in their teaching was also incorporated to see if the escape room would provide an opportunity for acquisition of new knowledge. Students were asked for the causes of septal perforation. This was completed in a ‘fill-in-the-gaps’ spelling game that created an anagram, but with the answers hidden in a reference book describing all conditions. On pre-escape and post-escape room testing, students showed an increase in knowledge on this topic, discovering causes they had not previously known.
Puzzle design
Each puzzle was carefully crafted to integrate the selected knowledge, with consideration taken to incorporate both variety and difficulty. When possible, the requirement for ENT-specific clinical skills was added, ensuring that both theoretical knowledge and practical abilities were tested. To accommodate different teaching environments, all puzzles and props were designed to be portable, effectively making the escape room a ‘pop-up’ event that could be set up and delivered in various locations as required. By balancing knowledge-based puzzles with interactive hands-on tasks, we aimed to engage students with different learning styles and maintain the challenge throughout the session.
It was decided that students would perform best in teams of two or three people, rather than as an individual. Often students had differing areas of knowledge and were able to successfully navigate the tasks together, whereas concern was raised that, as an individual, it would be far too easy to become stuck and frustrated.
Storyline, theme and immersion
To create an immersive and engaging experience for medical students, a carefully constructed backstory was developed. This storyline helped to create a sense of urgency and real-world application. Upon entering the escape room, students were told:
‘You’ve woken up in the hospital mess during a particularly bad on-call shift and, because it has been so busy, you accidentally fell asleep at your desk. Unfortunately, there are still patients to see and tasks to complete before handing over to the consultant on call, who is expected to arrive in approximately 1 hour. You must know, they have a reputation for being unforgiving. You cannot leave until all the jobs are done.’
To create a real sense of exploration and the ability to freely roam the environment, clues and props were distributed around the room. Students were required to search for puzzles that they had enough information to complete. To ensure that all tasks would be completed, and to avoid skipping to later puzzles, four padlocked boxes were introduced that required opening to gather the required information for later tasks. This helped the students to be unknowingly guided through the storyline created (Figure 1). The final task gave them the code that allowed them to complete the game and leave the escape room.
Timeline of escape room.

The first puzzle was hidden inside one of these padlocked boxes. Despite being easy to miss, upon closer inspection of the box, four holes could be seen on the back. When examined with the otoscope, participants were able to identify the diagnoses of otitis externa, otitis media with effusion, cholesteatoma and tympanic membrane perforation. These diagnoses each gave a number in the provided reference book. The corresponding code opened this first box and revealed a pathway to discover further puzzles and challenges. To heighten the immersion, atmospheric details were added including dim lighting, hospital props and finally haunted hospital sounds. Red herrings were strategically placed to further engage the students and maintain suspense.
Competition
Students were informed that their time would be recorded, as with other escape rooms, so that they could assess their performance. However, the scores of other teams were not disclosed, and students were informed of this in advance to help alleviate any worries of embarrassment. To help tailor to different personality types, it was emphasised that this exercise was expected to be a fun learning experience, and we would help them as much or as little as needed.
Encouraging cooperation, teams were informed that great teamwork would generate a time deduction and vice versa. Similarly, asking for clues would generate a time penalty, but the degree of penalty was not shared so that teams would make every attempt to complete the task rather than request a clue if they felt it would save them time overall.
Feedback and reinforcement
Feedback was embedded throughout the escape room. Whilst students were able to complete the room completely independently, a gamemaster was ever present and able to offer clues when requested. Furthermore, if students were seen to becoming frustrated and working in a direction that would bear no fruit, tips or guidance would be offered. It was key that this was a positive learning experience, and careful consideration was taken to assess individual students’ reactions and their preferences to receiving assistance. There was a concern that being allowed to struggle for too long would sour their experience.
Participants also received real-time feedback as a result of the coded boxes. Whether a box was unlocked or not, this offered an immediate positive or negative response and allowed a corrective action if required. Finally, to help reinforce the knowledge learned, upon completion of the escape room, students received a feedback session at which all tasks (including any incorrect answers mentioned by the candidates) were discussed to allow consolidation of the learning that had taken place.
Discussion
The development and implementation of the ENT-themed escape room within the curriculum for medical students demonstrated significant benefits. It enhanced their learning on fundamental ENT topics required to both pass finals and work as a foundational doctor, but also showcased ENT as a specialty resulting in increased engagement and keenness to pursue a career in ENT.
Whilst the escape room revealed significant educational benefits, it is important to consider the variability in the outcomes of the knowledge assessments. The MCQs, whilst showing absolute improvement in post-test results, only MCQ 2 showed a statistically significant rise in correct answers (MCQ 1: p = 0.125, MCQ 2: p = 0.0117, MCQ 3: p = 0.5). This lack of significance for MCQ 1 and MCQ 2 may be attributed to the fairly small sample size. Furthermore, it may be attributed to the relatively simple nature of the question. A large percentage scored correctly on these, even in the pre-test, and unfortunately some students who had answered correctly on the pre-test then answered incorrectly during the post-test (perhaps they had guessed both times or maybe the amount of information confused them). In contrast, the use of open-ended questions that required students to list answers to key concepts, such as red flag symptoms for throat cancer and causes of septal perforation, produced statistically significant improvements (OSQ 1: p < 0.001, OSQ 2: p < 0.001). The white-space nature of the question may have reduced the ability to correctly guess in the pre-test questionnaire. This highlights the success of the escape room in teaching students complex information and their subsequent ability to recall it, proving its potential as an educational tool in promoting knowledge acquisition. This will require further validation on larger cohorts.
Our findings align loosely with some principles of constructivism, when learners actively construct knowledge through experience and reflection. The escape room provided an immersive environment that required students to apply clinical skills and core knowledge to solve, at times, very complex puzzles. Learners build on their existing knowledge through engaging with the content, social interaction and teamwork to complete the challenges. As described by Reg Dennick, constructivism relies on the use of ‘hypothetico-deductive’ processes.Reference Dennick7 In the escape room, students test hypotheses and receive immediate feedback (whether the box opens or not) to show whether this hypothesis can be supported or rejected. Furthermore, simulated immersive experiences such as these provide a safe environment for students to exercise their diagnostic skills, a fundamental cognitive skill for doctors, with the only consequence being the delay in completing the game. Admittedly, due to the competitive nature of most medical students, this was quite significant for them.
Additionally, the collaborative nature of the escape room reflects social constructivism, emphasising the benefits of social interaction in learning. Through partnership, students can learn from, and also teach, each other. Working in pairs or small teams, students communicated, negotiated and educated each other, which enhanced their learning experience. To exemplify this, one student who had a good grasp of tuning fork assessments let their colleague have a first attempt to decipher the code but, when this failed, they were then able to help and explain their reasoning. Furthermore, when a student particularly underconfident at otoscopy immediately offered this task over to their colleague, stating ‘I can’t do this’. Another replied ‘Well now is a good time to practice, let me help you’.
Whilst applying principles of constructivism, the escape room is still a defined, structured learning experience, rather than true exploratory learning. The escape room relied on the design of the puzzles and available resources to provide the answers and guide students step-by-step through each challenge, instructed, when necessary, by the gamemaster. They also received the positive and negative feedback for correctly opening boxes. These instructional elements, that is learning through direction, are heavily laden with cognitivist theory.
An important part of the escape room is the incorporation of elements of gamification (such as challenge, competition and reward). It is still under discussion to what extent gamification helps with education, with critiques stating that it simply captures attention and encourages participation,Reference Kapp8 yet others argue that it also helps to improve retention and recall, and fosters collaborative learning.Reference Rooney and Whitton9, Reference Sailer, Hense, Mayr and Mandl10 One of the biggest arguments against gamification is the potential for superficial engagement and the potential for distraction from core learning objectives and outcomes by the completion of tasks and point-gaining. If the integration is not authentic and meaningful, then the activities may not promote genuine learning outcomes, but rather distract from purposeful knowledge development.Reference Faiella and Ricciardi11
As a result of this, to alleviate the pressures experienced by some students, it is important that gamification is used in a system that can be customised so that all students can benefit.Reference Faiella and Ricciardi11 During the experience, a gamemaster was always present to oversee the students during the escape room, therefore being present to offer tips and clues when necessary. It was observed that students acted extremely differently in these situations. Some really thrived under the pressure, whereas others appeared to struggle to function with the competitive element, which is relatable to the effect of high arousal/stress on performance described in the Hebbian version of the Yerkes–Dodson law.Reference Diamond, Campbell, Park, Halonen and Zoladz12 Whilst those thriving refused all offers of help, others found significant relief from this. When these behaviours were observed, emphasis was made on reminding students that the objective was fun and learning, and not to worry about the competitive element. Anecdotally, this appeared to alleviate student concerns and help maximise the learning opportunities for each student.
Participant feedback on gamified learning is often overlooked, that is explaining the mistakes they made, but it is theorised that, in these scenarios, early and meaningful feedback is extremely important.Reference Domínguez, Saenz-de-Navarrete, de-Marcos, Fernández-Sanz, Pagés and Martínez13 Following the completion of the escape room, all puzzles and challenges were discussed. It should be noted that compulsory use of gamified learning tools for students can negatively impact participation and so students should be offered the choice of engaging, which may help increase motivation and efficacy.Reference Faiella and Ricciardi11 Currently, there is no consensus on how and when to use gamification; more research is necessary to highlight where its uses are best placed. There is a risk that the novelty and fun could distract from the potential negative effects, especially if not used appropriately.
Importantly, challenges were encountered during the delivery of the escape room. Whilst created to be cost-effective and portable, it was a significant time investment to design and implement. This factor may limit the ability to scale and reproduce it. Commonly, students asked how long it had taken to prepare and described their gratefulness for it. They explained that the obvious effort made them feel valued and increased their positive feelings towards the experience. Despite the positive outcomes, there were also limitations to the sample size, which may have affected the generalisability of the results. The level of difficulty of this escape room would allow it to be appropriately used for foundational doctors, but future iterations could be designed at increasing complexity and used for post-graduate trainees or consultants.
Overall, this immersive experience was a fun learning tool that increased student engagement and demonstrated the ability to increase knowledge acquisition and consolidation. It provided valuable insight into the effectiveness of experiential learning methods in medical education.
Summary
What is already known on the subject
• ENT is commonly under-represented in the undergraduate medical curriculum.
• Cross-specialty relevance with ENT-related issues is seen in Paediatrics, General Practice and Emergency Care.
• Escape rooms are building in popularity as a social activity and have increasing representation in medical education.
What this paper adds to our understanding
• This ENT-themed escape room enhanced student knowledge and confidence in diagnosing and managing ENT conditions.
• Escape rooms can be used as a low-cost innovative teaching tool, helping to promote engagement in surgical education.
Conclusion
The ENT-themed escape room proved to be an effective, enjoyable and innovative educational tool that demonstrated the ability to enhance knowledge acquisition and confidence, and increased interest in ENT as a career choice. It complemented current traditional teaching methods and remained low-cost. Further validation is required before immersive escape room experiences such as this become a mainstream tool in education.
Supplementary material
The supplementary material for this article can be found at https://doi.org/10.1017/S0022215126105908.
Data availability statement
The raw data collected are available in the supplementary material.
Funding
None.
Competing interests
None.
Ethics approval and consent to participate
This project was deemed not necessary for ethics approval by both the Research Ethics Committee at South Tyneside and Sunderland NHS Trust and the Sunderland UREG under application number 029599. All participants provided informed consent prior to participation and were able to withdraw at any time.
Acknowledgements
None.
Authors’ contributions
All authors contributed to the design and conception of the study. SR wrote the initial manuscript and designed the initial concept. HW, TT and HC provided assistance with concept design for the escape room. All authors reviewed the draft and final editions of the manuscript.
Consent for publication
Not applicable.