Introduction
Vestibular neuronitis has been estimated to occur in 3.5 cases per 100 000 persons.Reference Sekitani, Imate, Noguchi and Inokuma1 At clinics that specialise in vestibular disorders and vertigo, this accounts for between 3 and 10 per cent of cases.Reference Neuhauser2 Clinically, vestibular neuronitis is characterised by the acute onset of severe vertigo and nausea, without hearing loss. This can last for days to weeks, but generally improves over the course of weeks to three months. It is associated with unilateral vestibular hypofunction; however, the exact aetiology of vestibular neuronitis is not yet fully understood. Although certain authors have postulated that an ischaemic process might underlie the aetiology of vestibular neuronitis, there is strong evidence to suggest that a virus is the causative agent.Reference Hemenway and Lindsay3–Reference Baloh, Ishyama, Wackym and Honrubia8 Anecdotally, many (but not all) patients may complain of a viral prodrome (with or without mild dizziness) before experiencing the severe vertigo.
As the incidence of viral infections changes throughout the year, variations in the incidence of vestibular neuronitis may indirectly support a viral aetiology. With this in mind, we undertook a retrospective chart review of patients with vestibular neuronitis seen over a three-year period.
Materials and methods
A chart review was performed following the approval of the Virginia Commonwealth University institutional review board. Between 1 May 2008 and 31 April 2011, 52 cases of vestibular neuronitis were diagnosed by the otolaryngology department (using the International Classification of Diseases, Ninth Revision, Clinical Modification code 386.12). The diagnosis of vestibular neuronitis was made clinically, based on a history of a single acute attack of vertigo without hearing loss that lasted days and improved over the course of weeks.
The information recorded for the review included: patient age and gender, date of onset, date of evaluation, presence of preceding upper respiratory infection or other viral prodrome, physical examination findings, audiogram results, symptoms at follow up, and medical comorbidities. The exclusion criteria were: patient age of less than 18 years, new onset hearing loss, recent trauma, asymmetrical hearing loss, other focal neurological signs, prior surgery on the affected ear, lack of expected improvement after the initial episode, a history of fluctuating hearing loss, prior vertigo, chemotherapy, radiation, exposure to other known ototoxins or failure to attend follow up.
Confirmatory testing of vestibulopathy was not performed in most cases; patients often presented after the initial episode had improved to some degree, and confirmatory testing has been shown to be unnecessary for the adequate diagnosis of vestibular neuronitis.Reference Goddard and Fayad9, Reference Baloh10 Fifty-two cases of vestibular neuronitis were identified during the study period and relevant data were extracted.
Monthly and quarterly incidence values were calculated for the three-year study period. Incidence values were then compiled for each 12-month period, and a chi-square test was performed to assess for uneven distribution within each year of the study. In addition, the monthly and quarterly incidence values were aggregated across all three years of the study (e.g. the incidence values for April 2009, April 2010 and April 2011 were summed) and assessed for uneven distribution using the chi-square test. To supplement the chi-square test, data were analysed using the Rayleigh test for circular means.
Results
The study population was 33 per cent male and 67 per cent female. The average age of patients was 55 years. Ninety-four per cent of patients (49 out of 52) had significant or complete resolution of symptoms at follow up. The patients were seen on average 58 days following the onset of their symptoms. Only 15 per cent of patients reported symptoms of an upper respiratory infection in the weeks prior to the onset of vertigo.
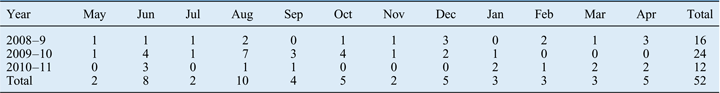
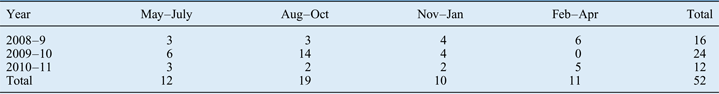
In terms of monthly differences in vestibular neuronitis incidence across the three-year study period, the chi-square test result was not statistically significant (chi-square = 4.31, 2 degrees of freedom, p = 0.116) (Table I). When quarterly differences in incidence were examined, the chi-square test revealed no statistically significant findings for two of the three study years. (For 2008–2009: chi-square = 1.49, 3 degrees of freedom, p = 0.684. For 2010–2011: chi-square = 1.97, 3 degrees of freedom, p = 0.578.) However, the quarterly difference was significant for the 2009–2010 study year (chi-square = 17.25, 3 degrees of freedom, p = 0.001), with larger than expected numbers of cases in the second quarter (August–October) (Table II). When the data for all three study years were aggregated, the chi-square test revealed no significant differences in terms of the quarterly incidence of vestibular neuronitis (chi-square = 3.85, 3 degrees of freedom, p = 0.279).
Monthly incidence of vestibular neuronitis

Quarterly incidence of vestibular neuronitis
When the Rayleigh test for circular means was applied to the individual years, the result was significant for the 2009–2010 study year (R = 10.281, p < 0.001), but failed to reach significance for the other two study years. (For 2008–2009: R = 0.771, p = 0.470. For 2010–2011: R = 1.028, p = 0.366.) When the data for all three study years were aggregated, the test failed to reach statistical significance (R = 1.613, p = 0.199). These results are consistent with those of the chi-square test.
Due to limited patient numbers, a subset analysis of the eight patients with pre-vestibular neuronitis viral prodrome could not be performed. There was no apparent trend towards seasonality amongst this group.
Discussion
Although never studied in vestibular neuronitis, several papers have addressed seasonal changes in incidence for other potentially virally-induced or virally-activated inner-ear disorders. As early as 1983, Wilson et al. reported higher rates of seroconversion to mumps, rubeola, varicella-zoster, cytomegalovirus and influenza B in patients with idiopathic sudden sensorineural hearing loss (SNHL) compared with controls, with a disproportionate number occurring in the Spring.Reference Wilson, Veltri, Laird and Sprinkle11 Wu et al. identified 9267 patients with idiopathic sudden SNHL when reviewing national health insurance data; from these data, the authors identified a statistically significant trend (p < 0.001) for higher rates of idiopathic sudden SNHL occurring in August to October (autumn in Taiwan).Reference Wu, Lin and Chao12 (It should be noted that idiopathic sudden SNHL was not defined in that study.) In another study from Taiwan, Chang et al. retrospectively analysed 146 patients hospitalised for idiopathic sudden SNHL, and found significant peaks in incidence in April (15 per cent) and October (12 per cent).Reference Chang, Ho and Kuo13
In contrast to the aforementioned studies, Danielides et al. found no significant differences in seasonal incidence (at a 95 per cent confidence level) in a retrospective review of 82 patients with idiopathic sudden SNHL over a four-year period at a single institution.Reference Danielides, Nousia, Bartzokas, Lolis, Kateri and Skevas14 More recently, Jourdy et al. reviewed the charts of 97 patients with idiopathic sudden SNHL and found no uneven distribution throughout the year.Reference Jourdy, Donatelli, Victor and Selesnick15 Furthermore, a subset analysis of those patients who complained of symptoms characteristic of upper respiratory infection prior to hearing loss revealed no evidence of seasonal variability. Studies of weather conditions and incidence of idiopathic sudden SNHL have been similarly inconclusive.Reference Preyer16–Reference Herbert, Nolte and Eichhorn19
Several studies support a viral aetiology of vestibular neuronitis; however, the evidence remains circumstantial. In 1952, Dix and Hallpike suggested a possible infectious process involving Scarpa's ganglion or the vestibular nerve itself.Reference Dix and Hallpike20 Yet, since then, no studies have proven that direct viral infection of the vestibular apparatus can cause acute vestibular neuronitis in humans. Although vestibular ganglia can be virally infected in murine models, with demonstrated vestibular hypofunction, these studies are limited by high animal mortality and difficulty in determining specific cellular triggers in response to infection.Reference Hirata, Sugita, Gyo and Yanagirhara21–Reference Okazaki and Sekitani23
The vast majority of relevant studies have focused on the reactivation of latent viruses, particularly on (the neurotrophic virus) herpes simplex virus type 1. Furuta et al. studied 26 autopsied human vestibular ganglia and found herpes simplex virus type 1 DNA in 6 of 10 ganglia analysed by polymerase chain reaction.Reference Furuta, Takasu, Fukuda, Inayuma, Sato and Nagashima4 A subsequent study by Theil et al. (2001) was able to detect latency-associated transcripts, suggesting that herpes simplex virus type 1 became reactivated after a period of latency.Reference Theil, Arbusow, Derfuss, Strupp, Pfeiffer and Mascolo7 More recently, Roehm et al. were able to show reactivation of latent herpes simplex virus type 1 in a cell culture model.Reference Roehm, Camarena, Nayak, Gardner, Wilson and Mohr24 Together, these studies indicate that herpes simplex virus is present in the vestibular ganglion and can lead to latent infection, thus supporting infection reactivation as a possible cause of vestibular neuronitis.
Irrespective of whether vestibular neuronitis is caused by direct viral infection of the vestibular apparatus or indirect infection via reactivation of latent viral DNA, the data from this study do not support monthly or seasonal variations in incidence. Although slight variation in the 2009–2010 study year were suggestive of seasonal changes, the other two study years showed no variation, and there was no evidence of variation when the three study years were aggregated. These findings are consistent with the better designed studies of seasonal incidence of idiopathic sudden SNHL.
Unlike idiopathic sudden SNHL, firm diagnostic criteria have yet to be established for vestibular neuronitis. As with most peripheral vestibular disorders, vestibular neuronitis should be diagnosed on the basis of a thorough patient history and physical examination. Central causes of vertigo must be ruled out, and brain imaging should be performed if there are any complaints of: altered sensation (e.g. numbness, pain and temperature), slurred speech, extremity weakness, vision changes, ataxia, memory loss and so on. In the early stages of vestibular neuronitis, patients may exhibit nystagmus (rotatory and/or horizontal) with the fast phase towards the uninvolved ear.
Due to the tertiary referral nature of our otology practice, the majority of patients in this study were seen long after the nystagmus would be expected to have been resolved. Several patients did report the sensation of ‘my eyes moving in my head’ during their acute vertigo. Head-thrust testing wherein the patient veers towards the affected ear can demonstrate catch-up saccades supportive of a peripheral vestibulopathy, but is not pathognomonic for vestibular neuronitis. In our clinic, a positive head-thrust test result was supportive of vestibular neuronitis, but a negative head-thrust result does not exclude vestibular neuronitis.
Formal vestibular testing has been used in research settings and may demonstrate reduced caloric responses, but in practice (as was true for most of the patients in this study) they are often not performed as the patients are clinically improving by that stage; the diagnosis of vestibular neuronitis is instead based on a strong suspicion. Imaging does not play a role in the diagnosis of vestibular neuronitis, and only serves to rule out other processes. Most patients in this study did not undergo imaging; although it would be atypical for retrocochlear pathology to present in a clinically similar manner to vestibular neuronitis, it is conceivable that some patients may have had alternative diagnoses.
• The pathophysiology of vestibular neuronitis is not fully understood
• It is diagnosed clinically, on the basis of patient history and a physical examination
• Some evidence suggests that vestibular neuronitis may be virally mediated
• Several studies of other inner-ear conditions have demonstrated seasonal changes in incidence, supporting a possible viral association
• No significant associations were found in this study between months or seasons of the year and vestibular neuronitis incidence
Another limitation of this study was the number of patients; it is possible that greater patient numbers may have revealed significant changes in the incidence of vestibular neuronitis throughout the year. Certainly, with more patients, multivariate analysis could be performed to determine associations between age, gender and comorbidities with respect to monthly variations in incidence.
As the symptoms of vestibular neuronitis naturally improve with time, many patients with vestibular neuronitis may not feel the need to have an initial evaluation by a neurotologist. Therefore, if seasonality affects a patient's willingness to be seen by a neurotologist (i.e. more inclined to see the doctor in winter, or less inclined to see the doctor in summer), selection bias could conceivably play a role.
Until viral cultures or serologic analyses are able to definitively prove a causal relationship between viral infection and vestibular neuronitis, associative epidemiologic studies (similar to this study) can aid our understanding of vestibular neuronitis pathophysiology and elucidate the aetiology of other conditions.
Conclusion
The current study found no significant annual or seasonal variation in the incidence of vestibular neuronitis over the three-year study period. However, when the study years were analysed individually, evidence of seasonal variation was found for the 2009–2010 period. Nevertheless, analysis of individual years should be viewed with caution given the small number of cases that arose within a single year, as well as the number of months within a year in which no cases were reported. Further study is warranted in light of the small sample size; evidence of seasonality would lend further support to a viral aetiology of this disease process.
Acknowledgement
Dr Thacker's efforts were financially supported in part by the National Institutes of Health (grant number UL1RR031990).