Atrioventricular septal defect, also known as endocardial cushion defect, common atrioventricular canal, or complete atrioventricular canal, is a serious cardiac anomaly with a central defect involving both the ventricular and atrial septum and a common atrioventricular valve across the defect. The defect may be partial or total and include the dominance of one ventricle – an unbalanced atrioventricular septal defect – and may have associated cardiac anomalies resulting in severe heart failure in early infancy.Reference Anderson, Baker, Macartney, Rigby, Shinebourne and Tynan 1 Surgery can be performed within the first year of life with good results, but later corrective surgery of one or both atrioventricular valves may be necessary. Studies show variations in survival ranging from 65% to 84.1% 20 years post surgery.Reference Dragulescu, Fouilloux, Ghez, Fraisse, Kreitmann and Metras 2 – Reference Tennant, Pearce, Bythell and Rankin 4 However, none of these studies included unbalanced atrioventricular septal defects for which survival is known to be worse.Reference Owens, Gomez-Fifer, Gelehrter and Owens 5
Atrioventricular septal defect is often seen in infants with Down syndrome and other karyotype anomalies.Reference Torfs and Christianson 6 However, studies report a large variation in the proportion of cases with atrioventricular septal defect and an associated karyotype anomaly.Reference Torfs and Christianson 6 , Reference Huggon, Cook, Smeeton, Magee and Sharland 7 A large population-based study from California showed that 54% of infants with atrioventricular septal defect had Down syndrome, whereas a study by Huggon et al found 35.5%.Reference Torfs and Christianson 6 , Reference Huggon, Cook, Smeeton, Magee and Sharland 7
Few studies have reported the epidemiology of atrioventricular septal defect, and of those that do only a very few have been population based.Reference Torfs and Christianson 6 , Reference Huggon, Cook, Smeeton, Magee and Sharland 7
Atrioventricular septal defect is most commonly diagnosed prenatally within the second trimester, although some cases may be diagnosed earlier.Reference Rasiah, Ewer, Miller, Wright, Tonks and Kilby 8 , Reference Berg, Kaiser and Bender 9 After the prenatal diagnosis of atrioventricular septal defect, health professionals may inform the parents of the risk of Down syndrome and other anomalies, and may offer prenatal karyotype testing. Accurate data on the epidemiology and survival of atrioventricular septal defect will be very useful in the counselling of parents when a prenatal diagnosis of atrioventricular septal defect is made.
The aim of this study is to describe the epidemiology of atrioventricular septal defect, particularly the prevalence of chromosomal and non-chromosomal atrioventricular septal defect.
Materials and methods
Data analysed in this study were obtained from EUROCAT, a European network of population-based registries collecting data on congenital anomalies. EUROCAT obtains information on foetuses and infants born with major congenital and chromosomal anomalies. Minor anomalies are disregarded according to the EUROCAT list of exclusions (http://www.eurocat-network.eu/aboutus/datacollection/guidelinesforregistration/malformationcodingguides). Information is obtained from hospital records, post-mortem examinations, and birth and death certificates. EUROCAT covers more than 1.5 million births per year from 43 registries in 20 countries (www.eurocat-network.eu).Reference Greenlees, Neville and Addor 10 , Reference Boyd, Haeusler, Barisic, Loane, Garne and Dolk 11 For this study, all full member EUROCAT registries were invited to participate. Data from 13 registries covering 993 cases of atrioventricular septal defect (International Classification of Diseases-9 and -10 codes 7456 or Q21.2) from 2000 to 2008 were included. Not all registries covered the entire study period. Cases were classified into four different groups using a computer algorithm.Reference Garne, Dolk and Loane 12 Each case was classified according to associated non-cardiac anomalies and allocated in groups of either isolated cardiac anomaly, chromosomal anomalies, monogenic syndrome, or potentially multiple anomaly. The potentially multiple anomaly cases were manually reviewed by three of the authors – Ester Garne, Diana Wellesley, and Nikolas Christensen. Multiple congenital anomaly was defined as a minimum of two major congenital anomalies in two different organ systems. During the manual review, cases were allocated to a new subgroup: heterotaxia sequence. Heterotaxia sequence was defined as two or more of the following anomalies: asplenia/polysplenia, bilaterally bi- or trilobed lungs, situs inversus, midline liver, right-sided stomach, intestinal malrotation, dextrocardia, or atrial isomerism.Reference Anderson, Baker, Macartney, Rigby, Shinebourne and Tynan 1 , Reference Peeters and Devriendt 13 – Reference Maclean and Dunwoodie 15 If other organs were involved, the case was classified as multiple congenital anomaly.
All cardiac defects were reviewed manually (Helle Andersen and Nikolas Christensen), and cases not compatible with atrioventricular septal defect were excluded. The diagnosis of atrioventricular septal defect was subdivided into either isolated complete atrioventricular septal defect, isolated primum atrial septal defect, atrioventricular septal defect with associated cardiac defects, or unbalanced atrioventricular septal defect. Cases with the text partial or incomplete atrioventricular septal defect were categorised as primum atrial septal defect. Unbalanced atrioventricular septal defect includes cases with a hypoplastic ventricle or hypoplastic left/right heart syndrome.
Prevalence and epidemiological data – type of birth, birth weight, gestational age at prenatal discovery, 1-year survival, and maternal age – will be given for each group.
Descriptive analyses were performed and Chi-square test was used for statistical testing. The level of significance was set at 0.05.
The total number of births covered in the 13 registries was 1,865,403.
Results
During the 9-year study period, a total of 993 cases of atrioventricular septal defect were diagnosed, with a total prevalence of 5.3 per 10,000 births (95% confidence interval 4.1 to 6.5). Live births accounted for 639 cases (64%). Stillbirths were present in 45 cases (5%). In 309 cases (31%), there was a termination of pregnancy owing to foetal anomaly, accounting for 54% of those prenatally diagnosed.
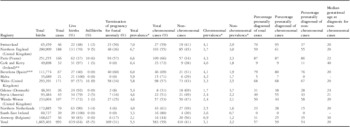
Table 1 shows the prevalence of atrioventricular septal defect in the 13 registries. The total prevalence of atrioventricular septal defect varied from 2.1 per 10,000 births in Antwerp, Belgium, to 7.0 in Switzerland. There was a significant difference between registries in the proportions of chromosomal and non-chromosomal cases (p-value < 0.001). The proportion of chromosomal cases ranged from 31% in Denmark to 80% in South-East Ireland. In all regions except Antwerp in Belgium and Odense in Denmark, there were more chromosomal atrioventricular septal defect cases than non-chromosomal atrioventricular septal defect cases.
Birth type and prevalence of the different European regions during 2000–2008.

*Listed per 10,000 births
**Included the years 2000–2005
***Included the years 2000–2007
Significant differences in the distribution between live births, stillbirths, and termination of pregnancy owing to foetal anomaly were found among registries (p-value < 0.001). The highest proportions of live births were found in Malta, South-East Ireland, Cork and Kerry, Northern Netherlands, and Denmark (≥90%). Termination of pregnancy owing to foetal anomaly ranged from 0% in South-East Ireland, Cork and Kerry, Ireland, and Malta to 57% and 60% in Paris, France, and Barcelona, Spain, respectively. The rate of termination of pregnancy owing to foetal anomaly varied between regions from 0% to 50% for chromosomal cases versus 0% to 41% for non-chromosomal cases.
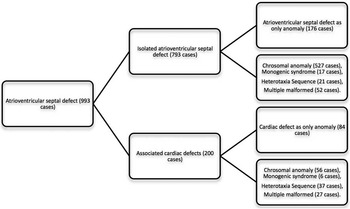
More than half of all cases were diagnosed with a chromosomal anomaly (583 cases or 59% of total), of which 488 cases had trisomy 21. Other karyotype anomalies included trisomy 18, trisomy 13, Turner syndrome, Klinefelter syndrome, various deletions, and unbalanced translocations. Isolated cardiac defects were seen in 250 cases (25%). Multiple anomalies and heterotaxia sequence were present in 79 (8%) and 58 cases (6%), respectively. There were 23 cases (2% of total) with a monogenic syndrome. The prevalence for these groups ranged from 0.1 to 3.1 per 10,000 live births, that is, monogenic syndrome and chromosomal cases, respectively. The distribution of all cases in individual groups is summarised in Figure 1. Figure 1 may be a helpful tool when counselling a pregnant woman with a foetus that is prenatally diagnosed with an atrioventricular septal defect.
Flowchart showing the distribution of cases with atrioventricular septal defect according to associated cardiac defects. For use in counselling pregnant women with a prenatally diagnosed foetus with atrioventricular septal defect.

For cases with chromosomal anomalies, 58% of cases were live births, for cases with multiple anomalies 53% were live births, and for cases with isolated atrioventricular septal defect and no other cardiac defects 90% were live births.
Of all cases, 57% were diagnosed prenatally. A large variation was seen between groups. Of cases of isolated atrioventricular septal defect, 41% were prenatally diagnosed compared with 83% of cases with Heterotaxia and 76% of cases with multiple anomalies. For postnatally diagnosed cases, the majority were diagnosed within the first month after birth.
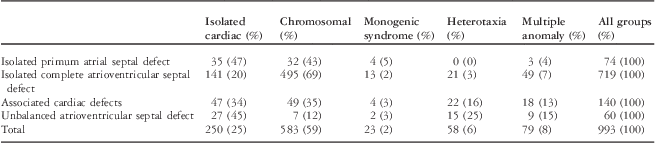
The distributions of the different types of atrioventricular septal defects are given in Table 2. For cases with isolated primum atrial septal defect, most were either an isolated cardiac lesion (47%), with no other major non-cardiac defects, or had a chromosomal anomaly (43%). No cases with isolated primum atrial septal defect had heterotaxia.
Distribution of cardiac defects among groups.

Isolated complete atrioventricular septal defect was the most frequent cardiac setting seen in 72% of total cases. Among these, 69% of the cases had a chromosomal anomaly and 20% of the isolated complete atrioventricular septal defect had no other cardiac or non-cardiac anomalies – isolated cardiac lesion.
Of cases with associated cardiac defects, 34% were isolated cardiac defects and 35% had chromosomal anomalies. Heterotaxia was present in 16% and 13% had multiple anomalies.
The median gestational age at prenatal diagnosis was 21 weeks for isolated primum atrial septal defect and isolated complete atrioventricular septal defect and 20 weeks for cases with associated cardiac defects and unbalanced atrioventricular septal defect.
Table 3 shows the distribution of associated cardiac defects. Coarctation of the aorta was the most frequent and was present in 48 cases, that is, 21% of the total associated cardiac defects.
Associated cardiac defects seen among 140 cases.

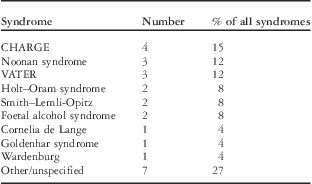
Table 4 shows the 26 syndromes and associations present with atrioventricular septal defect cases. The most common were the CHARGE syndrome, Noonan syndrome, and VATER association.
Syndromes and associations among cases with atrioventricular septal defects.

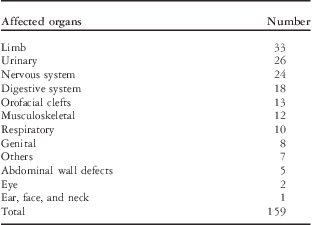
Table 5 shows the anomalies seen among the 79 cases with multiple malformations. The most common were limb, urinary, and nervous system anomalies accounting for 33 (21%), 26 (16%), and 24 (15%)of a total of 159 anomalies, respectively.
Additional congenital anomalies in cases with atrioventricular septal defects.

Of all 993 cases, 599 (60%) survived beyond the first week of life. For live births only, the percentage of survival at 1 week of age was 94% and survival past 1 week varied between groups from 82% (Heterotaxia) to 96% (Isolated cardiac) for live births. For six cases, the outcome at 1 week of age was unknown.
Discussion
Our European study showed an overall prevalence of atrioventricular septal defect of 5.3 per 10,000 births (95% confidence interval 4.1 to 6.5), which is higher than in previously published literature. The reported prevalence ranges from 2 per 10,000 to 4.4 per 10,000 live births.Reference Torfs and Christianson 6 , Reference Rasiah, Ewer, Miller, Wright, Tonks and Kilby 8 , Reference Calabrò and Limongelli 16 , Reference Miller, Siffel, Lu, Riehle-Colarusso, Frías and Correa 17 However, these studies included live-born cases only and only one study included the entire spectrum of atrioventricular septal defect.Reference Miller, Siffel, Lu, Riehle-Colarusso, Frías and Correa 17 The variation in prevalence is also demonstrated by the regional differences observed in our study. There was no clear North-South or East-West European distribution of prevalence present in our study.
In our European population, 64% of all atrioventricular septal defect cases were live births and 31% resulted in a termination of pregnancy for foetal anomaly. In other studies, the proportions of birth types are reported with some variation. Studies on prenatally diagnosed atrioventricular septal defects mostly show a lower proportion of live births than found in this study.Reference Huggon, Cook, Smeeton, Magee and Sharland 7 – Reference Berg, Kaiser and Bender 9 , Reference Machado, Crawford, Anderson and Allan 18 – Reference Fesslova, Villa, Nava, Boschetto, Redaelli and Mannarino 20 Delisle et alReference Delisle, Sandor, Tessier and Farquharson 21 and AllanReference Allan 22 included postnatally diagnosed cases, and the proportion of live births in these studies correlates well with our findings.
The highest proportion of termination of pregnancy for foetal anomaly cases in our study was seen in cases with multiple anomalies, chromosomal anomalies, and heterotaxia. Yıldırım et al did not find any significant increase in termination of pregnancy for foetal anomaly among cases with more complex cardiac lesions compared with those with isolated cardiac defects.Reference Yıldırım, Gungorduk and Yazıcıoğlu 19 Culture, prenatal screening policies, and local legislation in relation to termination of pregnancy for foetal anomaly may influence this proportion.Reference Boyd, DeVigan, Khoshnood, Loane, Garne and Dolk 23
Regional variation in chromosomal prevalence was seen in our study (Table 1). In regions with first-trimester screening for Down syndrome, the gestational age at termination of pregnancy for foetal anomaly might be too low for the diagnosis of atrioventricular septal defect either by ultrasound or by post-mortem examination. In the Danish registry, only 31% of all atrioventricular septal defect cases were reported to have a chromosomal anomaly. In this region, chorion villus sampling was the preferred invasive test offered for Down syndrome screening at a gestational age of 12–13 weeks to women from 35 years in the period 2000–2004, and from 2005 the first trimester combined screening was offered to all women.Reference Frøslev-Friis, Hjort-Pedersen, Henriques, Krogh and Garne 24 With the increasing use of first-trimester screening for Down syndrome in Europe, the overall prevalence and the chromosomal prevalence of diagnosed atrioventricular septal defect is expected to decrease.
In this study, chromosomal anomalies accounted for the majority of cases and Down syndrome was, as expected, the dominant chromosomal anomaly.Reference Huggon, Cook, Smeeton, Magee and Sharland 7 – Reference Berg, Kaiser and Bender 9 , Reference Machado, Crawford, Anderson and Allan 18 – Reference Delisle, Sandor, Tessier and Farquharson 21 , Reference Carmi, Boughman and Ferencz 25 , Reference Paladini, Volpe and Sglavo 26 Cases with isolated cardiac defects comprised a quarter of the total cases. This corresponds well with other studies.Reference Delisle, Sandor, Tessier and Farquharson 21 , Reference Carmi, Boughman and Ferencz 25 However, studies including only prenatally diagnosed cases are likely to be over-represented with more complex cases.Reference Huggon, Cook, Smeeton, Magee and Sharland 7 , Reference Machado, Crawford, Anderson and Allan 18 , Reference Allan 22
The proportion of heterotaxia sequence has been reported with large variation ranging from 6% to 45%.Reference Owens, Gomez-Fifer, Gelehrter and Owens 5 , Reference Rasiah, Ewer, Miller, Wright, Tonks and Kilby 8 , Reference Berg, Kaiser and Bender 9 , Reference Geva, Ayres, Pignatelli and Gajarski 14 , Reference Miller, Siffel, Lu, Riehle-Colarusso, Frías and Correa 17 , Reference Fesslova, Villa, Nava, Boschetto, Redaelli and Mannarino 20 – Reference Allan 22 , Reference Carmi, Boughman and Ferencz 25 In our study, we found heterotaxia in 6% of the cases. The proportion and type of monogenic syndromes in our study are similar to previously published studies.Reference Carmi, Boughman and Ferencz 25 , Reference Digilio, Marino, Toscano, Giannotti and Dallapiccola 27
Isolated primum atrial septal defect was the cardiac lesion in 74 cases (7% of total cases). This figure may be underestimated in our study, as isolated primum atrial septal defect is more difficult to diagnose and therefore might not be diagnosed within the first year of life.Reference Geva, Ayres, Pignatelli and Gajarski 14 , Reference Paladini, Volpe and Sglavo 26 , Reference Bini 28 Isolated primum atrial septal defect was mainly seen in patients with isolated cardiac lesions (47%) or chromosomal anomalies (43%), as has also been reported by Paladini et alReference Paladini, Volpe and Sglavo 26 No cases with isolated primum atrial septal defect had heterotaxia sequence in our study. Geva et alReference Geva, Ayres, Pignatelli and Gajarski 14 have noted that heterotaxia is more common in cases with complete atrioventricular septal defect than primum atrial septal defect.
Our study shows a strong association between isolated complete atrioventricular septal defect and chromosomal anomalies. This association is well known, especially the association with Down syndrome.Reference Huggon, Cook, Smeeton, Magee and Sharland 7 – Reference Berg, Kaiser and Bender 9 , Reference Calabrò and Limongelli 16 , Reference Machado, Crawford, Anderson and Allan 18 , Reference Fesslova, Villa, Nava, Boschetto, Redaelli and Mannarino 20 , Reference Delisle, Sandor, Tessier and Farquharson 21 , Reference Carmi, Boughman and Ferencz 25 , Reference Marino, Vairo and Corno 29
Atrioventricular septal defect is often reported with associated cardiac defects. In our study, 140 cases with atrioventricular septal defect had 229 associated cardiac defects. The frequency of individual cardiac lesions has been reported with some inconsistency in the published literature.Reference Huggon, Cook, Smeeton, Magee and Sharland 7 , Reference Berg, Kaiser and Bender 9 , Reference Geva, Ayres, Pignatelli and Gajarski 14 , Reference Machado, Crawford, Anderson and Allan 18 – Reference Fesslova, Villa, Nava, Boschetto, Redaelli and Mannarino 20 , Reference Paladini, Volpe and Sglavo 26 , Reference Marino, Vairo and Corno 29 , Reference ter Heide, Thomson, Wharton and Gibbs 30 We found that coarctation of the aorta was the most prevalent, accounting for 21% of all associated cardiac defects.
For live-born infants with atrioventricular septal defect, overall survival past the first week of life was 94% with some variation between groups. Cases with heterotaxia had the lowest survival rate, whereas cases with isolated cardiac lesions had the highest survival rate, as has been shown in other studies.Reference Huggon, Cook, Smeeton, Magee and Sharland 7 , Reference Miller, Siffel, Lu, Riehle-Colarusso, Frías and Correa 17 , Reference Yıldırım, Gungorduk and Yazıcıoğlu 19 , Reference Fesslova, Villa, Nava, Boschetto, Redaelli and Mannarino 20 , Reference Allan 22 Atrioventricular septal defect associated with Down syndrome has been reported to have a better survival than non-Down syndrome cases probably because of a lower proportion of severe associated cardiac defects.Reference Boening, Scheewe and Heine 3 , Reference Berg, Kaiser and Bender 9 However, we found no significant difference in 1-week survival between chromosomal cases and non-chromosomal cases, as seen by Huggon et alReference Huggon, Cook, Smeeton, Magee and Sharland 7
Studies on prenatally diagnosed atrioventricular septal defects report poorer outcomes compared with studies on postnatally diagnosed cases.Reference Huggon, Cook, Smeeton, Magee and Sharland 7 , Reference Rasiah, Ewer, Miller, Wright, Tonks and Kilby 8 Surgical studies also report a high survival rate.Reference Boening, Scheewe and Heine 3 , Reference Huggon, Cook, Smeeton, Magee and Sharland 7 , Reference Calabrò and Limongelli 16 Surgical studies often exclude cases not suitable for surgery or those who die before surgery can be performed.Reference Huggon, Cook, Smeeton, Magee and Sharland 7 Therefore, caution should be used if using these studies in the counselling of parents with a foetus with a prenatal diagnosis of an atrioventricular septal defect.Reference Rasiah, Ewer, Miller, Wright, Tonks and Kilby 8
This study has a number of strengths. To our knowledge, it is the largest of its type. All cases have been thoroughly reviewed for classification of cardiac defects and syndromes, although our review was based solely on the International Classification of Diseases-9 and -10 codes given by the local registries. Data for the study are population based and have been routinely collected for many years using the same methodology and without bias for this specific cardiac defect.
A weakness of this study is that no cases were included if the diagnosis was made after 1 year of life. This underestimates the prevalence of primum atrial septal defect, as this defect may go unnoticed for years. This study was of a European population and may not be representative for other parts of the world or all ethnicities.Reference Hartman, Riehle-Colarusso and Lin 31 , Reference Ashok, Thangavel, Indrani and Suresh 32 Furthermore, for cases with non-isolated atrioventricular septal defect or chromosomal anomalies, it is uncertain whether the atrioventricular septal defect or another anomaly was diagnosed first.
Conclusion
The total prevalence of atrioventricular septal defect in Europe was 5.3 per 10,000 births (95% confidence interval 4.1 to 6.5). In our study, three-quarters of all atrioventricular septal defect cases were associated with chromosomal disorders or other congenital anomalies. Of the 25% with only cardiac defects, 30% had associated cardiac defects or unbalanced atrioventricular septal defect. The proportion of termination of pregnancy for foetal anomaly was high for cases with multiple anomalies, chromosomal anomalies, and heterotaxia sequence. For infants with atrioventricular septal defect and no chromosomal anomaly, cardiac defects were more often complex compared with infants with atrioventricular septal defect and a chromosomal anomaly.
Acknowledgements
Marian Bakker from The Netherlands, Miriam Gatt from Malta, Vera Nelen from Antwerp, Belgium, Mary O'Mahony from Cork, Ireland, and Joaquin Salvador from Barcelona collected data for the study. Contributorship: All co-authors have contributed significantly to this manuscript. Funding: This research received no specific funding. Competing interests: There are no competing interests.