





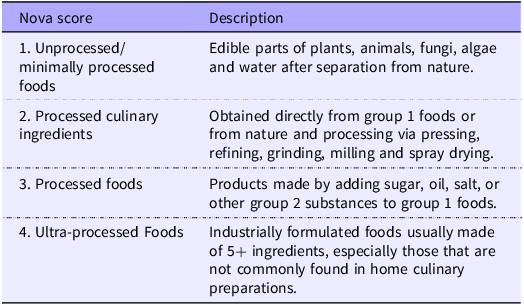
There is a great deal of concern in the nutrition science literature and among consumers about potential adverse cardiometabolic health impacts from eating ultra-processed foods (UPF)(Reference Crimarco, Landry and Gardner1,2) . The current body of research on UPF is largely comprised of observational studies, which indicate associations between increased intake of UPF and a range of adverse health outcomes including elevated blood pressure(Reference Barbosa, Sousa and de Oliveira Silva3,Reference da Silva Scaranni, de Oliveira Cardoso and Chor4) , excess weight gain(Reference Juul, Martinez-Steele and Parekh5,Reference Canhada, Luft and Giatti6) , CVD risk/incidence(Reference Rauber, Laura da Costa Louzada and Chang7–Reference Cordova, Viallon and Fontvieille9), inflammatory markers(Reference da Silva, Felício and Caldas10,Reference Lopes, Araújo and Levy11) and mortality(Reference Taneri, Wehrli and Roa-Díaz12). Evidence from intervention studies is limited. To address some of the gaps in the literature, a Research Roadmap for UPF was developed by experts from academia, government and industry in 2023(Reference O’Connor, Higgins and Smiljanec13). This Roadmap used the Nova system to identify more- and less-processed foods, as Nova is the most widely used classification system in nutrition literature, though several methods of characterising foods by ‘extent’ of processing have been published(Reference Lichtenstein, Appel and Vadiveloo14,Reference Dicken and Batterham15) . Nova classifies all foods into one of four groups: (1) unprocessed or minimally processed foods; (2) processed culinary ingredients; (3) processed foods and (4) UPF (Table 1)(Reference Monteiro, Cannon and Levy16–Reference Monteiro, Cannon and Lawrence18).
Nova scores and descriptions of different categories of food processing from Monteiro et al. (Reference Monteiro, Cannon and Levy16)

Table 1. Long description
A table categorizing foods based on their level of processing according to the Nova score system. The table has four rows and two columns. The first column is labeled Nova score and the second column is labeled Description. Row 1: Nova score 1, Description Edible parts of plants, animals, fungi, algae and water after separation from nature. Row 2: Nova score 2, Description Obtained directly from group 1 foods or from nature and processing via pressing, refining, grinding, milling and spray drying. Row 3: Nova score 3, Description Products made by adding sugar, oil, salt, or other group 2 substances to group 1 foods. Row 4: Nova score 4, Description Industrially formulated foods usually made of 5+ ingredients, especially those that are not commonly found in home culinary preparations.
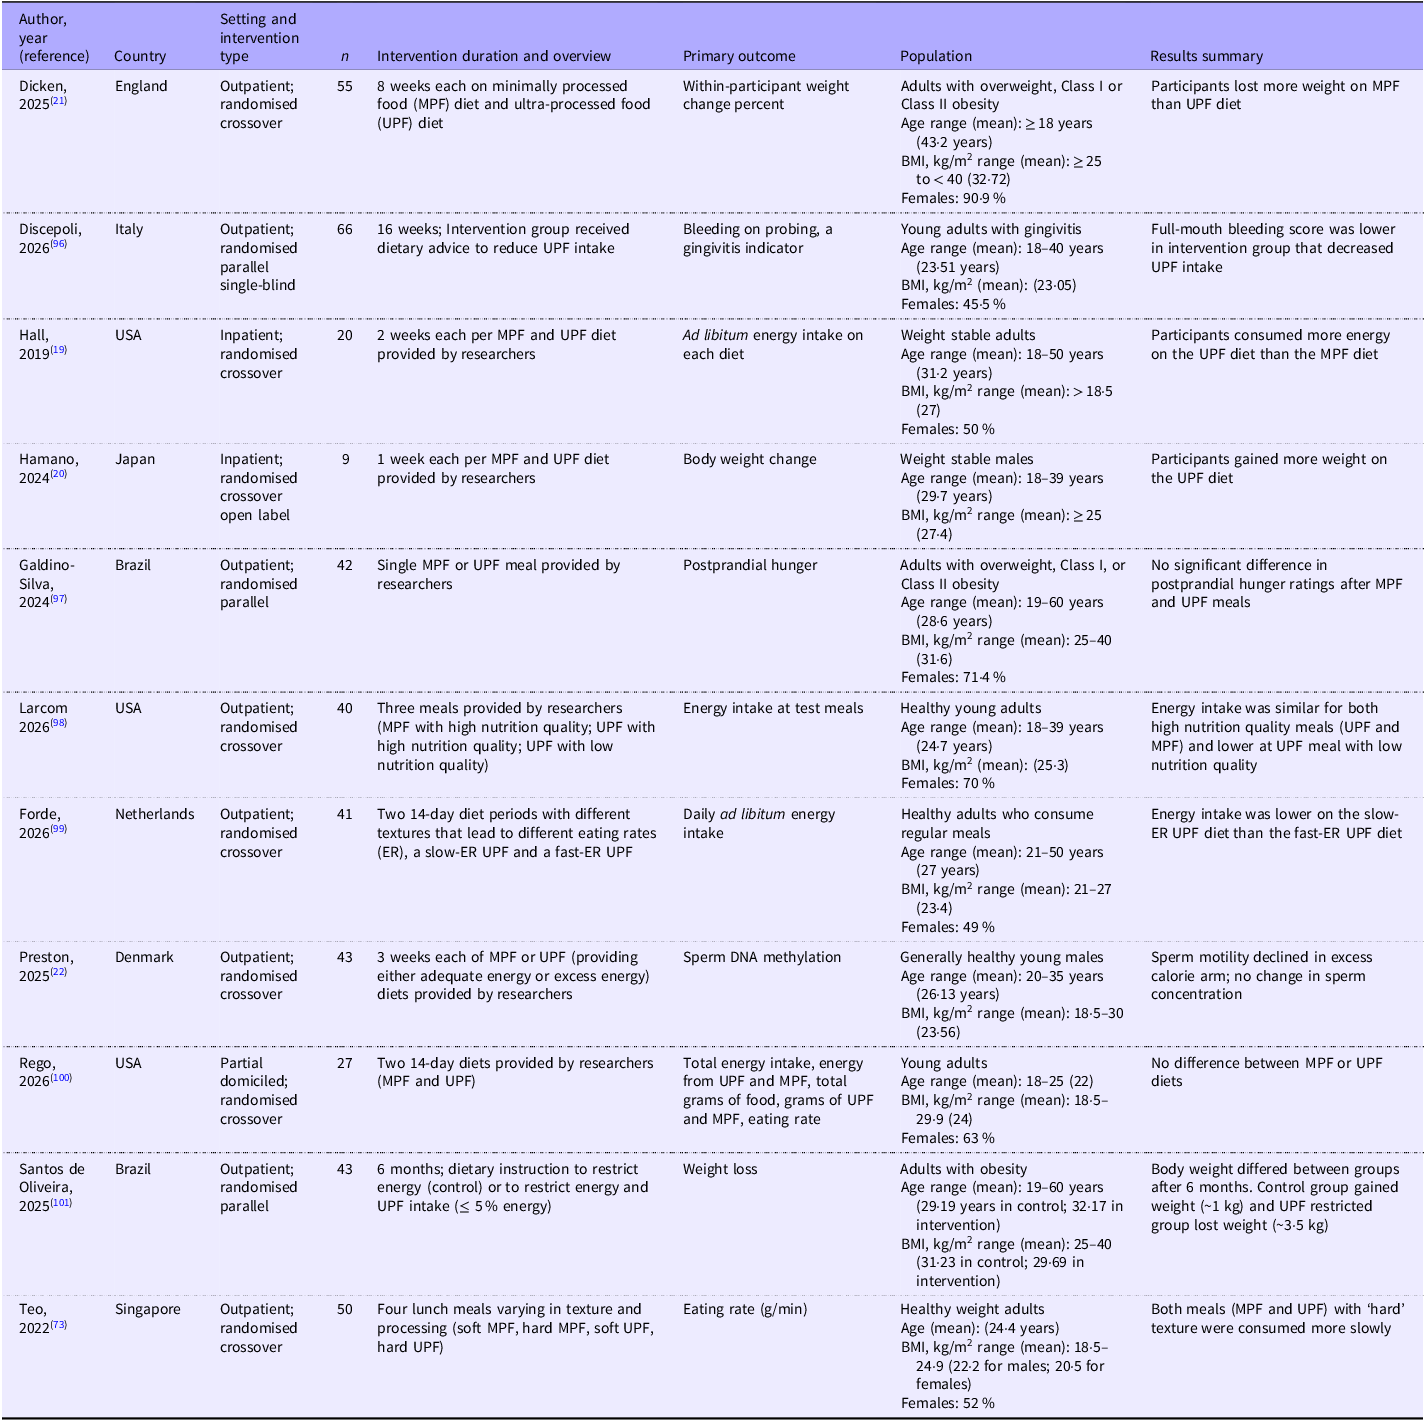
One of the research needs identified by the Roadmap was whether UPF intake influences risk for obesity or cardiometabolic disease, independent of diet quality. The Roadmap further stated that ‘randomized controlled trials matching dietary patterns for overall quality and food group intake are needed’(Reference O’Connor, Higgins and Smiljanec13). Even in 2026, evidence from intervention studies comparing diets comprised primarily of UPF with those comprised of mostly unprocessed foods on cardiometabolic health outcomes remains scarce(Reference Hall, Ayuketah and Brychta19–Reference Preston, Iversen and Hufnagel22), though more trials are in process(Reference Dinu, Angelino and Del Bo’23,24) . Table 2 provides a summary of randomised controlled trials that have been published to date, to our knowledge, on UPF.
Randomized controlled trials conducted on health impacts of ultra-processed food

Table 2. Long description
The table compares various studies on the health impacts of ultra-processed food. It has 10 rows and 6 columns. The columns are labeled Author (Year), Country, Setting and intervention type, Intervention duration and outcomes, Primary outcome, and Population. The rows list different studies with specific details under each column. For example, the first row includes Dicken (2027), England, Outpatient, randomized crossover, 8 weeks each on minimally processed food (MPF) diet and ultra-processed food (UPF) diet, Within-participant percent change, and Adults with overweight or obesity (Class 1 or Class 2), 18-45 years (43.2 percent female), BMI 25-29.9 kg/m^2 (mean: 27.5), 25-45 years (30.2 percent female), BMI 25-29.9 kg/m^2 (mean: 27.5). The table provides a detailed comparison of different studies, their settings, interventions, durations, outcomes, and populations.
Two randomised controlled trials that compared an ‘unprocessed’ food diet and an ‘ultra-processed’ food diet, per Nova, reported that a diet with most of its energy (kcal) coming from UPF led to greater energy intake and weight gain(Reference Hall, Ayuketah and Brychta19,Reference Hamano, Sawada and Aihara20) . A third randomised controlled trial compared two diets, one comprised of mostly UPF and the other comprised of mostly less-processed foods per Nova, both adhering to the UK’s dietary guidance(25), on weight change and cardiometabolic health markers(Reference Dicken, Jassil and Brown21). Both diets led to weight loss and improved health indicators, but the weight change was greater with the less-processed diet(Reference Dicken, Jassil and Brown21). A fourth intervention study assessed the impact of excess and adequate calories from unprocessed foods and UPF in men but focused on reproductive health indicators as a primary outcome(Reference Preston, Iversen and Hufnagel22).
Both the observational studies and randomised controlled trials on UPF published to date have important limitations. A major limitation of the observational research on UPF is the ability of these studies to accurately categorise foods according to Nova, because the granularity of data (e.g. brand names, product names and ingredient lists for individual food and beverage products) required to implement this categorisation system is not available in major datasets used to investigate interactions between foods from Nova groups and health outcomes(Reference Juul, Martinez-Steele and Parekh5,Reference Steele, Baraldi and Louzada26–Reference Vlassopoulos, Katidi and Noutsos33) . With the randomised controlled trials on UPF, two did not control for diet quality, food type or micronutrient content of the intervention diets(Reference Hall, Ayuketah and Brychta19,Reference Hamano, Sawada and Aihara20) , and one did not explicitly control for food type or micronutrient content(Reference Dicken, Jassil and Brown21). All three studies focused on weight as a primary outcome rather than cardiometabolic health markers. Additional research is required, therefore, to understand whether foods categorised as ‘ultra-processed’ on the Nova classification scale contribute to adverse cardiometabolic health outcomes when diet quality, nutrient content, energy intake and food type are all held constant. That is, further studies are needed to address the knowledge gap identified by the Research Roadmap.
While Nova is widely used to identify UPF products, some of the foods and beverages that are considered UPF in the Nova system are nutrient-dense, despite their level of processing(Reference Braesco, Souchon and Sauvant34,Reference Drewnowski, Gupta and Darmon35) . Dicken et al., for instance, developed an intervention diet aligning with the UK’s Eatwell Guide that included 90·7 % of energy from UPFs while meeting recommendations for macronutrient intake and servings of fruits, vegetables, dairy, and starchy foods(Reference Dicken, Jassil and Brown21). Some of the foods included in Dicken et al.’s healthy UPF menu include fruit and oat bars, plant-based milk, flavored yogurt, rice cakes, granola bars and multigrain breakfast cereals(Reference Dicken, Jassil and Brown21). Any extruded breakfast cereal is classified as a UPF according to Nova(Reference Martinez-Steele, Khandpur and Batis36). Breakfast cereals are also the top contributor to whole grain intake among Americans ages 2 years and older as well as a top contributor to calcium, vitamin D, potassium and fibre intake among Americans 1 year and older(37). Breakfast cereals, alongside other processed and packaged foods such as canned fish, whole grain and enriched breads and nut butters, have historically made important contributions to the nutrient-density of American dietary patterns(Reference Weaver, Dwyer and Fulgoni38).
Nova states that ‘ultra-processed foods are operationally distinguishable from processed foods by the presence of food substances of no culinary use’ and lists additives such as flavors and colors as two examples of these food substances(Reference Martinez-Steele, Khandpur and Batis36). Hundreds, if not thousands, of nutrient-dense foods have flavors and colors added, including items such as whole wheat banana bread, which may have natural or artificial vanilla and/or banana flavors added, and yellow cheddar cheese colored with annatto. Other foods with flavours and colours include premade salsa, canned corn, tinned fish, pizza sauces, trail mix, canned lentils, hummus, canned peaches, dried bananas, instant oatmeal, tofu, and hot wheat cereal, to provide some examples. Studies comparing Nova to nutrient profiling methods have found that UPFs fall into a wide range of nutrient densities(Reference Vlassopoulos, Katidi and Noutsos33,Reference Dicken, Batterham and Brown39–Reference Phulkerd, Dickie and Thongcharoenchupong44) . Diets containing mostly UPF (> 90 % total energy) can meet most recommendations from the 2020–2025 Dietary Guidelines for Americans (2020 DGA)(Reference Hess, Comeau and Casperson45), including micronutrient content. Yet, this type of nutrient-dense UPF diet has not been evaluated for its impact on health in a clinical trial.
This manuscript introduces a protocol for the Dietary Guidelines for Americans with Ultra-Processed foods (DGA-UP) study, an randomised controlled trial aimed at addressing gaps in UPF intake and cardiometabolic health through a feeding study with UPF- and unprocessed-foods intervention diets matched for diet quality, nutrient content, energy density and food type. The primary objective of DGA-UP is to evaluate the impact of diets composed primarily of ultra-processed or less processed foods that meet dietary guidelines recommendations on chronic disease risk factors. More specifically, when DGA-compliant diets comprised of mostly ultra-processed and less-processed foods (per Nova) are fed to generally healthy adults, determine whether there is an impact on blood pressure, fasting glucose and insulin concentrations, or blood lipids (total cholesterol, HDL-cholesterol, LDL-cholesterol and TAG). The hypothesis for this study is that changes in blood pressure (primary outcome), fasting glucose and insulin concentrations and changes in cholesterol levels (total, HDL-C, LDL-C) across the 4-week duration of each dietary intervention (ultra-processed DGA and less processed DGA) will not significantly differ between the groups following the intervention.
Blood pressure was selected as a primary outcome for several reasons. Cross-sectional studies(Reference Barbosa, Sousa and de Oliveira Silva3,Reference da Silva Scaranni, de Oliveira Cardoso and Chor4,Reference Steele, Juul and Neri46) and prospective cohort studies(Reference Mendonça, Lopes and Pimenta47,Reference Rezende-Alves, Hermsdorff and Miranda48) indicate an association between increased consumption of energy from UPF and hypertension. Hypertension is a leading risk factor for CVD, which has remained the most common cause of mortality in the USA, including throughout the COVID-19 pandemic(Reference Xu, Murphy and Kochanek49). However, the association between blood pressure and increased consumption of energy from UPF has not been studied in a clinical intervention study to allow for potential mechanisms to be identified and explored.
Experimental methods
Study design
DGA-UP is a randomised controlled crossover dietary intervention study performed with 4-week provision of all meals to generally healthy and normotensive, sedentary male and female adults at eucaloric levels. This study, registered at ClinicalTrials.gov (NCT07252037), will be conducted at the USA Department of Agriculture-Agricultural Research Service Grand Forks Human Nutrition Research Center (GFHNRC) from January 2026 through October 2029. The study protocol was approved by the University of North Dakota Institutional Review Board (IRB0006680). All study procedures will be conducted to align with the Declaration of Helsinki for human studies. Participants will provide written informed consent and have the chance to discuss any questions or concerns with study staff prior to starting the study and will be compensated for their participation.
The trial will consist of two dietary arms, both of which will include diets based on the Healthy USA Style Dietary Pattern (HUSDP) from the 2020 DGA:
-
1) an eucaloric less-processed HUSDP (LP-HUSDP; 4 weeks); and
-
2) an eucaloric ultra-processed HUSDP diet (UP-HUSDP; 4 weeks).
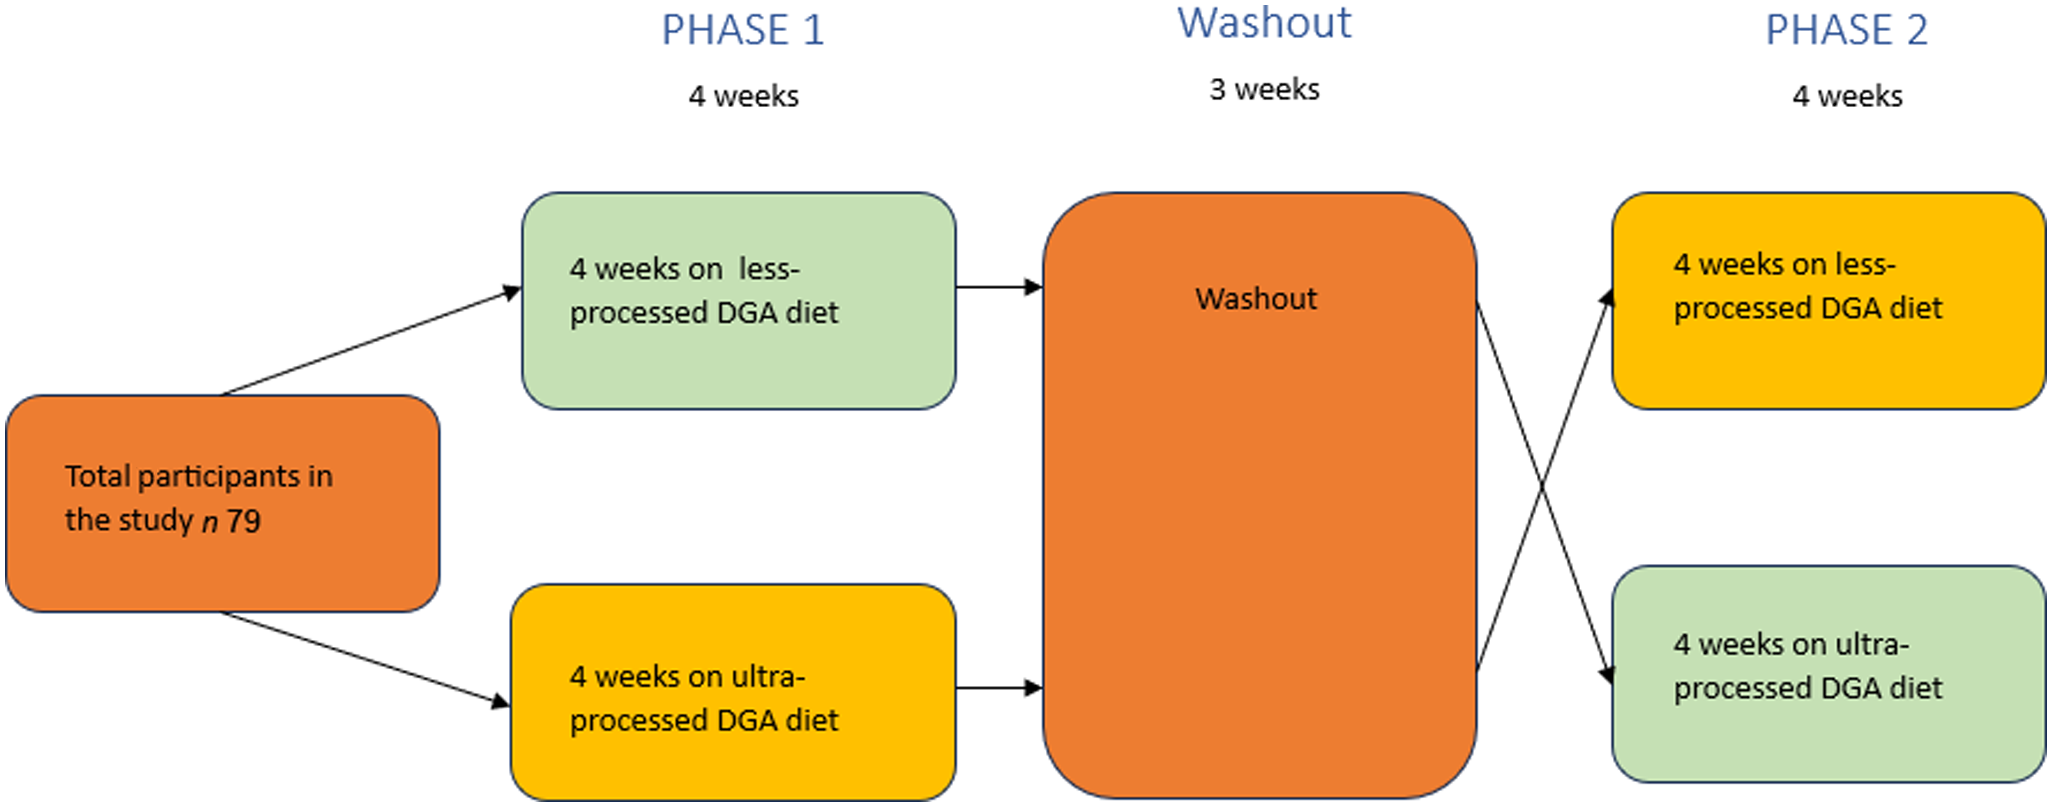
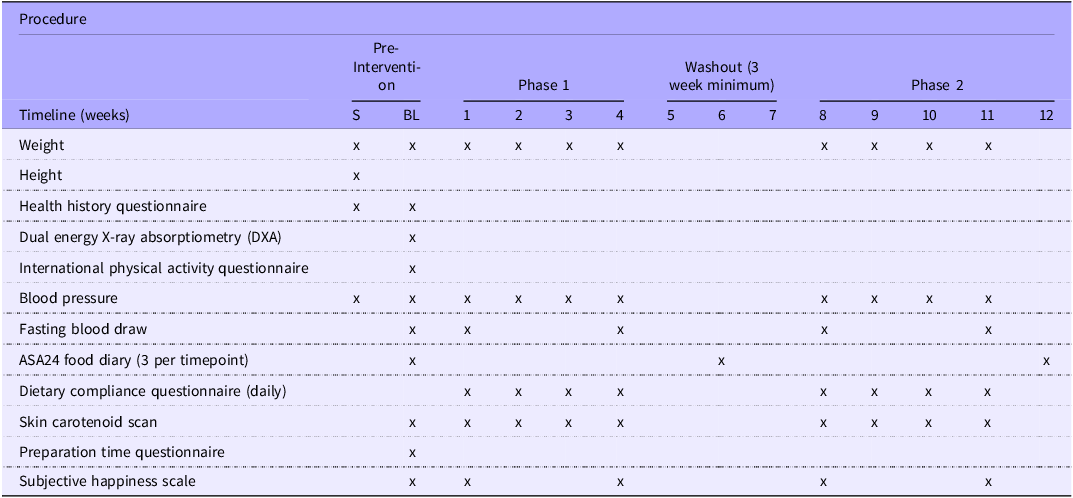
A schematic representation of the study’s two arms is shown in Figure 1, and an overview of study procedures is detailed in Table 3.
Study schematic for dietary intervention study comparing impact of unprocessed and ultra-processed DGA diets on cardiometabolic health outcomes. DGA, 2025 Dietary Guidelines for Americans.

Timeline of procedures included in the dietary guidelines for Americans with ultra-processed foods (DGA-up) study

Table 3. Long description
The table presents the timeline and procedures for a dietary study, structured into columns and rows. The columns represent the timeline in weeks, divided into Pre-Intervention, Phase 1, Washout (3 week minimum), and Phase 2. The rows list various procedures and measurements. Row 1: Timeline (weeks) with sub-columns S, BL, 1, 2, 3, 4, 5, 6, 7, 8, 9, 10, 11, 12. Row 2: Weight, measured at S, BL, 1, 2, 3, 4, 8, 9, 10, 11, 12. Row 3: Height, measured at S. Row 4: Health history questionnaire, measured at S and BL. Row 5: Dual energy X-ray absorptiometry (DXA), measured at BL. Row 6: International physical activity questionnaire, measured at S and BL. Row 7: Blood pressure, measured at S, BL, 1, 2, 3, 4, 8, 9, 10, 11, 12. Row 8: Fasting blood draw, measured at BL, 4, and 12. Row 9: ASA24 food diary (3 per timepoint), measured at BL and 12. Row 10: Dietary compliance questionnaire (daily), measured at 1, 2, 3, 4, 8, 9, 10, 11, 12. Row 11: Skin carotenoid scan, measured at S, BL, 4, and 12. Row 12: Preparation time questionnaire, measured at S. Row 13: Subjective happiness scale, measured at S, BL, 4, and 12. The table provides a detailed schedule of when each procedure is conducted throughout the study.
Dietary intervention
Menus for this study were developed using methods adapted from Hess et al. (Reference Hess, Comeau and Casperson45). The GFHNRC has a 2020 DGA base menu (5-day HEI-2015 score = 92·35) used in feeding studies to represent a ‘healthy diet’. This menu was used as the model for UP-HUSDP and LP-HUSDP with adjustments made to different ingredients and foods to accommodate processing levels. Both UP-HUSDP and LP-HUSDP are 5-day menus. Nutritional information for these menus was obtained by individually matching each menu item to its equivalent in a customised in-house nutrient analysis program developed at the GFHNRC and based on the USDA National Nutrient Database for Standard Reference, Legacy(50).
Initial determination of processing level (per Nova classification system) and DGA ‘fitness’ of each food were determined by consensus of three reviewers for each aspect (e.g. three experienced Nova classifiers and three experts on DGA dietary patterns/food groups). As the menu was adjusted for ingredient availability, formulation changes by food manufacturers and taste, subsequent determinations of Nova classifications were made via consensus of GFHNRC research staff.
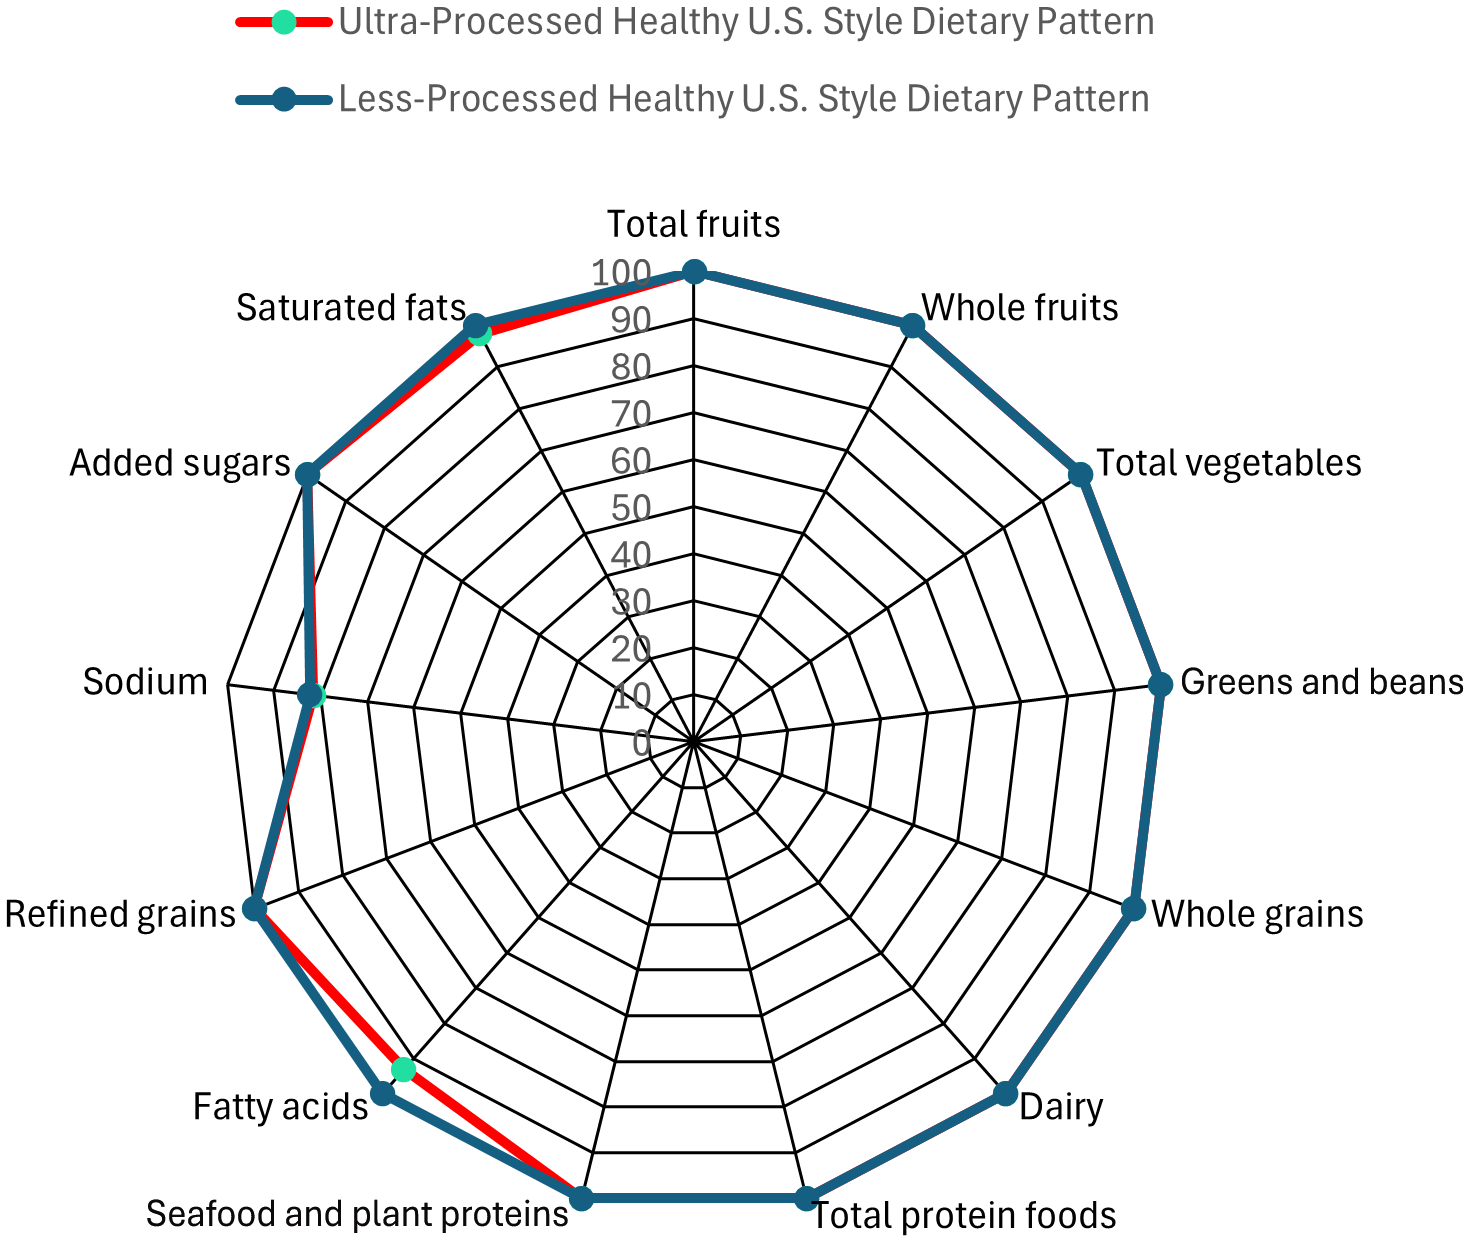
Participants will receive three meals and one snack per day and will be able to eat the provided food at a cadence of their choice. The LP-HUSDP includes 100 % kcal from foods from Nova categories 1–3, while the UP-HUSDP diet includes an average of 88 % kcal from Nova category 4/UPFs (across all 5 d). Both intervention menus have excellent diet quality as measured by Healthy Eating Index-2020 scores. LP-HUSDP has an Healthy Eating Index-2020 score of 98 and the UP-HUSDP has an Healthy Eating Index-2020 score of 97 (Figure 2). The 1-point difference in HEI scores is not a ‘meaningful’ one, according to research from USDA’s Center for Nutrition Policy and Promotion as well as the 2025 Dietary Guidelines Advisory Committee Report(37,Reference Kirkpatrick, Reedy and Krebs-Smith51) .
Radar plots depicting diet quality score of more- and less-processed menus included in the Dietary Guidelines for Americans-Ultra-Processed (DGA-UP) trial according to the Healthy Eating Index-2020 score. DGA, 2025 Dietary Guidelines for Americans.

Figure 2. Long description
Radar plots comparing diet quality scores of more- and less-processed menus according to the Healthy Eating Index-2020. The plots feature two lines representing Ultra-Processed Healthy U.S. Style Dietary Pattern and Less-Processed Healthy U.S. Style Dietary Pattern. The axes are labeled with various dietary components: Total fruits, Whole fruits, Total vegetables, Greens and beans, Whole grains, Dairy, Total protein foods, Seafood and plant proteins, Fatty acids, Refined grains, Sodium, Added sugars, and Saturated fats. The radar plots show that the less-processed dietary pattern scores higher in most components, particularly in whole fruits, total vegetables, greens and beans, whole grains, and seafood and plant proteins, while the ultra-processed dietary pattern scores higher in added sugars and saturated fats.
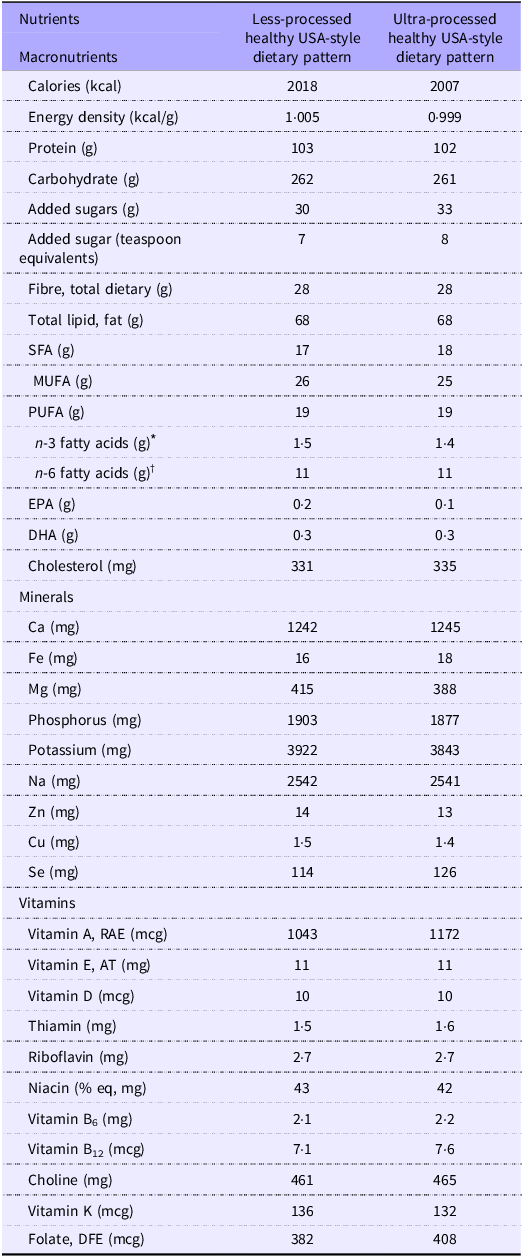
Both diets contain amounts of macronutrients within the Acceptable Macronutrient Distribution Ranges(52) and amounts of micronutrients within Dietary Reference Intakes(53). Na amounts exceed the Chronic Disease Risk Reduction recommendation of 2300 mg per day(54) in the two intervention diets. However, the Na amounts in the two diets are nearly equivalent. The LP-HUSDP contains 2542 mg of Na. Total sugar and saturated fat amounts are below 10 % of total energy in both diets, which is within recommendations from the 2020 DGA(53). The UP-HUSDP has 33 g added sugar (7 % total sugar), and the LP-HUSDP has 30 g added sugars (6 % of total energy). The UP-HUSDP contains 18 g saturated fatty acids (7·9 % of total energy), while the LP-HUSDP has 17 g saturated fatty acids (7·5 % of total energy).
The participant menu can be viewed in online Supplementary Table 1, and the nutrient profile of the intervention diets are in Table 4. Intervention menus were finalised after testing by the GFHNRC Dietary Core for food preparation feasibility, storage stability and taste. All foods and caloric beverages will be prepared by our metabolic kitchen staff using commercially available foods and provided as a 5-day rotating menu (e.g. the same meals would be provided on a Monday and a Saturday). The table in online Supplementary Table 2 shows the servings from each food group in the HUSDP from the 2020 DGA, which was used as the model for developing the intervention diets in this study(53). Pictures of both study menus can be found in online Supplementary Figure 3.
Average nutrient profiles of 5-day intervention menus that follow the 2020–2025 dietary guidelines for Americans with mostly ultra-processed or less-processed food

Table 4. Long description
A table comparing nutrient profiles of less-processed and ultra-processed healthy USA-style dietary patterns. The table has 22 rows and 4 columns. Column headers are Nutrients, Macronutrients, Less-processed healthy USA-style dietary pattern, and Ultra-processed healthy USA-style dietary pattern. Row labels include Calories (kcal), Energy density (kcal/g), Protein (g), Carbohydrate (g), Added sugars (g), Added sugar (teaspoon equivalents), Fibre, total dietary (g), Total lipid, fat (g), SFA (g), MUFA (g), PUFA (g), n-3 fatty acids (g), n-6 fatty acids (g), EPA (g), DHA (g), Cholesterol (mg), Ca (mg), Fe (mg), Mg (mg), Phosphorus (mg), Potassium (mg), Na (mg), Zn (mg), Cu (mg), Se (mg), Vitamin A, RAE (mcg), Vitamin E, AT (mg), Vitamin D (mcg), Thiamin (mg), Riboflavin (mg), Niacin (% eq, mg), Vitamin B6 (mg), Vitamin B12 (mcg), Choline (mg), Vitamin K (mcg), Folate, DFE (mcg). Each row provides values for both dietary patterns.
* n-3 fatty acids include the sum of amounts of alpha-linolenic acid (ALA), docosahexanoic acid (DHA) and eicosapentanoic acid (EPA).
† n-6 fatty acids include the sum of amounts of linoleic acid (LA), gamma-linolenic acid (GLA) and arachidonic acid (AA).
Participants and screening
Participants (n 79) will be recruited from the Grand Forks, ND (USA) community. Adults eligible to participate will include apparently healthy males and females ≤ 65 years of age with blood pressure in the normal to Stage I hypertensive range(Reference Whelton, Carey and Aronow55) and BMI between 18·5 and 34·9 kg/m2. Participants must be able to understand and sign the consent form, have their own transportation to study visits and be willing to eat study food and comply with study demands. Participants may not be taking statins, medication to lower blood pressure, weight loss medication or anti-inflammatory or anti-diabetes medications. Participants will be excluded if they are pregnant or planning to become pregnant, lactating, have a diagnosed eating disorder, smoke, have cancer, or report regular exercise.
Prior to study participation, all initially eligible participants will be invited to an informational meeting where the protocols will be explained and written informed consent obtained. Informational meetings will be followed by a screening exam, detailed below, to determine if prospective participants are eligible.
Recruitment
Participants will be recruited by the study staff members using targeted recruitment efforts to meet the demographic goals for participants in this study. Potential participants will be recruited through advertising in the Grand Forks metropolitan area via brochures, online advertisements, newsletters, flyers, expos and trade shows, in addition to the GFHNRC website. The GFHNRC has a decades-long history of successful human research, including feeding trials of 4–12 weeks(Reference Casperson, Jahns and Duke56–Reference Flack, Ufholz and Casperson60). Participants will be recruited until seventy-nine have completed all study requirements. Anticipating a 20 percent potential dropout rate, approximately ninety-five participants will need to be enrolled for seventy-nine participants to complete the study.
Randomisation
After study enrollment, participants will be randomised into treatment groups stratified by age and sex groups. Randomisation will be performed by the trial statistician. Participants will be informed that this study measures the effects of ‘ultra-processed’ and ‘less-processed’ diets on cardiometabolic health but will be blinded to their individual order of diet interventions throughout trial data collection. Researchers will not be blinded to the intervention assignments.
Experimental protocol
Screening (S) exam
The screening exam includes: (1) anthropometric measurements, (2) resting blood pressure and a (3) health history questionnaire. After the informational meeting has been conducted and informed consent provided, height, weight and resting blood pressure will be obtained to ensure eligibility. Anthropometric measurements will be done in bare or socked feet and light clothing. Blood pressure will be taken by trained study staff using the automated ADC ADView 2 Modular Diagnostic Station (American Diagnostic Corporation). Participants will rest for 5 min in a comfortable sitting position (legs uncrossed, back and measurement arm supported). Three measurements will be taken with 2-minute intervals, and the average of these multiple readings will then be calculated and recorded. Individuals meeting anthropomorphic and blood pressure inclusion criteria will be selected to participate in the study. After completing the screening and informed consent, participants will be scheduled for a baseline study visit.
Baseline study visit
Baseline diet will be assessed using a series of three food diaries completed with the ASA24 Automated Self-Administered Dietary Assessment Tool(61). Reflection spectroscopy (Veggie Meter; Longevity Link Corp.) will be conducted to measure skin carotenoids(Reference Jahns, Johnson and Mayne62,Reference Jilcott Pitts, Jahns and Wu63) , and participants will complete the Subjective Happiness Scale questionnaire(Reference Lyubomirsky and Lepper64). A food preparation time questionnaire based on survey questions provided as part of National Health and Nutrition Examination Survey 2007–2010 and using cut-points established by Wolfson et al. will be given at this visit as well(Reference Wolfson, Martinez-Steele and Tucker65). Dual energy X-ray absorptiometry scans will be conducted to determine body composition. Calibration to external standards will be performed prior to each individual scan. Absence of pregnancy will be confirmed in all pre-menopausal women prior the scan. Participants will complete the International Physical Activity Questionnaire(Reference Bassett66), which will be used to calculate their energy requirements in conjunction with the Dietary Reference Intakes for Energy from the National Academies for Science Engineering and Medicine(67).
Phase 1
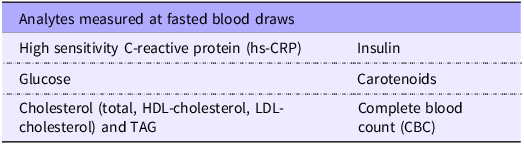
Participants will be randomised into one of the two dietary interventions (UP-HUSDP or LP-HUSDP) for the first 4 weeks (Figure 1). Each dietary group will be provided all meals (food and drink, except water) for 4 weeks. Participants will pick up their food Monday–Friday at a time that is convenient for them to promote study adherence. Participants in both groups will receive diets with adequate energy to maintain their baseline weight (as determined by estimated energy requirements from the National Academies for Science Engineering and Medicine(67)) and instructed to consume all food and beverages provided. Participants will visit the GFHNRC facility once a week throughout the 4-week period to have their blood pressure measured, to be weighed and to address any potential questions or issues with study compliance. Energy will be adjusted to maintain starting weight. A change in body weight of > 2 kg that is sustained for 2 consecutive weeks will be used as the criteria for determining when an adjustment in energy level is necessary. At the beginning and end of each phase, participants will also complete a fasted blood draw as part of the GFHNRC facility visit as well as the Subjective Happiness Scale (see Table 5 for analytes and online Supplementary Document 4 for explanation and method of analysis for blood samples). Participants will complete a daily dietary compliance questionnaire (online Supplementary Document 5) throughout the intervention period, asking if they ate everything provided or anything not provided.
Analytes measured at fasted blood draws within the dietary guidelines for Americans with ultra-processed foods (DGA-up) study

Table 5. Long description
A table listing analytes measured in fasted blood draws. The table has two columns and six rows. The first column lists the following analytes: High sensitivity C-reactive protein (hs-CRP), Glucose, Cholesterol (total, HDL-cholesterol, LDL-cholesterol) and TAG, Insulin, Carotenoids, and Complete blood count (CBC). The second column is empty.
Adherence to the intervention diets will also be assessed with an objective method. In addition to the daily dietary compliance questionnaire, reflection spectroscopy measurements(Reference Jahns, Johnson and Mayne62,Reference Jilcott Pitts, Jahns and Wu63) will be performed weekly at facility visits. Participants will be told that reflection spectroscopy measures adherence to the diets. Changes in skin carotenoids can be detected with an increase in carotenoid-containing fruit and vegetable intake of only 0·8 cup-equivalents(Reference Jahns, Johnson and Mayne62). This objective measure of compliance also instills a measure of accountability to participants. Each week, participants will also be weighed, another measure of compliance.
Washout
Participants will go through a minimum 3-week washout period between diets, a longer period than the 5 d washout used by a previous intervention study (the Dietary Approaches to Stop Hypertension trial, or ‘DASH’) also with blood pressure as a primary outcome measure(Reference Juraschek, Miller and Weaver68). Participants will also complete (3) 24 h food diaries during the second week of the washout period.
Phase 2
Participants will then consume the second dietary intervention for 4 weeks (Figure 1). Besides the change in dietary intervention, Phase 2 will mirror the procedures included in Phase 1.
Statistical analysis and data management plan
Power analysis
Three endpoints were used to calculate power for this study – fasting glucose, fasting TAG and systolic blood pressure and the highest participant number from the three measures was selected for the study implementation to ensure the strongest possible study was conducted with available resources. Data informing fasting glucose and fasting TAG calculations for power calculations come from the Krishnan et al.’s study conducted at the USA Department of Agriculture-Agricultural Research Service Western Human Nutrition Research Center, an intervention trial on DGA-adherent diets among women with overweight or obesity(Reference Krishnan, Adams and Allen69). Data informing systolic blood pressure calculations come from Zhang et al.’s study assessing blood pressure among Americans with data from National Health and Nutrition Examination Survey(Reference Zhang, Cogswell and Gillespie70).
Fasting glucose
The power for this endpoint was calculated via a mean difference in fasting glucose of 1·2 mg/dl at week 4 for the diets with a 100(1–2
 $\alpha$
)% confidence interval contained inside an equivalence region with lower bounds and upper bounds of −5 mg/dl and 5 mg/dl(71), respectively, with a standard deviation of 10·9 mg/dl, a correlation of 0·5 within subjects, a significance level of
 $\alpha$
= 0·05 and a power of 0·9 yields a total sample size of seventy-nine subjects. This assumes no carryover or period effects as well as no interactions between subjects, diets and periods.
Fasting TAG
The power for this endpoint was calculated via a mean difference in fasting glucose of 11·1 mg/dl at week 4 for the diets with a 100(1–2
 $\alpha$
)% CI contained inside an equivalence region with lower bounds and upper bounds of −42 mg/dl and 42 mg/dl, respectively, with a standard deviation of 78·8 mg/dl, a correlation of 0·5 within subjects, a significance level of
 $\alpha$
= 0·05 and a power of 0·9 yields a total sample size of seven-eight subjects. This assumes no carryover or period effects as well as no interactions between subjects, diets and periods.
Systolic blood pressure
The power for this study was calculated via a mean difference in systolic blood pressure of 1 mm Hg at week 4 for the diets with a 100(1–2
 $\alpha$
)% CI contained inside an equivalence region with lower bounds and upper bounds of −5 mm Hg and 5 mm Hg,(71) respectively, with a standard deviation of 10 mm Hg, a correlation of 0·5 within subjects, a significance level of
 $\alpha$
= 0·05 and a power of 0·9 yields a total sample size of fifty-six subjects. This assumes no carryover or period effects as well as no interactions between subjects, diets and periods.
A mean difference of 1 mm Hg is anticipated at week 4 based on National Health and Nutrition Examination Survey data that indicates most American adults consume 2745 mg/d of potassium(Reference Zhang, Cogswell and Gillespie70). Because the intervention diets provided in this study contain an additional 1000 mg/d potassium above typical intake, a 1 mm Hg difference in blood pressure corresponding with this increase in potassium intake after 4 weeks on each intervention diet is expected(Reference Zhang, Cogswell and Gillespie70).
Data analysis
The data from this study will be analysed using a mixed model with all relevant biomarkers as outcomes and fixed effects of diet (UP-HUSDP or LP-HUSDP), week (1, 2, 3, 4; 8, 9, 10, 11), diet x sequence (UP-HUSDP/LP-HUSDP, LP-HUSDP/UP-HUSDP) and phase (1, 2) and a random effect of subject not nested within treatment. The mixed model is used as it can account for missing data and perform intent-to-treat analyses(Reference Carpenter and Kenward72). If the diet x sequence interaction is significant, a carryover effect is assumed, and a contrast will be written to compare the diets at the first time point. A contrast will be written to compare the diets at the fourth week, and, if the 100(1–2
 $\alpha$
)% CI for the difference is contained completely within the equivalence bounds of –5 to 5 (systolic blood pressure), the null hypotheses of inferiority and superiority two one-sided tests are rejected.
Age, percentage body fat, baseline UPF intake, baseline diet quality as determined from ASA24 Automated Self-Administered Dietary Assessment Tool analysis and hypertension stage (normal or Stage I) will be evaluated as potential covariates of systolic blood pressure as will reflection spectroscopy measurements.
Data monitoring and management
Data entry will be conducted separately by two study staff members to ensure data quality. Due to low risk of adverse events from participation in this study, a data monitoring committee will not be established. For data retention, the GFHNRC current practices will be followed. That is, any hard copy data records will be stored for a minimum of 3 years from the time the study is completed. Electronic data records will be maintained for a period of at least 5 years after the study has been completed. Any paper records generated from this study will be accessible only by research personnel and will be kept in locked and secure storage. Computer files will be accessible only by research personnel and protected by passwords and encryption. Data transfer conducted electronically will be through secure email and encrypted external storage. All active servers are managed and backed up daily by USDA Information Technology. Data are available to study personnel throughout the duration of the study on the GFHNRC’s Center Automated Research System, a secure database established specifically to house data from human studies conducted at the GFHNRC. Any shared data will be de-identified.
Discussion
Overall, DGA-UP will help clarify the utility of Nova and the UPF label to define healthful dietary patterns, a gap in the literature identified by the 2023 Research Roadmap(Reference O’Connor, Higgins and Smiljanec13). One of the few differences between the two interventions (UP-HUSDP and LP-HUSDP) is the number and nature of additives in the foods and beverages provided in the menus. The foods and beverages in UP-HUSDP have seventy-six ingredients and additives (online Supplementary Document 6) from calcium disodium EDTA to dextrose to sucralose not present in the LP-HUSDP. While the menus look identical in most respects, the food formulations indicate clear distinctions. Pilot testing of the menu indicates that the menus taste similar as well. The similarities in appearance and taste between the two diets will allow participants to be blinded as to the current arm of the trial they are in, an important strength of this trial.
UP-HUSDP and LP-HUSDP were developed from the same base menu with differences between the two menus arising only from the Nova classification of the ingredients used to make the meals. For instance, the whole grain bread on the LP-HUSDP is homemade wheat bread, while the wheat bread on the UP-HUSDP is mass-produced. As another example, some meals in DGA-UP include 100 % fruit juice since the 2020 DGA recognises 100 % fruit juice as an item that can provide a serving of fruit(53). Both the LP-HUSDP and the UP-HUSDP include 100 % fruit juices. However, the 100 % fruit juice in the UP-HUSDP includes ‘cosmetic additives’ (natural flavours, citric acid) that make it a UPF while the 100 % fruit juice in the LP-HUSDP lists 100 % fruit juice as its sole ingredient, a Nova Group 1 food. The menus are matched in food type and preparation, so the food textures are identical in nearly all meals, a factor that can affect eating rate and satiety(Reference Teo, Lim and Goh73,Reference Lasschuijt, Heuven and Gonzalez-Estanol74) . Importantly, the energy density of the two menus is matched as well (1·0 kcal/g after rounding). UPF do not necessarily have higher energy density than ‘less-processed’ foods as defined by the Nova classification system(Reference Hamano, Sawada and Aihara20). Furthermore, the menus on DGA-UP will not be provided ad libitum, and participants will be actively monitored to confirm that they do not gain or lose weight throughout the intervention, ensuring that changes in cardiometabolic health markers are not due to weight fluctuations.
Other strengths of this trial include the use of dual energy X-ray absorptiometry to measure body composition and the intervention duration. Dual energy X-ray absorptiometry is an established method for evaluating adiposity(Reference Shepherd, Ng and Sommer75) that has been used by only one of the other RCT comparing more- and less-processed menus(Reference Hall, Ayuketah and Brychta19). The four-week duration of the trial was selected based on past research that indicates that 4 weeks is a sufficient intervention duration to obtain differences in blood pressure and is a commonly used intervention duration for this primary endpoint(Reference Appel, Moore and Obarzanek76–Reference Chiu, Bergeron and Williams81). Four weeks is also a sufficient timeframe to detect changes in fasting glucose and insulin(Reference Turner, Keogh and Clifton82–Reference Mateo-Gallego, Perez-Calahorra and Cenarro85) and changes in the lipoprotein panel measures(Reference Müller, Lindman and Brantsaeter86–Reference Kris-Etherton and Dietschy94).
While a dietary intervention among a free-living population will be an important strength of this trial, the ‘free-living’ situation also limits participant monitoring. This study may provide a more realistic assessment of how eating or not eating a UPF-rich diet affects health markers when integrated into regular life, but conducting the study outside of an inpatient setting prohibits strict monitoring of food and beverage consumption and eating intake patterns such as eating rate and eating frequency. Participants will be instructed to maintain their normal daily habits and avoid activity that would not normally be part of their routine. In addition, participants will receive instructions about menu additions to avoid throughout the interventions. Despite these instructions, participants may add UPF items to the less processed menu such as diet sodas or seltzer waters or add salt or fat to the provided meals with butter, sugar, or Na-containing seasonings, all of which would be deviations from the research protocol. The research staff will monitor study compliance with daily questionnaires and weekly face-to-face meetings. Participants will be reminded often that truthfulness is valued over ‘perfection’.
The most challenging limitation of this study is the frequent formulation changes of foods and beverages by manufacturers. Some products selected for the UP-HUSDP may become ‘processed’ (Group 3) foods during the duration of the trial if certain ingredients or additives are removed or replaced and some products on the LP-HUSDP may become ‘ultra-processed’ if certain ingredients or additives are added. Additionally, manufacturers sometimes discontinue products as well. Since beginning to track UPFs in 2022, we have identified changes to approximately 5 % of products in our UPF database(Reference Hess, Bodensteiner and Johnson95), inclusive of both discontinuations and formulation changes. Any of these changes to items on the LP-HUSDP or UP-HUSDP will disrupt the study menu and require revisions to one or both menus for future participants. To mitigate the impact of formulation changes, the ingredient contents of both menus will be reviewed on a regular basis and changes made as needed to ensure the UP-HUSDP contains mostly energy from Nova Group 4 foods and the LP-HUSDP contains only foods that fit into Nova Groups 1, 2 and 3.
Overall, the DGA-UP trial will advance research on food classification by processing, providing insight into whether additives and ingredients not commonly used in home cooking affect cardiometabolic health outcomes when fed as part of a healthy dietary pattern to generally healthy adults.
Dissemination
Results of this study will be disseminated through a series of peer-reviewed publications as well as presentations to the research community, health care professionals, policymakers and the public. Following the acceptance of study data for initial publication in a peer-reviewed journal, de-identified participant data will be stored and made available to other researchers via an online data repository (Open Science Framework).
Supplementary material
For supplementary material/s referred to in this article, please visit https://doi.org/10.1017/S0007114526108034
Acknowledgements
We thank Mary Jo Peltier and Deb Sauve for their work in developing the study menus. And we thank evaluators who reviewed all menu items for Nova classifications and ability to be included in the Dietary Guidelines for Americans. Finally, we thank all the participants who will be involved in this study.
Supported by USDA Agricultural Research Service project grant # 3062-10700-003-00D.
J. M. H.: Conceptualisation-Lead, Funding acquisition-Lead, Investigation-Lead, Methodology-Lead, Project administration-Lead, Writing – original draft-Lead, Writing – review & editing-Equal; C. P. S.: Writing – original draft-Supporting, Writing – review & editing-Equal; A. J. S.: Data curation-Supporting, Writing – review & editing-Equal; S. C.: Conceptualisation-Supporting, Methodology-Supporting, Writing – review & editing-Equal; J. L. S.: Writing – review & editing-Equal; D. G. P.: Formal analysis-Lead, Methodology-Supporting, Writing – review & editing-Supporting.
J. M. H., C. J. P., A. J. S., S. C. and D. G. P. declare that they have no known competing financial interests or personal relationships that could have appeared to influence the work reported in this paper. J. L. S. has received research support from Taiyo and Barilla, serves on scientific advisory boards for Simply Good Foods, Sustainable Nutrition, Olipop, Kenvue and the Institute for the Advancement of Food and Nutrition Science (IAFNS). J. S. also owns Slavin Sisters Farm LLC, a 119-acre mixed-use family farm in Walworth, WI.


 Open access

