We partner with a secure submission system to handle manuscript submissions.
Please note:
You will need an account for the submission system, which is separate to your Cambridge Core account. For login and submission support, please visit the
submission and support pages.
Please review this journal's author instructions, particularly the
preparing your materials
page, before submitting your manuscript.
Click Proceed to submission system to continue to our partner's website.
To save this undefined to your undefined account, please select one or more formats and confirm that you agree to abide by our usage policies. If this is the first time you used this feature, you will be asked to authorise Cambridge Core to connect with your undefined account.
Find out more about saving content to .
To send this article to your Kindle, first ensure no-reply@cambridge.org is added to your Approved Personal Document E-mail List under your Personal Document Settings on the Manage Your Content and Devices page of your Amazon account. Then enter the ‘name’ part of your Kindle email address below. Find out more about sending to your Kindle.
Find out more about saving to your Kindle.
Note you can select to save to either the @free.kindle.com or @kindle.com variations. ‘@free.kindle.com’ emails are free but can only be saved to your device when it is connected to wi-fi. ‘@kindle.com’ emails can be delivered even when you are not connected to wi-fi, but note that service fees apply.
The Tonga Emergency Medical Assistance Team (TEMAT) responded to the Hunga Tonga-Hunga Ha’apai (HTHH) volcano and tsunami in early 2022. The HTHH volcano erupted violently on January 15, 2022 triggering a tsunami that struck many of Tonga’s 169 islands.1 84% of the country’s population was affected.2 Tonga’s undersea internet cable was cut, stopping most communication. At the time of the eruption/tsunami, Tonga was COVID-19-free with its borders effectively closed, forcing reliance on national emergency resources, including TEMAT.
Objectives:
Describe TEMAT’s response to the 2022 HTHH volcano eruption and tsunami.
Method/Description:
TEMAT deployed four rotations of clinical and public health teams in response to the eruption/tsunami. Team members included clinicians from the Ministry of Health, with logistics support from His Majesty’s Armed Forces. TEMAT carried out emergency assessments, facilitated medical evacuations, aided in the evacuation of an entire island’s population, and provided essential health services.
Results/Outcomes:
From January 17 through March 4, 2022, TEMAT cared for 381 patients including patients with non-communicable diseases (>50), psychosocial complaints (39), communicable diseases (27), and traumatic injuries (13). The team supported five referrals to higher level care, conducted patients home visits, aided in health center repairs, and responded to a boat sinking during their deployment.
Conclusion:
TEMAT’s deployment demonstrates that deployment-ready and self-sufficient national EMTs are essential for response to sudden-onset disasters in vulnerable countries. A trained and well-prepared national EMT can respond independently, quickly, and effectively to emergencies, despite limited resources and high-impact events.
Japan is a country with many disasters. Japan’s disaster medical system has improved significantly over the past 30 years by gaining experience in various disasters. Japan is implementing one of the unique disaster medical teams raised from experience and needs.
Objectives:
Introducing the Japan Disaster Medical Assistance Team (DMAT) system and discussing how the domestic disaster medical team should be.
Method/Description:
Referring to the actual response to domestic disasters and the development of disaster medical teams in Japan.
Results/Outcomes:
The National Emergency Medical Teams (National-EMT), Japan DMAT, was established in 2005. Currently, DMAT is 1,754 teams and over 15,862 members were registered. The team usually consists of five to six personnel, including two doctors, two nurses, and two logisticians. Each team carries standardized equipment. Japan DMAT will not set up a field hospital in the disaster area. Japan DMAT will bring a team to the Disaster Base Hospitals (DBHs) and start supporting the affected hospital operation first. Then, if there are other affected patients within DBH’s medical jurisdiction, then the team will mobile and support each hospital and clinic for further medical assistance.
Conclusion:
Having National-EMT in your own country is necessary for disaster-prone countries. Still, it is also required to consider what type of EMT needs to be established, referring already existing emergency medical system of your country.
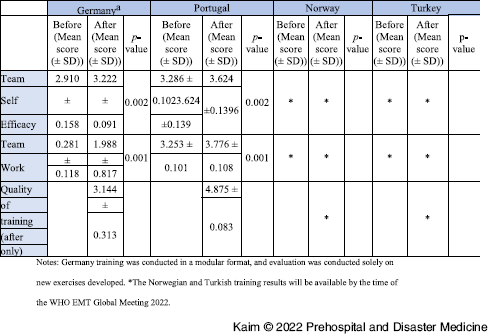
In the aftermath of disasters, Emergency Medical Teams (EMTs) are dispatched to help local rescue efforts. Although EMTs are recognized to be a critical component of the global health workforce, concerns have emerged over their functioning and effectiveness.1 For example, lack of cooperation and coordination between different EMTs has been a longstanding issue, resulting in fragmented disaster management.2 To enhance the provision of EMT’s field teamwork, the Training for Emergency Medical Teams and European Medical Corps (TEAMS) project was established,3 and later further updated with novel scenarios and exercises (ie, adapting EMT operations to a sudden disaster; becoming a modular team; reflecting on ethical dilemmas) in the complementary “TEAMS 3.0” project where a more comprehensive training package was developed.
Objectives:
The aim of this study was to assess the effectiveness and quality of the TEAMS 3.0 training package in four training programs in Portugal, Germany, Norway, and Turkey.
Method/Description:
Participants completed a set of questionnaires designed to assess self-efficacy, teamwork, and quality of training.
Results/Outcomes:
The results from the Portugal and German training suggest an improvement for both teams’ self-efficacy and teamwork. The quality of training is regarded as high and deemed as an appropriate tool package for addressing the objectives of the project and the perceived needs of EMT disaster deployment.
Conclusion:
Thus far, the TEAMS 3.0 project has demonstrated to be effective in promoting EMT teamwork capacities. The Norwegian and Turkish training results are expected to be available by the time of the WHO EMT Global Meeting 2022.
Tables and Figures (optional)
Table 1.
Comparison of Means Before and After the TEAMS 3.0 Training, per Country, for the Team Self-Efficacy Scale, Teamwork Scale, and Quality of Training Scale
The WHO has recommended the inclusion of rehabilitation capabilities in EMTs responding to disasters and health emergencies since 2013. Likewise, the importance of rehabilitation input across the continuum of care for patients experiencing COVID-19 illness has been highlighted since the onset of the global COVID-19 pandemic. Despite recognition of the role and value of rehabilitation, both in EMTs and the management of COVID-19, evidence that EMTs activated in response to COVID-19 have deployed rehabilitation professionals remains limited.
Objectives:
This paper will describe the experiences of the Australian Medical Assistance Team (AUSMAT) in deploying rehabilitation professionals as an integrated capability of multi-disciplinary EMTs responding to COVID-19 health emergencies.
Method/Description:
In response to COVID-19 emergencies in Papua New Guinea, Fiji, Timor-Leste, and the Solomon Islands, AUSMAT deployed rehabilitation professionals alongside multi-disciplinary EMTs on four occasions in 2021-2022. The rehabilitation professionals engaged in direct clinical care and capacity-building activities.
Results/Outcomes:
The work of the deployed AUSMAT rehabilitation professionals facilitated important capacity building and support for local rehabilitation staff and services, enhanced the time critical multi-disciplinary training of local nursing and medical staff, and improved the quality of clinical care of COVID-19 patients.
Conclusion:
AUSMAT’s experience has demonstrated that the deployment of rehabilitation professionals as part of a multi-disciplinary team adds significant value to the work of EMTs responding to COVID-19 health emergencies. Nursing and medical staff cannot readily replicate the knowledge, skills, and perspectives of rehabilitation professionals. Appropriately skilled rehabilitation professionals should be deployed to support national rehabilitation staff when EMTs respond to health emergencies.
In November 2021, a tanker exploded in Freetown, injuring and killing people. The WHO facilitated a seven-week first deployment of the Senegalese military to support the Ministry of Health (MOH) in providing care to the wounded in three referral hospitals.
Objectives:
Review the deployed team’s processes and outputs of medical care provided to burns patients.
Method/Description:
This is a cross-sectional After-Action Review (AAR) debrief of the deployment, including the WHO and MOH staff (n =14) in a virtual workshop. Six thematic areas: mobilization, deployment, coordination, case management activities, national capacity, and community acceptance were analyzed.
Results/Outcomes:
The WHO facilitated the team’s deployment and mobilized medical supplies and equipment whilst the MOH provided accommodation and logistics through collaboration. The team dispensed their functions with professionalism, adapted to the environment and available resources, and augmented the care provided by the available health workers. They offered additional care: reconstructive surgery, pain management, palliative and wound care, rehabilitation, physiotherapy, and psychosocial counselling, which were initially inadequate. 87 out of 155 patients were discharged home at the end, the national clinicians acquired additional skills, and the community appreciated the team. Despite being perceived as a weakness, the language barrier did not hinder the patient-doctor/nurse relationship or the provision of clinical care.
Conclusion:
This sub-regional response had significant benefits, including speed, political acceptability, and health context experience to support rapid and safe deployment. Mechanisms to facilitate rapid and quality-assured deployment of EMTs at regional and sub-regional levels in collaboration with WHO should be strengthened in region to support future responses.
Palau is a small island/large ocean nation in the Pacific with a population of approximately 18,000 and a high level of vulnerability to natural or climate-related disasters. In June 2022, Palau became the smallest nation in the world by population to establish a national Emergency Medical Team (EMT). The team is named “Klemat,” after the rope that holds the sails of Palau’s traditional canoes.
Objectives:
To establish a national EMT capable of self-sufficient, high-quality clinical response to disasters and outbreaks that may occur locally or in neighboring jurisdictions.
Method/Description:
The development of Klemat required a multi-step process with support from technical and funding partners. Online orientation webinars and meetings were held in 2019 and 2020, and a national Technical Working Group (TWG) was formed in 2022. A national EMT coordinator was jointly hired by the WHO and the Ministry of Health and Human Services of Palau in 2022, and EMT Standard Operating Procedures were drafted.
Results/Outcomes:
Klemat is the nation’s deployable clinical response capacity, capable of fully self-sufficient tented out-patient and emergency care in the most austere disaster or outbreak circumstances. There are now 18 fully trained clinical and support team members. Klemat is working with relevant stakeholders to be codified in the national disaster risk management framework of Palau.
Conclusion:
Palau’s development of a national EMT demonstrates that even the smallest of countries can establish self-sufficient EMTs capable of national or regional response.
The Induction Team Member (ITM) course is compulsory training for teams setting up an EMT. It encapsulates elements around safety and security, protocols and procedures, and familiarization with equipment and should happen in countries that have undergone the awareness session.1 Tailoring the ITM course to fit different countries settings and professional backgrounds is imperative, particularly in Africa, because countries have heterogeneous characteristics.
Objectives:
To describe the changes to the ITM Course curriculum adapted to the different professional backgrounds and technical scopes of potential team members (TM) and African countries.
Method/Description:
This is an After-Action Review (AAR) of in-depth feedback (n = 10) received from participants in the five trainings that have been conducted at the WHO African Regional EMT Training Center (TC) since 2021 to date. All analyses were done thematically.
Results/Outcomes:
The training experiences in the region have shown the need for three imperative modifications to the ITM course based on the type of EMTs and the background of the participants. These include ITM courses focusing on health workers (Doctors and Nurses); team leads, security, and logistics officials; and support staff that can work during deployment and pre-deployment tasks. An interactive ten steps to building an operational national EMTs initiative developed to fit the context has been shown as significant.
Conclusion:
Conceptualizing ITM course training for EMTs based on teams’ backgrounds, cultural circumstances, and political will is imperative for enhancing the capacity of regional countries’ EMTs. A pragmatic modification to the training to fit the context that captures the countries’ needs is key.
As disasters disrupt health systems and create additional health needs, Mobile Health Units (MHU) are deployed to help cover primary health care (PHC) needs. However, MHUs have been critiqued for being logistically burdensome and poorly adapted to dominating health needs. Guidelines exist, including WHO Classification for Emergency Medical Teams (EMT) Type 1 mobile, but the usefulness of MHUs in disasters has been poorly studied.
Objectives:
To explore the use of MHUs for PHC in disasters and identify key characteristics as described in the literature.
Method/Description:
A scoping review was conducted following framework by Arksey and O’Malley using thematic content analysis. Twenty-six bibliographic databases and websites were screened for white and grey literature on the use of MHUs in disasters published from 2000-2021.
Results/Outcomes:
The search resulted in 24 reviews and operational reports, highlighting nine themes. While MHUs were reported to improve health service delivery, 16 documents highlighted challenges related to logistics, organization, and coordination. Seven publications described cooperation with local authorities and stakeholders to help improve relevancy of care by adapting service provision to health needs. Several studies highlighted the need for a functioning referral system and inclusion of local and culturally sensitive staff.
Conclusion:
Findings of this study highlight the added value and areas of improvement of MHUs for PHC in disasters. Recommendations of best practices were proposed based on the literature and may guide future deployments. However, there is a paucity of publications, and further data on EMT Type 1 mobile are needed to evaluate MHUs in disasters and improve guidelines.
As natural disasters continue to cause human suffering and contribute to health inequalities, Mobile Health Units (MHU) provide medical aid to people deprived of health care. However, the service modality has received criticism related to logistical difficulties, irregular service provision, and adaptability. Although MHUs may be of value, there is a significant knowledge gap regarding their usefulness on addressing health needs in natural disasters.
Objectives:
To elucidate the use of MHUs in natural disasters in adherence to WHO Classification for Emergency Medical Teams.
Method/Description:
A scoping review was conducted following the framework by Arksey and O’Malley. Twenty-six bibliographic databases and websites were screened for white and grey literature published from 2000-2021 reporting on the use of MHUs in natural disasters.
Results/Outcomes:
Thirteen publications were included in the final analysis, highlighting seven themes: key characteristics, services, staff, benchmark indicator, operational availability, self-sufficiency, and pre-deployment preparedness. All documents described the mobile approach to increase access to health services in the absence of regular health care. MHUs were mostly reported to provide out-patient care with medical needs primarily related to non-communicable diseases. Basic trauma care was less reported on. The main challenges concerned transportation, coordination, and communication.
Conclusion:
Data on the use of MHUs in natural disasters are scarce with inconsistent reporting of key aspects. The literature adhered to previous research and WHO guidelines to some extent. Further research is deemed necessary to evaluate the interventions and outcomes of MHUs following natural disasters.
Pacific Island Countries and Areas (PICs) represent some of the most logistically challenging locations, covering vast ocean territory and remote islands. Light, mobile clinical response capability is critical in the disaster-prone Pacific. Beginning in January 2021, WHO researched, tailored, and procured EMT cache “kits” specifically for Pacific Island contexts, based on the core standards of the global EMT initiative.
Objectives:
To research, tailor, and procure cache “kits” to ensure self-sufficiency and high-quality out-patient mobile medical care for national EMTs in PICs.
Method/Description:
WHO facilitated the development of national cache kits for 10 PICs EMTs. A need for specialized equipment and supplies or “cache” for team self-reliance is critical. Through a consultative process, including Pacific EMT leadership and team members, EMT mentors, and regional partners, WHO curated and procured cache kits for 10 PICs EMTs.
Results/Outcomes:
The Pacific EMT cache kit is designed for four-to-six-person teams with the capacity to deploy for a minimum of three days, with full self-sufficiency. Because of the complex and remote access to many Pacific Islands, EMT cache must be practical for transport on small aircrafts and maritime vessels. A consultative process resulted in a curated cache list for Pacific national EMTs of over 125 items, estimated to weigh approximately 440 kilograms per kit. By the end of 2022, a total 31 kits will be delivered to EMTs in ten countries.
Conclusion:
The design, development, and procurement of Pacific EMT cache for national response operations will allow for increased speed and agility for response to disasters and public health emergencies.
Many Pacific governments have committed to establishing deployable, self-sufficient national EMTs following recent tropical cyclones, measles outbreaks, and the COVID-19 pandemic. However, for much of the COVD-19 pandemic, PICs have closed international borders limiting in-person team member training.
Objectives:
To develop a remote, interactive EMT training series to engage current and prospective EMT team members in the PICs during the COVID-19 pandemic.
Method/Description:
From July through September 2021, WHO hosted a weekly webinar series to introduce the concepts of the EMT Initiative to current and prospective EMT team members in the PICs. The sessions utilized Pacific deployment experience using faculty from EMTs in Australia, Fiji, New Zealand, Papua New Guinea, Solomon Islands, Tonga, and Vanuatu.
Results/Outcomes:
Attendees from over 23 countries from across the Pacific and other areas of the world participated in the 11 sessions, with a total of over 300 individual participants. The average number of participants per sessions was 85. Feedback was sought after every session. The most significant adaptation of the sessions from the feedback was incorporating the Pacific tradition of talanoa, or storytelling, into the sessions.
Conclusion:
Adapting the session plans to incorporate the talanoa style of communication in the Pacific created an environment of learning from colleagues throughout the Pacific and increased participant engagement in the virtual setting. The webinar series provided knowledge of EMT basics and increased engagement and excitement in the establishment and continued growth of EMTs in the Pacific.
WHO EMTs play an important role in providing assistance and health care services to countries hit by an emergency or a natural disaster. Therefore, EMTs are subjected to vastly different cultures from various countries, meaning they require training to cultural awareness, an understanding and acceptance of the languages, beliefs, cultures, and morals of those receiving care. The World Health Organization (WHO) has published minimum standards for Emergency Medical Teams (EMTs), which briefly mention that the senior EMT team member must have some knowledge of cultural awareness. However, there is no requirement for cultural awareness training for EMTs prior to responding to disasters.
Objectives:
The goal of this study is to determine the presence of cultural awareness training, and if present, what are the competencies covered by the training for the WHO EMTs.
Method/Description:
A survey will be distributed to Accredited WHO EMTs to capture the presence for cultural awareness training and the core competencies of the existing training.
Results/Outcomes:
Data expected to be collected and analyzed by October 1, 2022.
Conclusion:
Cultural awareness training is a crucial and beneficial skill for EMTs while deploying internationally. For WHO EMTs, it is essential to respond internationally in an accepted and ethical manner; cultural awareness training should be a requirement for all teams deploying to a foreign country. A cultural awareness curriculum will create more efficient EMTs that provide effective aid to countries in need.
The country’s location makes it vulnerable to natural disasters, hence, the PEMAT’s potential was tested during local disaster response for Taal Volcano Eruption in Batangas last January 2020 and during the aftermath of Super Typhoon Odette in Dinagat Islands last December 2021, amidst COVID-19 surge.
Objectives:
The primary objective of the deployment was to augment the DOH in the provision of safe, effective, and efficient quality health care services appropriate to the victims’ needs, timely, and coordinated mobilization of DJNRMHS PEMAT, and to evaluate the knowledge and skills acquired in the EMT Basic induction course in disaster response.
Method/Description:
As per WHO standards, disaster responses conducted by the DJNRMHS PEMAT followed three important phases: pre-mobilization, mobilization, and post-mobilization. The methods used during these phases in Taal and Dinagat missions were the simulation of drills and application of didactics learnt from the EMT Basic Induction Course for Disaster Response conducted by the DOH in collaboration with WHO in 2019.
Results/Outcomes:
The essential services rendered by DJNRMHS PEMAT, ensuring patient and responder safety despite being at the height of COVID-19 surge, were out-patient, acute emergency, trauma and basic obstetric care, basic laboratory, social welfare, public health, and pharmaceutical to 1,124 victims in the Taal Eruption and 1,089 victims of Typhoon Odette.
Conclusion:
Safe and effective delivery of quality health care services by PEMAT, a team equipped with knowledge and skills acquired through mentorship, can be achieved with thorough planning, setting of mission objectives, and most importantly, having full support from the management and all stakeholders.
The humanitarian health field has grown rapidly in the last decades. However, education and training programs are still limited in number, especially where it is needed most. Additionally, the cost of the training is too expensive for local humanitarian health respondents. If developed appropriately, E-Learning can potentially address these gaps.
Objectives:
Develop an effective E-Learning tool for humanitarian public health training.
Method/Description:
The tool was developed using an institutional-based, action research method. Rapid prototyping - a modified analysis, design, development, implementation, and evaluation (ADDIE) model - was used to identify the content and instructional design. This iterative process involved consultations and feedback from public health and disaster medicine instructors and students at different levels and training programs. Different methods were used to collect and analyze data, such as literature and courses reviews, observation, interviews, and questionnaires.
Results/Outcomes:
Four scenario-based E-Simulations - targeting entry-level humanitarian health professionals - were developed and piloted based on identified needs. Formative evaluation clarified training objectives and structure. Trainees were satisfied by the simulated scenario, interactivity, questions, and timely feedback. Poor internet was identified as a potential barrier to delivering the training in the humanitarian context.
Conclusion:
Clear objectives and quality content are the prerequisites for training effectiveness. Yet, instructional design is a critical element that can enhance training effectiveness. The tool’s offline mode is being adapted to improve access in poor internet connection settings. A summative evaluation will be conducted to measure the training’s effectiveness. Furthermore, successful factors in instructional design will be used to inform the development of advanced training in the field.
Tropical Cyclone Yasa made landfall on Fiji’s main islands as a Category 5 cyclone on December 17, 2020 causing an immense impact on the health system with damages to health infrastructure amounting to 1.2 million USD.1 FEMAT was activated to assess and assist with disaster response in the greatly impacted Northern and Eastern Divisions of Fiji.
Objectives:
To describe FEMAT’s response to Tropical Cyclone Yasa.
Method/Description:
FEMAT’s response to TC Yasa included community assessments, provision of medical supplies and temporary tents for health facilities, and coordinating the distribution of WASH kits. FEMAT’s Health Emergency Response Team (HERT) was mobilized and provided surveillance support and medical care in Evacuation Centers (EC) treating the injured and sick. Health inspectors were deployed with FEMAT to provide food safety surveillance and management of dead animals near and in water sources.
Results/Outcomes:
Four mobile FEMAT teams were deployed during the TC Yasa response for 17 days over the Christmas and New Year holidays. Teams were composed of physicians, nurses, and health inspectors, and were provided with vehicles stocked with medications, medical supplies, food, and tents. 354 different communities were visited by FEMAT HERT teams, including five islands, 170 villages, 167 settlements, four estates, and eight evacuation centers. 1,172 out-patient medical encounters were recorded. Over 110 sites were treated for potential vectors by spraying and disinfection.
Conclusion:
FEMAT operationalized a small, mobile medical teams approach to respond to Category 5 tropical cyclone that impacted Fiji in December of 2020.
Pacific Island Countries and Areas (PICs) represent some of the most remote and logistically challenging locations – with thousands of islands covering vast ocean territory. Since 2017, Pacific Ministries of Health have been developing EMTs, and all have worked to train team members to be deployment-ready.1
Objectives:
To describe an EMT training package specifically tailored to PIC contexts, including curated content, practical exercises, and “talanoa” discussions to improve EMT readiness, with a focus on logistics in remote and austere PIC contexts.
Method/Description:
WHO leveraged EMT training materials developed globally and regionally to continuously tailor an in-person EMT training package, emphasizing readiness for the deployment of light, mobile clinical teams for disaster-prone small island/large ocean countries. Emphasis was placed on practical learning exercises focusing on skills and competencies needed to manage complex Pacific deployments, and to care for populations on remote, difficult-to-reach islands with limited resources and referral options.
Results/Outcomes:
The Pacific EMT training program includes a mix of didactic and practical sessions coupled with a full-scale simulation exercise; it was designed with and for Pacific EMTs. The effectiveness of the training package has been evidenced through many successful national EMT deployments in several PICs, as well as through consistently positive participant feedback.
Conclusion:
Tailoring training materials to specific country contexts is essential. In the Pacific, core EMT training content with an emphasis on practical activities and simulations and “talanoa” discussions reflecting on previous deployments in remote islands has been viewed by participants as critical to preparing them for real-world deployments.
Fiji consists of 110 populated islands over an area of 2,600,000 square kilometers and is prone to disasters such as tropical cyclones.1 To increase national capacity to respond to disasters and outbreak, the Fijian government, under the commissioning of Ministry of Transport and with technical guidance from the Ministry of Health, designed a medical ship called the MV Veivueti. During Fiji’s COVID-19 surge, MV Veivueti was utilized to provide operative health services during the surge in COVID-19 patients at other health facilities.2
Objectives:
To describe FEMAT’s COVID-19 response utilizing the medical ship, MV Veivueti, in Fiji’s Pacific island setting.
Method/Description:
MV Veivueti has been used on multiple disaster responses, however the COVID-19 surge in mid-2021 was the first time the vessel was used during an outbreak to allow for the continuation of surgeries when other health facilities were overwhelmed with COVID-19 patients. The medical ship is staffed with a comprehensive team from Fiji’s EMT - FEMAT - including surgeons, pediatricians, obstetricians, a dentist, nurses, and other medical staff.
Results/Outcomes:
From May 5 through July 6, 2021, a 12-member medical team staffed the medical ship 24-hours a day, providing primarily operative management of cases that were referred from health facilities. COVID-19 screening and IPC measures were in place and a clear patient flow was designed for patient transferred to health care facilities.
Conclusion:
The use of the MV Veivueti helped ensure continuity of critical health services during the peak of the Delta VOC outbreak in the Fiji Islands.
UK-Med, as part of our UK EMT project, deployed a team to respond to the overwhelming surge in COVID-19 cases in Papua New Guinea in late 2021. Such deployment was associated with several risks, including natural hazards; earthquakes; societal crisis; tribal fighting and civil unrest; and health risks such as extreme temperatures and poor sanitation infrastructure presented further hazards to personnel safety.
Objectives:
To share lessons learned on enhancing the well-being of an EMT in a challenging context such as PNG.
Method/Description:
Satisfaction survey, bilateral meetings, in addition to weekly meetings with the headquarters held throughout the deployment.
Results/Outcomes:
All deployed team members felt exhausted early in the deployment, including an early lack of clarity on the deployment location which eventually ended up being Mount Hagen, a very risky area only accessible by plane. Utilizing emotional and social support, diversity acceptance within the team, and coherent coordination between team members the deployment delivered upon all agreed objectives. Local staff were integrated and a successful workplan was well-received and evaluated as making a real difference to the staff and patients, with a request for an extension of activities received from the Provincial Health Authority.
Conclusion:
Considerations for staff well-being need to counter-balance the need for strict security protocols. Solid feedback mechanisms should be designed and implemented at an early stage of deployments to avoid any adverse effect on the team’s well-being. Deployment of an assessment team should strengthen coordination, ensuring required needs are being responded to and operational planning is location/context specific.