To save content items to your account,
please confirm that you agree to abide by our usage policies.
If this is the first time you use this feature, you will be asked to authorise Cambridge Core to connect with your account.
Find out more about saving content to .
To save content items to your Kindle, first ensure no-reply@cambridge.org
is added to your Approved Personal Document E-mail List under your Personal Document Settings
on the Manage Your Content and Devices page of your Amazon account. Then enter the ‘name’ part
of your Kindle email address below.
Find out more about saving to your Kindle.
Note you can select to save to either the @free.kindle.com or @kindle.com variations.
‘@free.kindle.com’ emails are free but can only be saved to your device when it is connected to wi-fi.
‘@kindle.com’ emails can be delivered even when you are not connected to wi-fi, but note that service fees apply.
Obesity is characterised by the dysregulation of the neurobiological systems governing hunger, satiety and food reward. Dysfunction in signalling across the gut-brain axis impairs both homeostatic and hedonic control of eating, ultimately resulting in excessive energy intake. The weight loss achieved through pharmacological and surgical interventions is not primarily the result of cognitive behavioural restraint; it instead reflects the direct biological modification of the neuroendocrine circuits involved in regulation of eating behaviour. This review applies a conceptual framework structured around two axes; homeostatic versus hedonic eating and the appetitive versus consummatory phases of feeding to interpret how these interventions change eating behaviour. Bariatric surgery has a substantially more mature evidence base. The Roux-en-Y gastric bypass in particular, produces sustained modification in consummatory homeostatic behaviour – with earlier satiation and meal termination, in conjunction with short-term changes in food preferences. Evidence for GLP-1 receptor agonists and dual GIP/GLP-1 receptor agonists demonstrates a parallel profile of reduced hunger, increased satiety, attenuated food-cue reactivity and subduing of the hedonic drive. Whether the effects of pharmacotherapy and surgery engage in the same biological processes and whether their effects follow a similar time course remains an unresolved question. We consider the implications of this framework for nutrition and dietetic practice.
Different types of bariatric surgeries, such as malabsorptive and restrictive procedures, can impact nutrient absorption and metabolism. One of the concerns for reproductive-aged women and pregnancy-capable individuals undergoing bariatric surgery is the increased risk of nutritional deficiencies during pregnancy and breastfeeding. This review aimed to collate and synthesise available literature on nutritional status during pregnancy and breastfeeding post-bariatric surgery. The Preferred Reporting Items for Systematic Reviews and Meta-Analyses extension for Scoping Reviews framework was used. It included peer-reviewed primary research studies published in English that reported the nutritional status of women with histories of bariatric surgery during pregnancy and breastfeeding. There were no time restrictions for including studies. A narrative synthesis was performed to summarise and interpret the findings. Anaemia and micronutrient deficiencies were frequently reported during pregnancy after bariatric surgery. Malabsorptive procedures were associated with greater micronutrient deficiencies during pregnancy, while the surgery-to-conception interval showed no consistent association. Macronutrient intake during pregnancy was characterised by high fat intake, low carbohydrate and fibre intake, and adequate protein intake. There was limited evidence of altered breast milk macronutrient composition following bariatric surgery. Limited qualitative studies showed that women wanted more nutritional information and support during pregnancy and breastfeeding following bariatric surgery. These findings highlight the need for individualised nutritional care, regular biochemical monitoring, and multidisciplinary management for women and pregnancy-capable individuals during pregnancy and breastfeeding following bariatric surgery, particularly after malabsorptive procedures. Further research is required to address gaps in evidence regarding mothers’ experiences and breast milk composition after bariatric surgery.
A mutual influence between mood disorders and obesity has been reported. Maladapting eating behaviors associated with mood spectrum swings may play a pivotal role in the development and maintenance of obesity. Considering that, the aim of the present study is to investigate the relationship between problematic eating behaviors, namely emotional eating, grazing and night eating, with impulsivity and lifetime mood spectrum (mood, energy, cognition, rhythmicity and vegetative functions) in severe obese patients seeking bariatric surgery.
Methods
304 obese outpatients were recruited at the Psychiatric Unit of the University Hospital of Pisa. Participants completed psychometric tools including the Emotional Eating Scale (EES), the Italian-Night Eating Questionnaire (I-NEQ), the Grazing Questionnaire (GRAZ), the Barratt Impulsiveness Scale (BIS-11), and the Mood Spectrum Self-Report – lifetime version (MOODS-SR). Descriptive analyses and linear correlation were performed.
Results
The sample was predominantly female (71.4%), with a mean age of 47.5 ± 10.9 years and a mean BMI of 43.3 ± 6.3 kg/m2. Impulsivity was positively correlated with depressive and manic mood, energy, and cognitive MOODS-SR domains. Emotional eating, night eating, and grazing were significantly associated with the MOODS-SR total score (r=0.422, p=0.000; r=0.321, p=0.001; r=0.321, p=0.000, respectively) and with specific depressive and manic subdomains of the MOODS-SR.
Conclusion
Loss-of-control eating behaviors were positively associated with lifetime depressive and manic mood spectrum features in bariatric patients, highlighting the importance of assessing these dimensions to promote a tailored and integrated treatment.
The potential of obesity medications to serve as viable alternatives to bariatric surgery to treat obesity remains an open question. This review examines whether contemporary anti-obesity pharmacotherapy can replace metabolic and bariatric surgery in the management of obesity, by critically comparing their mechanisms of action, weight loss outcomes, durability, safety profiles and roles in long-term disease control. While metabolic/bariatric surgery has been the gold standard for substantial and sustained weight loss, advancements in pharmacotherapy are producing weight loss approaching surgical outcomes without associated risks, complications and recovery time. New drug therapies demonstrate previously unattainable efficacy and long-term control of obesity. Surgery, however, induces superior short- and long-term weight loss via profound hormonal, neurological and metabolic shifts, resulting in durable outcomes without ongoing intervention, though it remains difficult to scale. Pharmacotherapy is scalable and increasingly effective but requires sustained adherence, with loss of treatment-mediated control and weight regain upon cessation. It also does not have as extensive established research on safety as surgery. While obesity medications cannot fully replicate the multifactorial physiological impacts of metabolic/bariatric surgery, they offer a scalable, less invasive treatment path that broadens patient options. So far, pharmacotherapy will not replace surgery, as there are patients who will respond better to it, while others to medication only. However, combining both surgical and pharmacological options can increase the penetrance of treatments to manage the chronic complexities of obesity.
Obesity and overweight in pregnant women increase pregnancy and neonatal morbidity with a risk of metabolic syndrome for children in later life. Maternal preconceptional bariatric surgery reduces maternal and paediatric outcomes but may induce fetal nutritional deficiencies and intrauterine growth restriction through placental reprogramming. The aim of this study was to describe feto-placental unit modifications induced by obesity, and the effect of bariatric surgery performed before gestation, on a diet-induced obese rat model. One month after surgery, rats of ‘control’, ‘obese’ and ‘bariatric surgery’ groups were mated and then sacrificed at D19 of gestation. Clinical description, immuno-histochemistry and molecular analyses were performed on feto-placental units. Obesity induces placental modifications including lipid accumulations, increased inflammation and oxidative stress. Some of these modifications are partially restored by maternal preconceptional bariatric surgery. On the other hand, a reduction in the expression of markers of glucose transport, insulin function and amino acid transport, after bariatric surgery was observed. This phenotype may lead to fetal caloric restriction, adoption of a ‘thrifty phenotype’ and subsequently fetal growth restriction. These preliminary findings highlight the importance of a close follow-up of women who have undergone bariatric surgery and their children.
Severe obesity in adolescents is a public health crisis of increasing concern. Cardiac maladaptation, such as left ventricular hypertrophy, increases the risk of future cardiovascular disease. This study aims to evaluate the impact of weight loss surgery on cardiac geometry in morbidly obese adolescents.
Methods:
A single-centre, randomised controlled trial titled comparing laparoscopic adjustable gastric banding with multidisciplinary lifestyle intervention against a control group with multidisciplinary lifestyle intervention alone. The trial included severely obese adolescents aged 14–16 who had not responded to a minimum of 12 months of multidisciplinary lifestyle intervention. The primary outcome measured was the percentage change in total body weight one year after surgery. Left ventricular geometry was evaluated ultrasonographically before and one year after bariatric surgery.
Results:
In the intervention and control group, a total of 10 and 8 patients received both the baseline and follow-up ultrasonographic examination. BMI significantly decreased in the intervention group compared to the control group (−6.75; 95% CI: -10.28 – −3.23). Moreover, left ventricular mass index (−8.21; 95% CI: −15.43 – −0.98) and relative left ventricular wall thickness (−0.04; 95% CI: −0.07 – 0.00) significantly decreased within the intervention group, reflecting amelioration of adverse remodelling, albeit without statistically significant intervention effect when compared to the control group.
Conclusions:
Significant weight loss through bariatric surgery may improve left ventricular geometry in severely obese adolescents. These findings support the potential of bariatric surgery not only for reducing weight loss but also for improving cardiac health.
This chapter discusses the role of neuroanatomy in the development and maintenance of obesity. Similar to other addictive behaviors, alterations in dopaminergic and opioid pathways involved in food reward are important in obesity. The reward system, including the striatal nucleus accumbens, caudate nucleus, amygdala, anterior insula, and OFC, has been implicated in the development of obesity. Activation in these areas to food cues predicts food consumption, weight gain, and changes with weight loss. Interestingly, gut hormones can modulate the activation of these reward systems both at rest and in response to food stimuli. Surgical interventions for obesity have proven to be the most effective tool for treating obesity. However, if anatomical manipulations of the gut can alter the hedonic evaluation of food, then the gut-brain axis may be the most important target for future treatments of obesity. This chapter provides a comprehensive overview of the neuroanatomical basis of obesity and highlights the importance of understanding the reward system in the development and treatment of obesity.
Current literature has shown that poor sleep patterns and social jet lag (SJL) are associated with obesity and weight gain. However, this area remains underexplored in patients who have undergone bariatric surgery. We hypothesised that higher levels of SJL and poorer sleep patterns are associated with lower weight loss, greater caloric/nutrient intake and poorer metabolic outcomes following surgery. This study aims to assess the associations of SJL and subjective sleep with anthropometric, metabolic and dietary parameters during the first year following bariatric surgery. SJL, sleep quality and daytime sleepiness were measured in 122 patients (77 % women; median age 33·0 [28·0 – 41·7]). SJL was estimated by the absolute difference between the midpoint of sleep and wake times on weekdays and weekends. Daytime sleepiness and sleep quality were evaluated using the Epworth Sleepiness Scale (Epworth) and the Pittsburgh Sleep Quality Index, respectively. Multiple linear regressions were employed to evaluate the associations of SJL, sleep quality and daytime sleepiness with weight loss, metabolic and dietary outcomes. Independent variables were negatively associated with weight loss after surgery: SJL at 6 months and 1 year; sleep quality at all time points and sleepiness after one year (P < 0·05). SJL was positively associated with calorie and protein intake after 1-year post-surgery (P < 0·05). Our results show that higher SJL and poorer sleep patterns are associated with worse anthropometric, metabolic and dietary outcomes after bariatric surgery. These findings reinforce the importance of addressing variables related to biological rhythms to optimise post-surgical outcomes in bariatric patients.
Bariatric surgery has significantly increased globally as an effective treatment for severe obesity. Nutritional deficits are common among candidates for bariatric surgery, and follow-up of nutritional status is critically needed for post-surgery healthcare management. This observational prospective study was conducted at King Khalid University Hospital in Riyadh. Samples were collected pre- and post-laparoscopic sleeve gastrectomy (LSG), with the visit intervals divided into four visits: pre-surgery (0M), 3 months (3M), 6 months (6M) and 12 months (12M). Food intake and eating patterns significantly changed during the first year (P < 0·001). The mean energy intake at 3M post-surgery was 738·3 kcal, significantly lower than the pre-surgery energy intake of 2059 kcal. Then, it increased gradually at 6M and 12M to reach 1069 kcal (P < 0·00). The intake of Fe, vitamin B12 and vitamin D was below the dietary reference intake recommendations, as indicated by the 24-hour dietary recall. The prevalence of 25 (OH) vitamin D deficiency improved significantly from pre- to post-surgery (P < 0·001). Vitamin B12 deficiency was less reported pre-LSG and improved steadily towards a sufficient post-surgery status. However, 35·7 % of participants were deficient in Fe status, with 28·6% being female at higher levels than males. While protein supplementation decreased significantly over the 12M follow-up, the use of vitamin supplements dramatically increased at 3 and 6M before declining at 12M. Fe and vitamin B12 were the most popular supplements after vitamin D. This study confirms the necessity for individualised dietary plans and close monitoring of candidates’ nutritional status before and after bariatric surgery.
The dual burden of malnutrition is characterised by the coexistence of undernutrition alongside overweight/obesity and diet-related noncommunicable diseases. It is a paradox which disproportionately affects women and is applicable to those who become pregnant after weight loss surgery. Obesity before and during pregnancy is associated with increased risk of adverse perinatal outcomes in both mother and child. Overall lifestyle interventions targeting weight loss in the preconception period have not proven effective, with people, and women in particular, increasingly seeking weight loss surgery. In women with severe obesity, surgery may normalise hormonal abnormalities and improve fertility. In those who become pregnant after surgery, evidence suggests a better overall obstetric outcome compared to those with severe obesity managed conservatively; however, there is heightened risk of maternal nutritional deficiencies and infants born small for gestational age. Specifically, pregnancy soon after surgery, in the catabolic phase when rapid weight loss is occurring, has the potential for poor outcomes. Lifelong micronutrient supplementation is required, and there is considerable risk of malnutrition if nutritional aftercare guidelines are not adhered to. It is therefore recommended that pregnancy is delayed until a stable weight is achieved and is supported by individualised advice from a multidisciplinary team. Further research is required to better understand how weight loss surgery affects the chances of having a healthy pregnancy and to ultimately improve nutritional management and patient care. In this review, we aim to summarise the evidence and guidance around nutrition during pregnancy after weight loss surgery.
Research implicates inflammation in the vicious cycle between depression and obesity, yet few longitudinal studies exist. The rapid weight loss induced by bariatric surgery is known to improve depressive symptoms dramatically, but preoperative depression diagnosis may also increase the risk for poor weight loss. Therefore, we investigated longitudinal associations between depression and inflammatory markers and their effect on weight loss and clinical outcomes in bariatric patients.
Methods
This longitudinal observational study of 85 patients with obesity undergoing bariatric surgery included 41 cases with depression and 44 controls. Before and 6 months after surgery, we assessed depression by clinical interview and measured serum high-sensitivity C-reactive protein (hsCRP) and inflammatory cytokines, including interleukin (IL)-6 and IL-10.
Results
Before surgery, depression diagnosis was associated with significantly higher serum hsCRP, IL-6, and IL-6/10 ratio levels after controlling for confounders. Six months after surgery, patients with pre-existing depression still had significantly higher inflammation despite demonstrating similar weight loss to controls. Hierarchical regression showed higher baseline hsCRP levels predicted poorer weight loss (β = −0.28, p = 0.01) but had no effect on depression severity at follow-up (β = −0.02, p = 0.9). Instead, more severe baseline depressive symptoms and childhood emotional abuse predicted greater depression severity after surgery (β = 0.81, p < 0.001; and β = 0.31, p = 0.001, respectively).
Conclusions
Depression was significantly associated with higher inflammation beyond the effect of obesity and other confounders. Higher inflammation at baseline predicted poorer weight loss 6 months after surgery, regardless of depression diagnosis. Increased inflammation, rather than depression, may drive poor weight loss outcomes among bariatric patients.
The clinical effectiveness of bariatric surgery has encouraged the use of bariatric procedures for the treatment of morbid obesity and its comorbidities, with sleeve gastrectomy and Roux-en-Y gastric bypass being the most common procedures. Notwithstanding its success, bariatric procedures are recognised to predispose the development of nutritional deficiencies. A framework is proposed that provides clarity regarding the immediate role of diet, the gastrointestinal tract and the medical state of the patient in the development of nutritional deficiencies after bariatric surgery, while highlighting different enabling resources that may contribute. Untreated, these nutritional deficiencies can progress in the short term into haematological, muscular and neurological complications and in the long term into skeletal complications. In this review, we explore the development of nutritional deficiencies after bariatric surgery through a newly developed conceptual framework. An in-depth understanding will enable the optimisation of the post-operative follow-up, including detecting clinical signs of complications, screening for laboratory abnormalities and treating nutritional deficiencies.
Obesity has increased worldwide and concerns comorbidity in patients with schizophrenia, and is linked to a high mortality rate in this group. Although bariatric surgery is the gold standard treatment for refractory obesity, it rarely is indicated for subjects with schizophrenia due to psychotic symptoms recurrence.
Objectives
Report weight-loss outcome and psychopathology changes over 36 months follow-up of 5 patients with schizophrenia submitted to bariatric surgery.
Methods
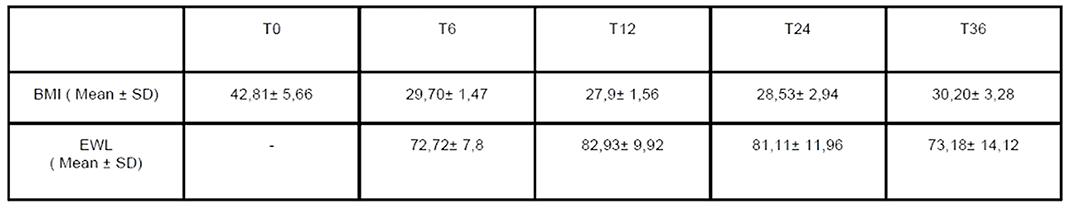
Patients have been followed for 36 months. Clinical and anthropometric assessments such as percentage of excess weight loss (EWL) and body mass index (BMI) have been performed at 6, 12, 24, and 36 months follow-up. The Positive and Negative Syndrome Scale (PANSS) was used to assess psychopathology status. Wilcoxon test was used to assess statistical differences.
Results
The sample included four female and one male subject, with BMI at baseline 42,81± 5,66. The results of BMI and EWL over time are described in Table 1. A significant statistical difference was found between BMI at baseline and at T6, T12, T24, and T36 (p<0,05). EWL was higher at T12 ( compared with T6), but not different from other measurements. PANSS scores at the baseline were 7,7 ± 1,6 for a positive domain, 8,7 ± 2,3 for a negative domain, and 19,2 ± 6 for general psychopathology, with no statistically significant differences during the follow-up.
Conclusions
Despite the small sample, bariatric surgery has been shown a safe and efficient refractory obesity treatment in patients with schizophrenia.
Bariatric surgery is considered an effective treatment against obesity. Psychiatric illness is relatively common in patients who have undergone bariatric surgery. Over one-third of these patients are prescribed psychotropic drugs, particularly antidepressants. Unlike medications for diabetes, hypertension or hyperlipidemia, which are generally reduced and at times discontinued, postsurgery psychotropic use is only slightly reduced. The surgical intervention and the subsequent weight loss can affect several pharmacokinetic parameters, leading to a possible need of dosing adjustment.
Objectives
To review the influence of bariatric surgery on the use and pharmacokinetics of psychotropic drugs.
Methods
Non-systematic review of literature through search on PubMed/MEDLINE for publications from 2011 to 2021, following the terms psychotropic and bariatric surgery. Textbooks were consulted.
Results
It is difficult to predict how psychotropics will be affected by bariatric surgery because of interindividual differences and limited data. Malabsorptive surgical procedures have a relatively greater potential to alter drug exposure. Medication disintegration, dissolution, absorption, metabolism and excretion have been found to be altered in postbariatric patients. Antidepressants are the best studied psychotropics in the bariatric population and their absorption is reduced. The risk of gastric bleeds with bariatric surgery will probably be increased by serotoninergic antidepressants. Antipsychotics and mood stabilisers are not well studied in these patients. Depot antipsychotics avoid the risk of reduced absorption after surgery. Lithium use requires particular close monitoring.
Conclusions
Close treatment monitoring and the ongoing monitoring of symptoms are needed after bariatric surgery. Many patients may not require significant changes to drug treatment after surgery.
Attention-deficit/hyperactivity disorder (ADHD) is a neurodevelopmental condition characterized by symptoms of inattention, hyperactivity, and impulsivity, which only rarely remits in adulthood[1]. A positive association between ADHD and obesity has been repeatedly observed, especially in adult samples[2]. However, only a few studies investigated the prevalence and correlates of ADHD in obese patients seeking bariatric treatment[3,4].
Objectives
Our study was aimed to examine the prevalence of probable ADHD comorbidity in a sample of obese patients referred for bariatric surgery. Secondly, we sought to characterize differences in eating behaviour between obese subjects with and without probable ADHD.
Methods
The study sample was composed of 110 adult obese patients (BMI ≥ 30 kg/m2) consecutively referred for bariatric surgery to the Obesity Center of the Endocrinology Unit in Pisa University Hospital between November 2010 and May 2012. Probable ADHD was identified using a recently developed screening scale based on items selected from Symptom Check‐List‐90‐R (SCL-90-R)[5]. The extent of binge-eating/purging and night-eating behaviours were respectively estimated using the Bulimic Investigatory Test, Edinburgh (BITE)[6] and the Night-eating Questionnaire (NEQ)[7]. Wilcoxon test was used for statistical comparisons, with a significance level of p<0.05 set for all tests.
Results
Probable ADHD was found in 14 subjects (12.7%, 95%CI=7.1-20.4%). Patients with probable ADHD showed significantly higher BITE symptom score (20.4±9.3 vs. 12.1±7.5, r=0.31, p=0.001) and NEQ total score (16.1±9.2 vs. 9.5±3.9, r=0.27, p=0.005).
Conclusions
ADHD is a relatively common comorbidity in obese patients seeking bariatric treatment, which is positively associated with disordered eating habits, such as binge-eating/purging and night-eating behaviours.
To determine the relative validity and reproducibility of the Eetscore FFQ, a short screener for assessing diet quality, in patients with (severe) obesity before and after bariatric surgery (BS).
Design:
The Eetscore FFQ was evaluated against 3-d food records (3d-FR) before (T0) and 6 months after BS (T6) by comparing index scores of the Dutch Healthy Diet index 2015 (DHD2015-index). Relative validity was assessed using paired t tests, Kendall’s tau-b correlation coefficients (τb), cross-classification by tertiles, weighted kappa values (kw) and Bland–Altman plots. Reproducibility of the Eetscore FFQ was assessed using intraclass correlation coefficients (ICC).
Setting:
Regional hospital, the Netherlands.
Participants:
Hundred and forty participants with obesity who were scheduled for BS.
Results:
At T0, mean total DHD2015-index score derived from the Eetscore FFQ was 10·2 points higher than the food record-derived score (P < 0·001) and showed an acceptable correlation (τb = 0·42, 95 % CI: 0·27, 0·55). There was a fair agreement with a correct classification of 50 % (kw = 0·37, 95 % CI: 0·25, 0·49). Correlation coefficients of the individual DHD components varied from 0·01–0·54. Similar results were observed at T6 (τb = 0·31, 95 % CI: 0·12, 0·48, correct classification of 43·7 %; kw = 0·25, 95 % CI: 0·11, 0·40). Reproducibility of the Eetscore FFQ was good (ICC = 0·78, 95 % CI: 0·69, 0·84).
Conclusion:
The Eetscore FFQ showed to be acceptably correlated with the DHD2015-index derived from 3d-FR, but absolute agreement was poor. Considering the need for dietary assessment methods that reduce the burden for patients, practitioners and researchers, the Eetscore FFQ can be used for ranking according to diet quality and for monitoring changes over time.
Obesity is commonly associated with polycystic ovarian syndrome (PCOS), featuring both elements of insulin resistance and metabolic syndrome. Understanding the causes of obesity, its impact on health and its comorbidities, as well as its regulation, are important factors in relation to the treatment of obesity and more particularly the effect of weight loss in PCOS. The various modalities of treatment include the conservative approach, utilizing lifestyle and dietary techniques, pharmacotherapy and the more invasive surgical approach, which has been shown to have better weight-loss results and less recidivism.
There is a need to investigate how adopting different strategies for treating obesity in different countries in the European Union affects the psychological well-being of patients.
Aims
The aim of this study was to perform a comparative evaluation of psychiatric symptoms (depression, anxiety and stress) in patients undergoing bariatric surgery versus patients receiving conservative treatment for morbid obesity in Poland and Germany.
Method
A multicentre international prospective cohort study with 155 patients who underwent bariatric surgery and 409 patients who received conservative weight reduction treatment. Evaluation of the psychiatric symptoms was carried out for each patient at baseline and after 12 months of active treatment using a standardised Depression Anxiety Stress Scale questionnaire (DASS-21) questionnaire.
Results
After 12 months of active treatment, the level of psychiatric symptoms (depression, anxiety and stress) significantly decreased in both groups of patients: surgically treated versus conservatively treated patients from Poland and also from Germany. The median change in level of psychiatric symptoms among patients from both countries was significantly higher among surgically treated patients compared with conservatively treated patients (Poland P < 0.0001; Germany P < 0.0001). Improvements in the patient's mental health as a consequence of treatment were dependent on the specific strategy for treating obesity adopted in the analysed countries, the percentage of total weight loss and on gender.
Conclusions
The use of bariatric surgery in both Poland and Germany compared with non-surgical treatment for obesity resulted in more measurable benefits in the form of a decrease in psychiatric symptoms (depression, anxiety and stress) and reduction in body weight.
Food addiction (FA) appears among bariatric weight loss surgery candidates who struggle to control the intake of hyperpalatable/refined foods have high rates of psychopathology and related health problems. Despite this, prevalence rates of FA in the bariatric sector are reported as low or variable. We investigated the prevalence of FA and the applicability of conventionally used metrics for 166 pre-surgery candidates from a weight management centre (USA) and a major metropolitan hospital (Australia). Self-report measures assessed FA (Yale Food Addiction Scale (YFAS)), body mass index (BMI), disordered eating, addictive personality, psychopathology, and diet. Consistent with prior research, standard YFAS scoring, requiring the endorsement of a distress/impairment (D/I) criterion (FA + D/I), yielded a FA prevalence rate of 12.7%, compared to 37.3% when D/I was omitted (FA − D/I). We compared profiles for those with FA using each scoring method against those ‘without’, who did not meet a minimum of three YFAS symptoms (non-FA ≤ 2). Both methods differentiated those with and without FA on addictive traits, disordered eating and hyperpalatable food consumption. Only FA + D/I differentiated markers of psychological distress or impairment, including depression, anxiety and quality of life. Results indicate a need for further FA research in bariatric settings.
Previous research has found that candidates for bariatric surgery usually present anxiety, depression, personality disorders and/or a tendency to binge eating. The situation related with the pandemic and the lockdowns during the 2020 are possible aggravating factors for these characteristics.
Objectives
To study the more important psychological characteristics presented by candidates for bariatric surgery.
Methods
40 people between 29 and 65 years old (M=46.4, SD=9.1; 37.5% male, 62.5% female) were evaluated between July and December of 2020. The assessment consisted in an interview carried out by a clinical psychologist, and a pool of questionnaires to evaluate depression and anxiety symptoms (Beck Depression Inventory, BDI; and the Goldberg Anxiety and Depression Scale, GADS) the existence of a binge eating pattern (the Binge Eating Scale; BES) and personality traits (the Salamanca Screening Test).
Results
The 25% of the sample had previous mental health antecedents. Eight people disclosed to feel stress in relation with the COVID-19, and 18 presented an emotional regulation strategy using food during the lockdown. 62.5% scored above the cut-off point on the BDI (mild=27.5%, moderate=20%, severe=15%) and a 40% and a 47.5% did it for the anxiety and the depression (respectively) GADS subscales. 20% presented a binge eating pattern according with the BES. Most common personality traits were histrionic (50%), emotionally unstable impulsive type (45%), and anxious (42.5%).
Conclusions
These findings support the previous scientific literature. Psychological intervention programs may be considered to guarantee the surgery’s success, especially when adverse contextual circumstances are presented.
